For Clinicians | It Was Only a Lick: A Rabies Exposure Case Study Part 1
For Clinicians | It Was Only a Lick: A Rabies Exposure Case Study

Off Duty Series: Part 1 of 6

By Aaron Asay, PA-C, DMSc, FIBODM, FAWM
Medically reviewed and edited by Dr. Jamie Wilkey, PharmD, Director of Clinical Education

Off Duty is a six-part series on the emergencies clinicians end up handling outside of work: a call from family overseas, a car crash, a choking baby, a bad bleed. Aaron Asay has spent his career in emergency, disaster, and austere medicine. Part 1 comes from his own family: his daughter’s rabies exposure while volunteering in Peru.

At the mention of rabies, most people think of wild dogs, angry bats, and a painful shot if you get exposed. But due to increased vaccination rates and more careful wildlife management, actual human cases of this illness have all but disappeared in the majority of our communities and neighborhoods. However, that doesn’t mean exposure doesn’t still occur, nor does it mean that the rest of the world has the same safety record as we do here in the United States.

This is a case study on a rabies exposure that occurred in South America recently. Some details have been changed to protect the privacy of those involved, but for the sake of full disclosure, this was my own daughter, and in the process of navigating her experience, I realized I knew less than I thought I did regarding the management of a rabies exposure while traveling. As an emergency medicine Physician Assistant, and even with a doctorate degree and training in Global Health, I wasn’t fully prepared for this situation. I hope this article helps to clear up some misconceptions and gives others a better understanding of managing a case like this one. This isn’t an academic paper; rather, it’s more of an awareness campaign for laypeople and providers alike.

The Story

My daughter has been living in a small town in Peru for several months, teaching English with a group of other volunteers in their early twenties. About three weeks ago, several of them took a trip to Machu Picchu. On the way back they got stuck at a bus stop with a long wait ahead of them. The mosquitoes had eaten her alive, and she had scratched the bites on her arm until several were open and bleeding. Worn out from the hike, she dozed off. She woke up to a dog licking her arm.

That alone would make most of us jump, but it was the dog itself that made the girls nervous. It staggered when it walked, drooled constantly, and wandered around like it was searching for water. They were fairly sure it was blind. Before they could decide what to do, a local boy grabbed it and disappeared. One of the girls finally said out loud what they were all thinking. Rabies. Three of the girls had been licked, and all three had broken skin where the saliva made contact. That night, back at the hotel, they scrubbed their arms and called me.

What Is Rabies?

I need to stop here and explain something I didn’t fully appreciate until that phone call. Rabies virus can be present in the saliva of an infected animal, and a bite isn’t the only way in. Saliva on broken skin, even a scratched-open mosquito bite, can transmit it. The World Health Organization sorts animal exposures into three categories, and saliva on broken skin lands in Category III, the most serious, right alongside bites that penetrate the skin. Once symptoms start, rabies is virtually always fatal. Before that, appropriate treatment is extremely effective. Everything depends on what happens in between¹,².

Most of the exposures I’ve managed in the ER involved bats. Here at home, bats are responsible for approximately 70 percent of human rabies cases acquired in the United States³. Worldwide, dogs account for up to 99 percent of human rabies transmission, and WHO estimates that rabies kills tens of thousands of people every year, likely more given how many cases go unreported².

So I did what I tell my students to do. I pulled up the guidance, confirmed that saliva contacting broken skin was a Category III exposure, and told her she needed wound care, a series of vaccines, and rabies immune globulin, which we call RIG¹,⁴.

If you’re unfamiliar with RIG, that’s OK. Most people are. The vaccine teaches your body to make its own antibodies, but that takes time. RIG provides ready-made antibodies that cover the gap, and whenever possible it’s infiltrated directly into and around the wounds. It isn’t just another shot in the arm, and as I would soon find out, even healthcare providers get that part wrong⁴.

Why I Was Worried

It took an extra day to get seen at the local health center, so her first vaccine dose came on day three after the lick. They were told RIG wasn’t available to foreigners through the local system and they would have to leave the country to get it. The staff didn’t seem worried anyway. Rabies, they said, doesn’t really happen here.

To be fair, they had a point about the odds. Dog rabies has circulated in the Arequipa region since it returned there in 2014, with a confirmed human case in Arequipa in 2023⁵. CDC identifies dog rabies primarily in Arequipa, Puno, and southern Cusco, rather than the area around Machu Picchu, and notes that bat rabies is more common in Peru than dog rabies⁶.

But odds describe populations. We had one specific dog that staggered, drooled, and seemed blind, and it vanished before anyone could observe or test it. Those symptoms aren’t unique to rabies. Other illnesses and injuries can produce similar behavior. But combined with saliva contacting broken skin, and no way to rule out rabies in the animal, I wasn’t willing to dismiss it.

Then there was the chart. Her scratches had scabbed over by the time she was examined, so the provider wrote that there were no obvious wounds and RIG wasn’t recommended. The leaders of her volunteer organization leaned on that note and tried to talk the girls into staying put. I understand why, but the exposure category is decided by what happened at the bus stop, not by how the skin looks three days later¹.

Why We Publish Guidelines

This is where the story takes a turn that still bothers me. My daughter and one friend decided to get the immune globulin. The third girl, reassured by the health center and her organization, chose to continue the vaccines without it. She decided to “risk it.” I don’t blame her. She was a young woman in a foreign country getting conflicting advice, with local providers on one side and somebody’s dad on the phone on the other. Who would you believe? But all three had saliva contact with broken skin, the dog couldn’t be observed or tested, and it showed neurological signs that could have been consistent with rabies. Those are exactly the circumstances the guidelines were written for¹,⁴.

RIG also comes with a deadline. It can be given up to seven days after the first vaccine dose, but isn’t recommended after that because the body is expected to be developing its own antibodies and RIG can interfere with that response. The clock starts with the first vaccine dose, not the exposure. And the vaccine should never be held back just because RIG isn’t available¹,⁴.

Healthcare Shortfalls Are Similar Everywhere

The closest place we could arrange treatment was Miami. My daughter got her second dose in Peru, right on schedule, and got on a plane with her friend.

The Miami ER visit took about nine hours, and it was clear this wasn’t routine for the team. My daughter received her RIG the right way, infiltrated into and around the identifiable wounds on her arm, along with her third vaccine dose. Her friend’s lesions had healed over, so the nurse split her RIG between injections in both arms instead. The thing is, those spots were still visible. Anyone who took a minute to look could have found exactly where the saliva had touched broken skin.

For my fellow providers, this is the part I’d underline. CDC guidance is to infiltrate as much of the calculated RIG dose as anatomically feasible into and around the wounds, with any remainder administered intramuscularly at a site distant from the vaccine. RIG and the first vaccine dose should not be administered in the same anatomical location⁴. WHO goes further, emphasizing local wound infiltration, and no longer recommends injecting leftover RIG into a distant muscle¹. The wound is the priority. When no wound can be identified, CDC still calls for RIG, given intramuscularly at a site away from the vaccine⁴. But when the original exposure sites are identifiable, they should be assessed for infiltration. If RIG was given incorrectly, don’t assume the treatment has failed. CDC guidance addresses situations where additional RIG infiltration may be considered, subject to dose and timing limitations⁴. Call your public health department or a rabies specialist before attempting corrective treatment.

One Last Hurdle

Back in Peru, the schedule brought one more surprise. The standard CDC schedule for someone never vaccinated, who is not immunocompromised, is four doses on days 0, 3, 7 and 14⁴. Day zero means the day the first vaccine is administered, not the day of exposure. Peru wanted her fourth dose on day 28. My first reaction was that somebody had it wrong. They didn’t. WHO recognizes a four-dose intramuscular schedule that allows the final dose anywhere from day 14 to day 28¹. Different countries use different approved schedules, and an unfamiliar protocol doesn’t necessarily mean an incorrect one.

I’ve worked in enough health systems abroad that I should have remembered that. But when your daughter’s record says day 14 and a clinic tells her to come back two weeks later, it gets your attention.

It’s now been about three weeks since the exposure. All three girls are doing well and are scheduled to receive their fourth and final rabies vaccine dose next week. My daughter’s biggest worry has been for her two friends, one who received RIG in the wrong place and one who went without it. Rabies usually takes weeks to months to show itself, sometimes longer². That worry doesn’t go away quickly. Neither situation means either girl will develop rabies, but both deserve review with public health or a rabies specialist. Completing the vaccine series will be reassuring, but it doesn’t change the fact that immune globulin was recommended for their Category III exposures.

Then came the bill. When we filed with our travel insurance for the flight to Miami, they asked for a signed note from the treating doctor. The only note we had was the one saying RIG wasn’t needed. They denied the claim. One line in a chart, written after a quick look at some scabs, cost us thousands of dollars. Providers, what you write follows the patient, sometimes across borders and all the way to an insurance claim. Classify the exposure by what happened, not by what the skin looks like when the patient finally gets to you.

I’ve gone back and forth on the pre-exposure vaccine, and I’m not convinced every short-term traveler needs it. But CDC recommends considering it for expatriates and people spending time in rural areas where access to appropriate rabies treatment may be limited⁶,⁸. Which describes my daughter. The initial pre-exposure series is two doses, a week apart. If you’re subsequently exposed and meet the criteria for being previously vaccinated, you generally need two more vaccine doses and no RIG. People with ongoing risk may need antibody testing or a booster to maintain their protection⁷,⁸. Where RIG is hard to find, that takes one of the hardest parts of the problem off the table before you leave home.

For other travelers, keep unfamiliar animals away, even the friendly ones, and keep open wounds covered. If an animal bites, scratches, or licks broken skin, wash it with soap and running water for at least fifteen minutes and get medical care promptly². If human RIG isn’t available, ask what alternatives are approved and available locally. Equine rabies immune globulin and, in some countries, rabies monoclonal antibody products may be options, depending on local regulatory approval and availability¹,²,⁸. Photograph the vaccine products you receive, keep a record of the dates and doses, and read your insurance fine print on evacuation before you need it.

I’ve spent years working in places where medical resources are limited, and a good part of my career has involved teaching people how to prepare for emergencies. Yet here I was, trying to get my own daughter the treatment she needed, and discovering just how difficult that could be. The medication wasn’t available, the medical advice was conflicting, and even after we got her to an American emergency department, things didn’t go quite as expected. I learned a few things about rabies that I should have known already. But I also got a reminder of something I’ve been teaching for years. Knowing what to do doesn’t always mean you’ll have the resources to do it. I started this thinking I had a pretty good handle on rabies. The lesson came from a dog at a bus stop in Peru. It was only a lick. It was also a Category III rabies exposure.

Quick Reference: Rabies Exposure

Question Answer Source
Does a lick count? Yes, if saliva contacts broken skin or a mucous membrane. This is WHO Category III. 1
First thing to do? Wash thoroughly with soap and running water for at least 15 minutes, then seek medical care. 2
Category III, never vaccinated? Wound care, vaccine, and immune globulin, or an approved alternative where indicated and available. 1, 2, 4
No RIG available? Start vaccination without delay. Seek expert guidance about obtaining the remaining recommended treatment. 1, 4
RIG deadline? No later than day 7 after the first vaccine dose. 1, 4
Where does RIG go? Into and around identifiable wounds as anatomically feasible. Follow product-specific and national guidance for any remaining volume. 1, 4
US vaccine schedule? Days 0, 3, 7 and 14. Immunocompromised patients require an additional dose on day 28 and further assessment. 4
WHO four-dose IM schedule? Days 0, 3, 7 and a fourth dose between days 14 and 28. 1
Pre-exposure vaccination? Initial doses on days 0 and 7. Previously vaccinated people generally receive two post-exposure doses without RIG, subject to applicable guidance. 7, 8
Treated abroad? Keep product names, dates, doses, and administration records. Consult public health if schedules or products differ. 4, 8


Sources

  1. World Health Organization. Rabies vaccines: WHO position paper, April 2018. Weekly Epidemiological Record. 2018;93(16):201-220. https://www.who.int/publications/i/item/who-wer9316
  2. World Health Organization. Rabies. Fact sheet. https://www.who.int/news-room/fact-sheets/detail/rabies
  3. Pieracci EG, Pearson CM, Wallace RM, et al. Vital Signs: Trends in Human Rabies Deaths and Exposures, United States, 1938-2018. MMWR. 2019;68:524-528. https://www.cdc.gov/mmwr/volumes/68/wr/mm6823e1.htm
  4. Centers for Disease Control and Prevention. Rabies Post-exposure Prophylaxis Guidance. https://www.cdc.gov/rabies/hcp/clinical-care/post-exposure-prophylaxis.html
  5. Centro Nacional de Epidemiología, Prevención y Control de Enfermedades (CDC Perú). CDC Perú emite alerta epidemiológica sobre un caso confirmado de rabia humana urbana en Arequipa. October 17, 2023. https://www.dge.gob.pe/portalnuevo/informativo/prensa/cdc-peru-emite-alerta-epidemiologica-sobre-un-caso-confirmado-de-rabia-humana-urbana-en-arequipa/
  6. Centers for Disease Control and Prevention. Peru. CDC Yellow Book, 2026 edition. https://www.cdc.gov/yellow-book/hcp/americas-caribbean/peru.html
  7. Rao AK, Briggs D, Moore SM, et al. Use of a Modified Preexposure Prophylaxis Vaccination Schedule to Prevent Human Rabies. MMWR. 2022;71:619-627. https://www.cdc.gov/mmwr/volumes/71/wr/mm7118a2.htm
  8. Centers for Disease Control and Prevention. Rabies. CDC Yellow Book, 2026 edition. https://www.cdc.gov/yellow-book/hcp/travel-associated-infections-diseases/rabies.html

Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.
Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

Flu and COVID Prevention for the Holidays: Why Timing Matters

Flu and COVID Prevention for the Holidays: Why Timing Matters

By the Jase Medical Team

The holidays are a time for gathering around the table, catching up with family, and making memories with the people we love.

They’re also a time when respiratory viruses can spread quickly, especially when families travel and multiple generations gather indoors.

If you’re planning to spend Thanksgiving with your children and grandchildren, there’s one important question to ask now:

Will your flu vaccine have enough time to work before everyone arrives?

Preventing flu and COVID isn’t about one perfect precaution. It’s about layering several practical steps together, starting before the holiday season begins.

How Long Does the Flu Shot Take to Work?

It takes approximately two weeks for your body to develop protective antibodies after a flu vaccination.

That means if you’re hoping to have vaccine protection in place for Thanksgiving on November 26, 2026, aim to get your flu shot by November 12.

You can still benefit from vaccination after that date, but your immune system needs time to build protection.

The CDC recommends annual flu vaccination for nearly everyone six months and older, with rare exceptions.

Why every year? Because flu viruses change, and immune protection decreases over time. Each season’s vaccine is designed to protect against viruses expected to circulate.

COVID vaccination also remains an important prevention tool, particularly for older adults and people with underlying medical conditions. Recommendations vary by age, risk factors, vaccination history, and current guidance, so discuss your options with your healthcare provider or pharmacist.

You’re Not Just Protecting Yourself

One of the most meaningful benefits of vaccination is that it can help protect the people around you.

Research has shown that vaccinating children against influenza can reduce infections among unvaccinated members of their communities. Other studies have found that recent COVID vaccination can reduce the likelihood of transmitting the virus within a household, although that protection decreases over time.

When more people around the holiday table are protected, vulnerable family members may benefit too.

That matters especially for grandparents, infants, and loved ones living with heart disease, diabetes, lung disease, or weakened immune systems.

Vaccination isn’t a guarantee that you won’t get sick. But it can reduce your risk of infection and, importantly, lower the likelihood of severe illness, hospitalization, and serious complications.

For older adults, that protection can make a significant difference.

What If Someone Tests Positive Before Thanksgiving?

Imagine you’re preparing for a family gathering when your grandson develops a fever and tests positive for influenza.

Or you learn that someone you spent yesterday afternoon with has COVID.

Should you wait to see whether symptoms develop?

If you’re at higher risk for complications, contact your healthcare provider promptly after a known exposure.

There are prescription antiviral medications that may help prevent certain infections after exposure, but they are not appropriate for everyone.

Flu: Prevention After Exposure

For influenza, medications such as oseltamivir (Tamiflu) and baloxavir (Xofluza) may be prescribed for post-exposure prevention in certain circumstances.

When prescribed for this purpose, timing is important. Preventive treatment is generally considered within 48 hours after the relevant exposure.

Your healthcare provider will consider factors such as your age, medical history, vaccination status, and the nature of the exposure before recommending medication.

COVID: Ask About Current Prevention and Treatment Options

COVID prevention and treatment options continue to evolve.

Prescription antivirals may be appropriate for certain patients, but medications used to treat an active COVID infection are not necessarily approved or recommended to prevent infection after exposure.

If you’ve been exposed to COVID, especially if you’re 65 or older or have a chronic medical condition, contact your healthcare provider to discuss current options, testing, and the symptoms to monitor.

Don’t start prescription antivirals on your own or use medications prescribed for someone else. A qualified healthcare professional should determine whether preventive or therapeutic treatment is appropriate.

Three Simple Ways to Protect Your Holiday Gathering

Vaccination and prescription medications aren’t the only tools available.

A few everyday precautions can reduce the likelihood of spreading respiratory viruses.

1. Stay home when you’re sick. If you have a fever, cough, sore throat, or other respiratory symptoms, don’t assume it’s just a cold. Follow current public health guidance for staying home and returning to normal activities.

2. Consider testing before visiting someone at high risk. A COVID test before gathering with an older relative or someone with a weakened immune system can provide useful information. Remember that a negative rapid test doesn’t completely rule out infection.

3. Improve indoor airflow. Opening windows when practical, using effective air filtration, and spending time outdoors can help reduce the concentration of airborne respiratory viruses.

These precautions are especially valuable when someone at your gathering has a higher risk of serious illness.

Medical Preparedness Starts Before the Holiday

Most people think about medical preparedness in terms of emergency supplies, medications, and what to do when healthcare becomes difficult to access.

But preparation also means taking steps to prevent illness before it happens.

For flu and COVID, that includes knowing when to get vaccinated, understanding your personal risk factors, and having a plan for what to do after an exposure.

If you’re traveling this holiday season, consider discussing these questions with your healthcare provider:

  • Am I up to date on the vaccines recommended for me?
  • Am I at higher risk for complications from flu or COVID?
  • If I’m exposed or develop symptoms while traveling, when should I contact a healthcare professional?
  • Are there prescription treatments or preventive options appropriate for my medical history?

At Jase Medical, our family team of doctors, PAs, and pharmacists believes appropriate medical preparation begins with informed decisions made before an emergency.

The goal isn’t to eliminate every risk. It’s to make it easier for everyone around the table to enjoy the holidays safely.

So before the turkey goes in the oven and the family starts arriving, take a moment to review your vaccination status and make a plan.

A little preparation now can help protect the people who make the holidays worth celebrating.

Medical disclaimer: This article provides general educational information and does not replace individualized medical advice. Vaccination and antiviral recommendations depend on personal health factors and current clinical guidance. Prescription antivirals should only be used following evaluation and authorization by a qualified healthcare professional. If you develop symptoms after an exposure, contact your healthcare provider promptly, especially if you’re at increased risk for severe illness.

Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

For Clinicians | How Long Does the Flu Shot Take to Work? Holiday Flu Prevention

For Clinicians | How Long Does the Flu Shot Take to Work? Holiday Flu Prevention

By Dr. Jamie Wilkey, PharmD, Director of Clinical Education
Medically reviewed and edited by Kristen Carpenter, PA-C

Hi again, everyone. Last week I had a lot of fun writing about flu treatment, but the whole time I was writing it, I felt like half the story was missing. Treating the flu is one thing. Not getting it in the first place is even better. I’m a girl who loves preventative medicine and will do just about anything to keep sickness out of my house. So today we’re talking flu prevention, because everyone’s looking at the calendar and seeing Thanksgiving right around the corner. This is the season of getting together with family from all over the country, and we’ll cover when the shot needs to happen, what to do when someone at the table tests positive, and where COVID and RSV fit into the same season.

A couple of Sundays ago, I was sitting next to one of my good friends at church, and we got to talking about shots. We both agreed we hate getting vaccines. We’re also strict about getting them every single year, because we love preventing sickness, for ourselves and for the herd immunity of everyone around us. I already gave my family their flu and COVID shots, so we’re all ready to go for this season. This isn’t something I’m just preaching. It’s something I’m doing for my own family.

How long does the flu shot take to work?

About two weeks. Flu vaccines cause antibodies to develop about two weeks after vaccination¹, so protection at Thanksgiving dinner on November 26 means a shot by November 12. Yep, that’s this week!!

The end of October was CDC’s ideal¹, but it isn’t too late, and we keep offering the shot as long as flu is circulating². Bring it up at every visit and refill call this week, in the office or at the pharmacy counter.

For patients 65 and up, reach for an enhanced vaccine: high-dose, adjuvanted, recombinant, or mRNA². If none of those is on the shelf, give the standard shot rather than wait³.

And for the patient who says the flu shot never works for them anyway that’s a great time to remind them that even when it doesn’t stop the infection, vaccinated adults hospitalized with flu are far less likely to end up in the ICU⁴.

Does the flu shot protect the people around your patient?

It can, and that’s the herd immunity my friend and I were talking about. In a cluster-randomized trial in Hutterite colonies in Canada, vaccinating the kids cut confirmed flu by 61% among the community members who didn’t get the study vaccine⁵. Kids bring flu home, so protecting them protects the people they live with.

CDC is a little more careful, saying a shot “may also protect people around you”⁴. The protection doesn’t last forever: immunity wanes and the virus changes every season, which is why this is a yearly shot.

So when a patient tells you they never get the flu and don’t need it, that’s the moment to remind them the shot isn’t only for them. It’s for the grandparent flying in for Thanksgiving and the baby too young for a flu shot of their own¹.

What should happen after a flu exposure?

Tell your high-risk patients to call the same day someone at the gathering tests positive. They need to call that day, not when they start feeling a fever come on 2-3 days later. That day.

Prevention after an exposure is based on the exposure clock, not the symptom clock:

  • Oseltamivir (Tamiflu): start within 48 hours of close contact⁶.
  • Baloxavir (Xofluza): a single dose within 48 hours of contact, for ages 5 and up⁷.

Once symptoms start, it’s a treatment question.

But alas, that’s not so easy over the next couple of months because it is a holiday problem. If someone coughs through Thursday’s turkey, tests positive Friday morning, and the 48-hour window closes Saturday night…that’s all happening on a holiday weekend when most offices are closed.

Prevention after exposure works. In the Tamiflu household trial, confirmed flu dropped from 12% to 1% in the contacts who took it⁶. The patients who most need that same-day call are the ones flu hits hardest: adults 65 and up, pregnant patients, and anyone with a chronic condition like asthma, diabetes, or heart disease⁸. 

And in case you were feeling like, well, it’s way easier to just take Tamiflu than get a shot…. it’s no substitute for the shot⁶. It’s not always easy to get, either. Generic oseltamivir is the cheap one, around $22 to $55 for a 10-capsule box, depending on the pharmacy and whether there’s a discount card⁹. Xofluza is brand-only, about $170 to $250 cash for a single dose¹⁰.  Insurance usually puts quantity limits on oseltamivir, so a prevention course can eat into what the plan covers for treatment later in the season, and Xofluza often needs a prior authorization first¹¹,¹².

And pharmacies run out during the holiday rush (I know, because I worked in one for years and we almost always ran out). Last January, ASHP listed some oseltamivir capsules and powders in short supply from local stockouts driven by demand¹³. Check stock before you send the prescription.

COVID and RSV should be considered too!
Flu is the one on everyone’s mind, but COVID and RSV travel to the same gatherings.

For COVID, AAFP recommends an updated vaccine for every adult this season, with two doses six months apart at 65 and up². A shot in the past six months also cut spread to household members by about 43%, and the effect was no longer measurable by month seven¹⁴. After an exposure, there’s now a pill for COVID too: ensitrelvir (Xocova), approved in late May for ages 12 and up and started within 72 hours of contact¹⁵. It’s a strong CYP3A inhibitor, so check the full medication list and pregnancy status first. Paxlovid is still treatment only, started within 5 days of symptoms.

For RSV, AAFP recommends a single dose for those ages 75 and up, and at 50 to 74 for anyone at increased risk². There’s no pill after an RSV exposure, and treatment is mostly supportive¹⁶, so the shot is the prevention. Babies get theirs through the maternal vaccine or an infant antibody¹⁷.

What else keeps patients well at holiday gatherings?

If someone’s sick, they stay home until they’ve gone 24 hours with symptoms getting better and no fever, without fever reducers¹⁸. For five days after that, CDC suggests extra care: cleaner air, good hygiene, a mask, some distance, and a test before being around others, especially anyone at higher risk¹⁸. Not fancy or expensive, but it works: a cracked window, clean hands, and a negative test before the hugs start.

Why plan before the gathering?

Prevention after an exposure runs all or none: the call reaches a prescriber inside 48 hours AND medication is readily available from a pharmacy, or the window closes somewhere between the leftovers and Saturday night. Most of the work can happen before anyone’s sick, though: the shot by November 12, a high-risk patient who knows to call the same day, and a written list of everything they take, supplements included. On a holiday weekend, the prescriber who picks up the phone may never have met them, and the COVID antivirals interact with a long list of common drugs. That right there is appropriate medical preparation.

At Jase, we build that layer for the times primary care isn’t there, never as a replacement for it. If you’d rather not field these calls over a holiday weekend, you can refer patients to us. A licensed provider reviews every request, and Tamiflu and Paxlovid are available as JaseCase add-ons for treatment, for emergency use only, after first seeking the assistance of a qualified healthcare provider. 

The bottom line

Get flu shots in by November 12, with an enhanced vaccine at 65 and up, and keep COVID and RSV vaccines in the same conversation. Tell high-risk patients to call the same day someone at the gathering tests positive. Then go enjoy the pie.

To refer a patient, visit jase.com. A licensed provider reviews every request and writes a prescription only when it’s appropriate.


Sources

  1. CDC. Key Facts About Seasonal Flu Vaccine. Updated September 1, 2026. https://www.cdc.gov/flu/vaccines/keyfacts.html
  2. Lin KW. Practice Alert: AAFP 2026–2027 Respiratory Vaccine Recommendations for Adults. Am Fam Physician. 2026;114(4):333-335. https://www.aafp.org/afp/2026/1000/editorials-respiratory-vaccine-recommendations-adults
  3. CDC. Prevention and Control of Seasonal Influenza with Vaccines: Recommendations of the Advisory Committee on Immunization Practices, United States, 2025-26 Influenza Season. Summary of Recommendations. MMWR 2025;74(32):500-507. https://www.cdc.gov/flu/media/pdfs/2025-2026-summary-of-recommendations.pdf
  4. CDC. Benefits of Flu Vaccination. May 28, 2026. https://www.cdc.gov/flu-vaccines-work/benefits/
  5. Loeb M, Russell ML, Moss L, et al. Effect of influenza vaccination of children on infection rates in Hutterite communities: a randomized trial. JAMA. 2010;303(10):943-950. https://doi.org/10.1001/jama.2010.250
  6. Tamiflu (oseltamivir phosphate) prescribing information. Genentech, Inc. Revised December 2025. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=ee3c9555-60f2-4f82-a760-11983c86e97b
  7. CDC. Influenza Antiviral Medications: Summary for Clinicians. Updated March 10, 2026. https://www.cdc.gov/flu/hcp/antivirals/summary-clinicians.html
  8. CDC. People at Increased Risk for Flu Complications. September 11, 2024. https://www.cdc.gov/flu/highrisk/index.htm
  9. GoodRx. Oseltamivir prices, 75 mg, 10 capsules. Accessed October 26, 2026. Prices vary by location and pharmacy. https://www.goodrx.com/oseltamivir
  10. SingleCare. Xofluza coupons and prices, 40 mg tablet. Accessed October 26, 2026. Prices vary by location and pharmacy. https://www.singlecare.com/prescription/xofluza
  11. Prime Therapeutics for Blue Cross and Blue Shield of Minnesota. Anti-Influenza Agents Quantity Limit Program Summary. Effective November 1, 2025. https://bluecrossmn.com/sites/default/files/DAM/2022-09/MN_PS_Anti-Influenza_Agent_QL_ProgSum_AR0621_r0721.pdf
  12. Blue Cross Blue Shield Association, Federal Employee Program. Xofluza, policy 5.01.049. Effective July 1, 2026. https://www.fepblue.org/-/media/PDFs/Medical-Policies/2026/July-2026/Pharmacy-Policies/Remove–Replace/501049-Xofluza-baloxavir-marboxil.pdf
  13. Journal of Urgent Care Medicine. Flu Season Brings Local Shortages of Oseltamivir. January 22, 2026. https://www.jucm.com/flu-season-brings-local-shortages-of-oseltamivir/
  14. Benist SC, Smith-Jeffcoat SE, Talbot HK, et al. Recent COVID-19 Vaccination and Risk of SARS-CoV-2 Transmission. JAMA Netw Open. 2026;9(5):e2612609. https://doi.org/10.1001/jamanetworkopen.2026.12609
  15. Xocova (ensitrelvir) prescribing information. Shionogi Inc. June 2026. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=526acf60-abc3-2cc2-e063-6294a90affa6
  16. Ng KE, Bradley N. Pharmacists’ Role in Respiratory Syncytial Virus. US Pharm. 2026;51(4):23-26. https://www.uspharmacist.com/article/pharmacists-role-in-respiratory-syncytial-virus
  17. Moulia DL, Link-Gelles R, Chu HY, et al. Use of Clesrovimab for Prevention of Severe Respiratory Syncytial Virus-Associated Lower Respiratory Tract Infections in Infants: Recommendations of the Advisory Committee on Immunization Practices, United States, 2025. MMWR Morb Mortal Wkly Rep. 2025;74(32):508-514. https://www.cdc.gov/mmwr/volumes/74/wr/mm7432a3.htm
  18. CDC. Preventing Spread of Respiratory Viruses When You’re Sick. Updated August 18, 2025. https://www.cdc.gov/respiratory-viruses/prevention/precautions-when-sick.html


Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

Flu vs. COVID Antivirals: Is It Too Late to Take Tamiflu or Paxlovid?

Flu vs. COVID Antivirals: Is It Too Late to Take Tamiflu or Paxlovid?

By the Jase Medical Team

You’ve been sick for three days. The fever isn’t improving, you’re exhausted, and you’re wondering whether an antiviral medication could help. But you’ve heard that antivirals only work if you start them within 48 hours.

So, is it too late? Not necessarily.

The 48-hour window you’ve probably heard about primarily applies to flu treatment in otherwise healthy adults. For people at higher risk of complications, including adults 65 and older, antiviral treatment may still be beneficial after that window. And COVID follows a different timeline altogether.

For flu, the usual treatment window is two days. For COVID, it’s five days for oral antivirals. But your age, health conditions, and severity of illness can change the decision. Here’s what to know before assuming you’ve missed your chance.

Is It Too Late to Take Tamiflu After 48 Hours?

Tamiflu (oseltamivir) is a prescription antiviral used to treat influenza. For otherwise healthy adults with uncomplicated flu, treatment works best when started within 48 hours of symptoms beginning. Clinical trials show that starting oseltamivir early can shorten flu symptoms by approximately one day on average. That might not sound dramatic, but an extra day without fever, body aches, or exhaustion can make a meaningful difference. However, the benefit becomes less certain when an otherwise healthy person starts treatment later.

That doesn’t mean everyone should stop considering Tamiflu after day two.

For people at higher risk of flu complications, the recommendations are different.

Over 65 or Have a Chronic Condition? The 48-Hour Rule Isn’t a Hard Cutoff

If you’re 65 or older, have a chronic medical condition, or are experiencing severe flu symptoms, don’t assume it’s too late for antiviral treatment. The CDC recommends starting antiviral treatment as soon as possible for people who are hospitalized, severely ill, or at higher risk of complications, even when more than 48 hours have passed since symptoms began.

Higher-risk groups include people with:

  • Diabetes
  • Heart disease
  • Chronic lung conditions, including COPD
  • Kidney disease
  • Weakened immune systems
  • Other conditions that increase the risk of severe influenza

Pregnant patients and young children may also be at increased risk. For these individuals, the goal isn’t simply to shorten symptoms. It’s to reduce the likelihood of serious complications. Research suggests antiviral treatment can improve outcomes in certain high-risk and hospitalized patients, particularly when started early. However, evidence that oseltamivir prevents hospitalization in otherwise healthy outpatients is less conclusive.

The takeaway: If you’re at higher risk, call your healthcare provider even if you’ve already been sick for three or four days.

A clinician can determine whether treatment is still appropriate.

Do You Need a Positive Flu Test Before Starting Tamiflu?

Not always. If influenza is circulating in your community and your symptoms strongly suggest flu, your healthcare provider may recommend antiviral treatment without waiting for test results. This is especially important for people at higher risk of complications. Waiting for a test result can delay treatment during the period when antivirals are most effective. That doesn’t mean you should diagnose yourself or begin taking leftover medication. It means your healthcare provider may make a treatment decision based on your symptoms, exposure history, risk factors, and the likelihood of influenza.

If you’re at higher risk, contact your provider promptly rather than waiting several days to confirm the diagnosis.

Paxlovid Has a Different Clock: Five Days, Not Two

COVID antivirals follow a different treatment timeline. Paxlovid (nirmatrelvir/ritonavir) is a prescription antiviral used to treat mild to moderate COVID-19 in eligible patients at higher risk of progressing to severe illness.

Paxlovid must be started within five days of symptom onset.

That means someone who’s been sick for three days may be outside the usual treatment window for uncomplicated flu but still within the window for COVID treatment.

Other COVID treatment options have their own timelines:

  • Paxlovid: Start within five days of symptom onset.
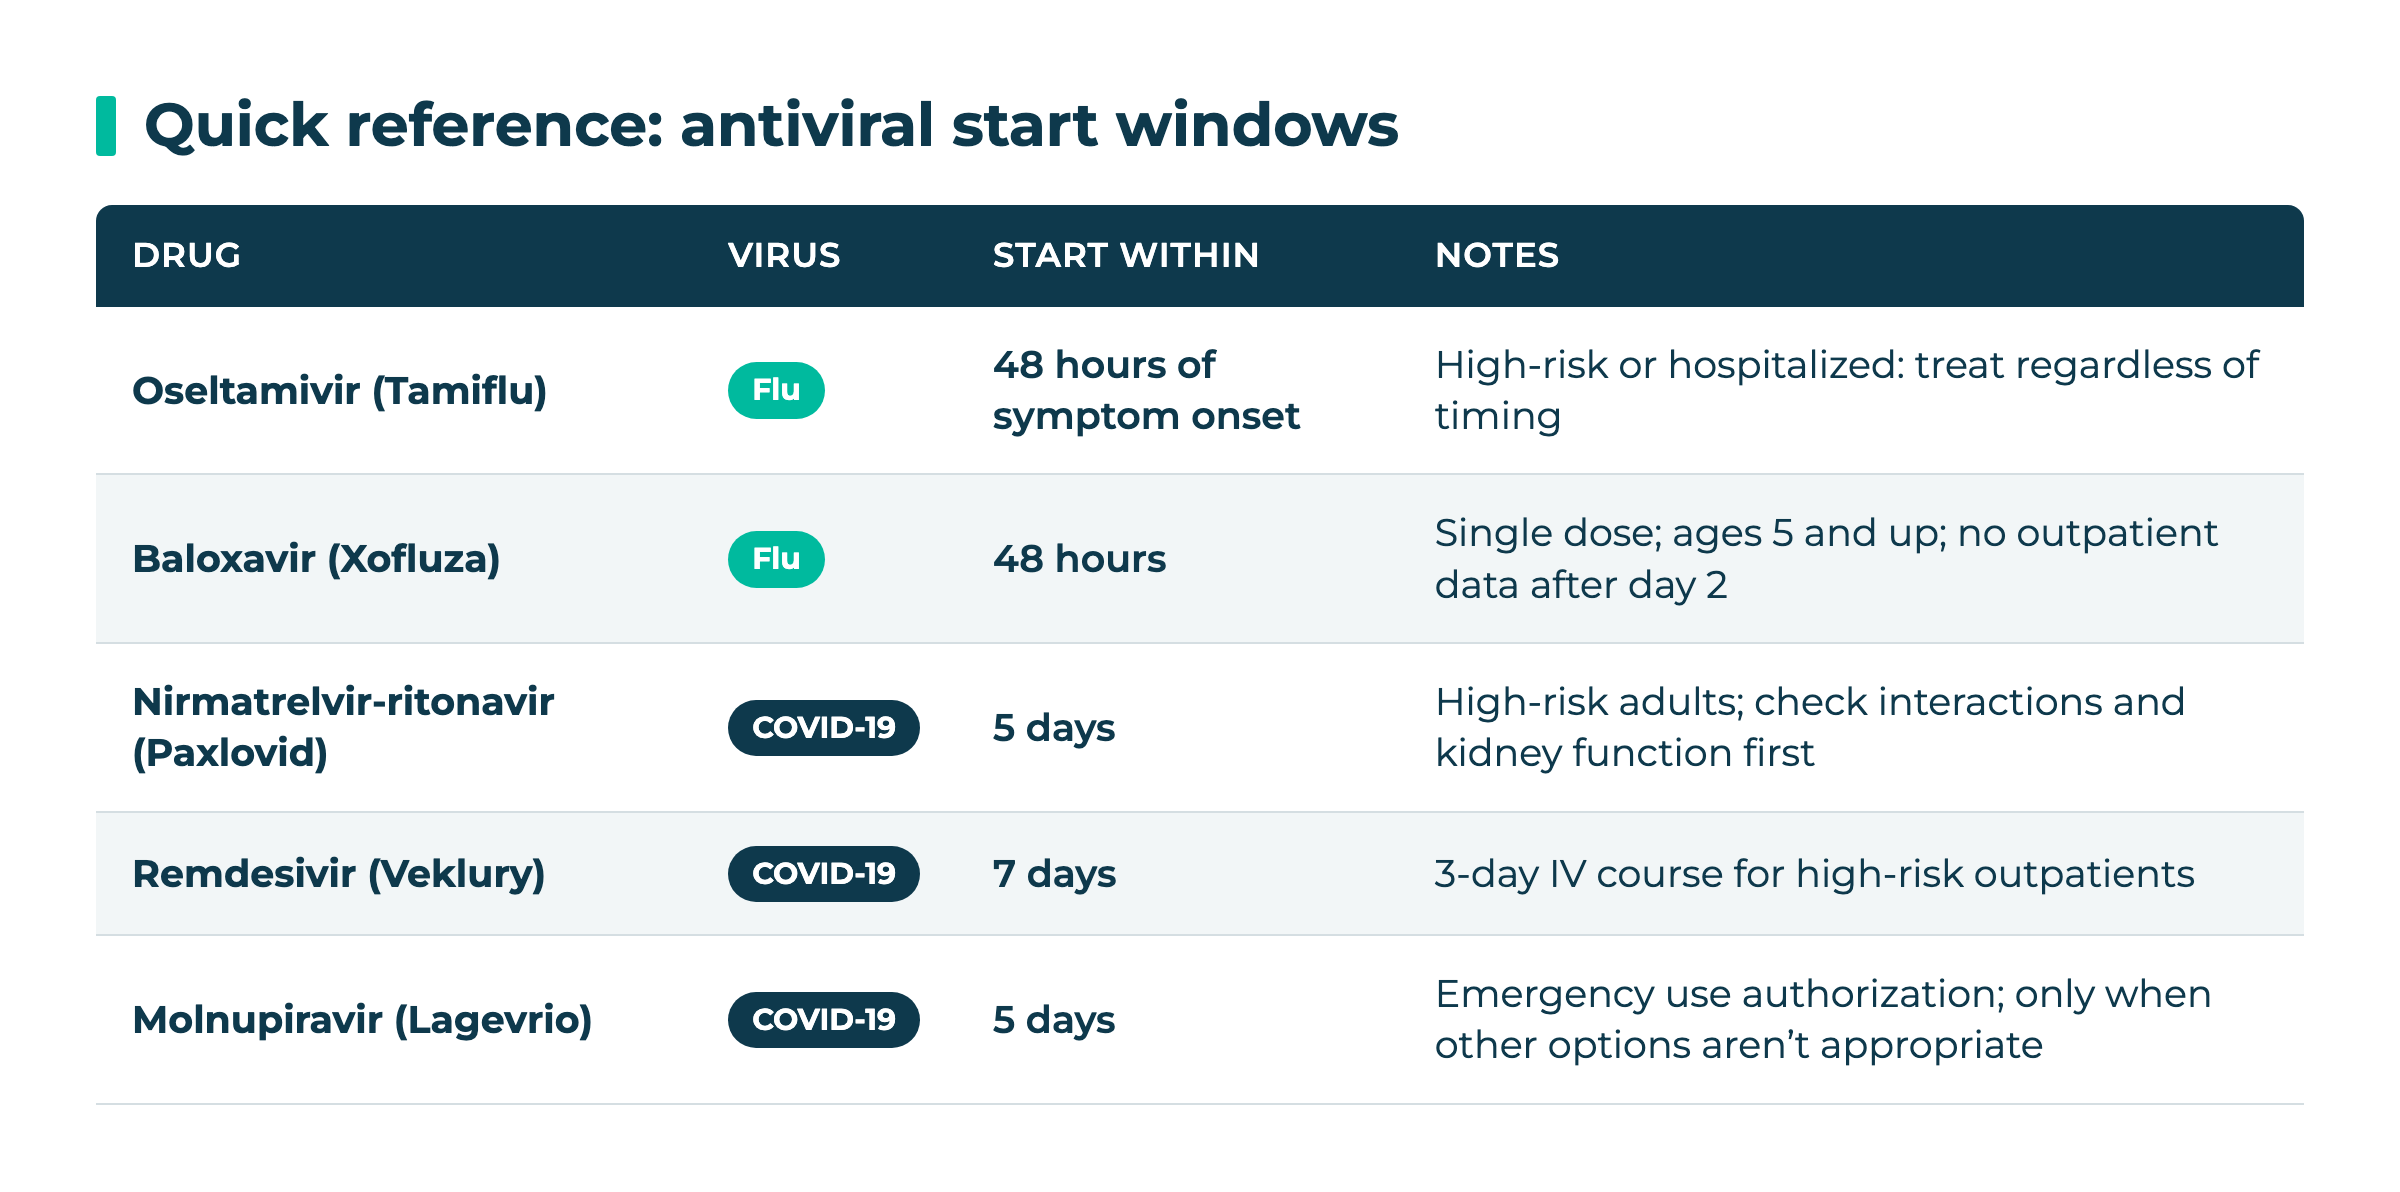
  • Molnupiravir: Start within five days of symptom onset when other appropriate options aren’t accessible or clinically appropriate.
  • Remdesivir: An intravenous antiviral that can be started within seven days of symptom onset for eligible outpatients.

These medications aren’t interchangeable, and each has different eligibility requirements, precautions, and potential benefits.

If you suspect COVID and are at higher risk for severe illness, contact your healthcare provider as soon as symptoms develop.

Why Your Medication List Matters Before Taking Paxlovid

Paxlovid can be highly effective for eligible patients, but it has an important consideration: drug interactions. One of its ingredients, ritonavir, affects how the body processes many common medications. That can create potentially serious interactions with certain prescriptions, including some medications used for heart conditions, cholesterol management, and other chronic health problems. Your healthcare provider or pharmacist needs to review your complete medication list before prescribing Paxlovid. That includes prescription medications, over-the-counter products, and supplements. Kidney function and other medical factors may also affect whether Paxlovid is appropriate or how it’s prescribed.

Don’t stop or adjust your regular medications on your own to make Paxlovid an option. Your healthcare team can determine whether interactions can be safely managed or whether another treatment would be better.

What If You’ve Already Missed the COVID Treatment Window?

If you’ve been sick with COVID for more than five days, Paxlovid is generally not recommended for initiation outside its authorized treatment window. However, that doesn’t mean you should ignore worsening symptoms or assume there are no options. Depending on your circumstances, a healthcare professional may consider other treatments, particularly if you’re severely ill, immunocompromised, or require hospital care. Outpatient remdesivir may be an option within seven days of symptom onset for eligible patients. If you’re experiencing worsening shortness of breath, chest pain, confusion, or other concerning symptoms, seek urgent medical attention.

The important thing is not to make treatment decisions based on the calendar alone.

Flu vs. COVID: Know Which Treatment Window Applies

Here’s a quick comparison of the typical antiviral treatment timelines:

Infection
Medication
Typical treatment window
Influenza
Tamiflu (oseltamivir)
Ideally within 48 hours; later treatment may benefit high-risk or severely ill patients
Influenza
Xofluza (baloxavir)
Within 48 hours for eligible patients
COVID-19
Paxlovid
Within 5 days
COVID-19
Molnupiravir
Within 5 days
COVID-19
Remdesivir
Within 7 days

These timelines are based on when symptoms began, not when you received a positive test. And remember, the flu treatment window isn’t an absolute cutoff for everyone. High-risk patients may still benefit from treatment after 48 hours, particularly with oseltamivir. All antiviral medications require appropriate medical evaluation and prescribing. They should not be started, changed, or used for emergency treatment without first seeking guidance from a qualified healthcare professional.

Medical Preparedness Means Knowing When to Make the Call

When you’re feeling sick, it’s easy to lose track of exactly when symptoms started. But with flu and COVID, that information can affect your treatment options. One of the simplest things you can do is write down the day your symptoms first appeared. If you’re 65 or older or have a chronic medical condition, don’t wait several days hoping symptoms will resolve before contacting your healthcare provider. Ask whether testing or antiviral treatment is appropriate for your situation.

We discussed why timely access to medical care matters during emergencies in our August Jase Medical article on post-disaster disease and treatment delays.

At Jase Medical, our family team of doctors, physician assistants, and pharmacists believes appropriate medical preparation means understanding your treatment options before you’re faced with a time-sensitive decision.

The 48-hour rule isn’t the whole story.

For an otherwise healthy person with flu, early treatment may shorten symptoms by about a day. For someone at higher risk, treatment may still be worthwhile after that window. And for COVID, the timeline for oral antivirals extends to five days. The decision belongs to your healthcare provider, but knowing when to make the call belongs to you.

Don’t assume you’ve missed your chance. Ask.

Medical disclaimer: This article provides general educational information and does not replace individualized medical advice. Antiviral medications require evaluation and prescribing by a qualified healthcare professional. Treatment eligibility depends on your symptoms, medical history, risk factors, medication interactions, and timing. If you have access to an emergency-use antiviral prescription, first attempt to contact a qualified healthcare provider and follow your individualized prescribing instructions. Seek urgent medical care for severe or worsening symptoms.

Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

For Clinicians | Tamiflu After 48 Hours, Paxlovid After 5 Days

For Clinicians | Tamiflu After 48 Hours, Paxlovid After 5 Days: Antiviral Timing for Flu and COVID

By Dr. Jamie Wilkey, PharmD, Director of Clinical Education
Medically reviewed and edited by Kristen Carpenter, PA-C

As the weather turns colder, every retail pharmacist I know is bracing for the Tamiflu rush. Yep, it’s that time again. We’re heading into the season of getting together, which means shared memories…… and a whole lot of shared germs.

I’m writing this early so we can all brush up on current antiviral recommendations before the first patient asks, in the office or at the pharmacy counter, whether it’s too late for Tamiflu. Today we’re covering the 48-hour window, who it actually applies to, why COVID runs on a different clock, and how much these drugs help.

Is it too late to take Tamiflu after 48 hours?

For an otherwise healthy adult, usually yes. The Tamiflu label covers patients who’ve had symptoms for no more than 48 hours¹, and the CDC says healthy outpatients can be treated on clinical judgment if treatment starts within two days of illness onset². We made the short version of this point in our August article on disease after disasters: for flu, a patient doesn’t need a positive test to start treatment. They need a prescriber, and they need to reach one in time.

The 48-hour window comes from how the drug works. Oseltamivir blocks neuraminidase, the enzyme flu needs to spread from an infected cell to healthy ones³, so it can only slow a virus that’s still spreading. In volunteer challenge studies, viral shedding peaked around day two, a day before symptoms hit their worst⁴. By the time a healthy patient feels terrible, the virus is already on its way down.

I know many of my patients have unrealistic expectations for what an antiviral can do. Started on time, Tamiflu gets a typical patient back on their feet about a day sooner¹. That may not sound like much, but ask anyone laid out miserable on the couch with a fever if they’d take one less day of it. So it can shorten the misery, but it isn’t a magical solution that solves a viral illness instantly.

Why doesn’t the 48-hour rule apply to high-risk patients?

For a high-risk patient, the answer does a complete 180: treat them! No matter how long they’ve been sick. CDC recommends antiviral treatment as soon as possible for anyone with suspected or confirmed flu who is hospitalized, has severe, complicated, or progressive illness, or is at higher risk for complications². That last group is way bigger than it sounds because it includes: adults 65 and older, pregnant patients, and anyone with a chronic condition like asthma, diabetes, or heart disease⁵. So now, as I write that out, it feels like half my patient list. Don’t wait on a test, either. A negative rapid test doesn’t rule out flu, and CDC says not to withhold treatment because of one⁶.

And now that we’re talking about high-risk patients please please remember that the goal changes with the patient. In a healthy adult, we’re shaving off a day of misery. In an 80-year-old with heart failure, we’re trying to keep them out of the hospital. And, dang it, the virus doesn’t always work on schedule: critically ill patients can keep replicating the virus longer than healthy patients². The evidence for a late start is observational, not randomized, but it points toward treating².

CDC says even higher-risk patients aren’t always getting prescribed antivirals⁷. So when an older patient asks at the counter, or calls the office on day three, whether it’s too late for Tamiflu, the answer is no. You can still prescribe it, and it can still help.

Why does COVID get 5 days instead of 2?

Because that’s where the trials determined it should be. Paxlovid’s main trial, EPIC-HR, enrolled high-risk patients within 5 days of symptom onset⁸, and the outpatient remdesivir trial enrolled them within 7⁹. COVID also gives us more runway than flu: in early-pandemic data, patients sick enough to be hospitalized usually started struggling to breathe.¹⁰. IDSA’s 2025 update strongly recommends Paxlovid for high-risk adults and keeps molnupiravir as a fallback¹¹.

So a patient on day 3 can be late for Tamiflu and right on time for Paxlovid. And here’s the plot twist: for COVID, you need the test that confirms it is actually COVID. Paxlovid starts after a COVID-19 diagnosis has been made⁸. You can’t pick the drug until you know which virus you’re treating.

Any antiviral a patient keeps on hand is for emergency use only, after first seeking the assistance of a qualified healthcare provider.

What has to be checked before Paxlovid?

Two things. The medication list + the kidneys.

Ritonavir has one job. It blocks CYP3A so the body can’t clear nirmatrelvir as fast, which keeps the antiviral level up⁸. It doesn’t pick favorites, though. It blocks CYP3A for everything else the patient takes, too. The most commonly reported serious interactions involved tacrolimus and cyclosporine, followed by calcium channel blockers⁸, and that last group shows up on a lot of our older patients’ lists. Some conflicts are workable: simvastatin and lovastatin are contraindicated, but they can be held from 12 hours before the first dose until 5 days after the last⁸. St. John’s Wort is on the contraindicated list too, so the medication list you check has to include OTCs and supplements.

Then check renal function. The label reduces the dose when eGFR falls below 60, dialysis included⁸.

How much do antivirals actually help?

Prescribe them for the high-risk patient. And be candid with everyone else about the size of the benefit.

For flu, the clearest benefit is the day of symptoms from earlier. Whether Tamiflu keeps outpatients out of the hospital is less clear: a 2024 meta-analysis of 15 randomized trials found no significant drop in hospitalization, older and high-risk subgroups included¹⁵. That’s why the high-risk recommendation leans on observational data².

For COVID, the gap is immunity. EPIC-HR enrolled only unvaccinated high-risk adults with no prior infection, and Paxlovid cut hospitalization or death from 6.5% to 0.9%⁸. EPIC-SR included vaccinated high-risk adults, and there Paxlovid didn’t shorten symptoms, and the drop in hospitalization or death didn’t reach significance⁸. By late 2022, nearly all US blood donors had antibodies from vaccination, infection, or both¹⁶, so most of our patients today look more like the second trial than the first.

The evidence still points one direction. The benefit is biggest in the patients most likely to end up in the hospital, and those are the patients the 48-hour-or-nothing myth talks us out of treating.

What happens when the patient can’t reach a prescriber in time?

Antiviral care runs all or none. Either the patient reaches a prescriber inside the window, or the clock runs out while they wait for an appointment or for Monday to roll around.

A lot of the clinical work doesn’t need a sick patient, though. You can tell a high-risk patient to call on day one, not day four. You can flag the simvastatin or the tacrolimus that would complicate Paxlovid, and note their kidney function. All of that can happen at a routine visit or a refill call, while everyone’s healthy. That’s the missing middle layer, and it’s what we mean by appropriate medical preparation.

At Jase, we build that layer for the times primary care isn’t there, never as a replacement for it. Tamiflu and Paxlovid are both available as JaseCase add-ons. A licensed provider reviews each request and writes the prescription only when it’s appropriate, and either medication is for emergency use only, after first seeking the assistance of a qualified healthcare provider. If you’d rather not field these requests yourself, you can refer patients to us. We’ll keep publishing the frameworks behind where we draw these lines.

The bottom line

The 48-hour window belongs to healthy outpatients with flu. For a high-risk patient, treat as soon as possible, whatever the day count, and don’t wait on a test. COVID runs on its own clock: 5 days for Paxlovid, after you’ve checked the medication list and the kidneys. The benefit is modest for most patients and biggest for the ones most likely to land in the hospital, so start there. Then go enjoy the holidays…… and wash your hands.

To refer a patient, visit jase.com. A licensed provider reviews every request and writes a prescription only when it’s appropriate.

And a final note from Kristen Carpenter, our PA-C who reviewed this article, “during cold/flu season, the timing is so important to start the medication but there are no appointments in primary care schedules since everyone is sick! The chances of a same day or next day appointment are lower! So having high risk patients prepared ahead of time for these busy seasons can be super helpful!”


Sources

  1. FDA. Tamiflu (oseltamivir phosphate) prescribing information. Genentech; revised August 2019. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=ee3c9555-60f2-4f82-a760-11983c86e97b
  2. CDC. Influenza Antiviral Medications: Summary for Clinicians. Updated March 10, 2026. https://www.cdc.gov/flu/hcp/antivirals/summary-clinicians.html
  3. CDC. Influenza Antiviral Drug Resistance. Updated June 26, 2026. https://www.cdc.gov/flu/treatment/antiviralresistance.html
  4. Carrat F, Vergu E, Ferguson NM, et al. Time lines of infection and disease in human influenza: a review of volunteer challenge studies. Am J Epidemiol. 2008;167(7):775-785. doi:10.1093/aje/kwm375
  5. CDC. People at Increased Risk for Flu Complications. Updated September 11, 2024. https://www.cdc.gov/flu/highrisk/index.htm
  6. CDC. Rapid Influenza Diagnostic Tests. Updated June 22, 2026. https://www.cdc.gov/flu/hcp/testing-methods/clinician_guidance_ridt.html
  7. CDC. Underutilization of Flu Antivirals. March 20, 2026. https://www.cdc.gov/flu/whats-new/2025-2026-underutilization-of-flu-antivirals.html
  8. FDA. Paxlovid (nirmatrelvir tablets; ritonavir tablets) prescribing information. Pfizer; revised January 2025. https://www.accessdata.fda.gov/drugsatfda_docs/label/2025/217188s008lbl.pdf
  9. Gottlieb RL, Vaca CE, Paredes R, et al. Early remdesivir to prevent progression to severe Covid-19 in outpatients. N Engl J Med. 2022;386(4):305-315. doi:10.1056/NEJMoa2116846
  10. Zhou F, Yu T, Du R, et al. Clinical course and risk factors for mortality of adult inpatients with COVID-19 in Wuhan, China: a retrospective cohort study. Lancet. 2020;395(10229):1054-1062. doi:10.1016/S0140-6736(20)30566-3
  11. Shumaker AH, Bhimraj A, et al. 2025 Clinical Practice Guideline Update by the Infectious Diseases Society of America on the Treatment and Management of COVID-19: Antiviral Treatment for Mild to Moderate COVID-19 in Adults. Clin Infect Dis. doi:10.1093/cid/ciaf680. Posted October 14, 2025. Nirmatrelvir/ritonavir for high-risk adults: strong recommendation, moderate certainty of evidence. Molnupiravir when no other options exist: conditional recommendation, low certainty of evidence.
  12. FDA. Xofluza (baloxavir marboxil) prescribing information. Genentech; revised May 2025. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=e49e1a61-1b7c-4be5-ac84-af6240b511e7
  13. FDA. Veklury (remdesivir) prescribing information. Gilead; revised July 2026. https://www.accessdata.fda.gov/drugsatfda_docs/label/2026/214787s033lbl.pdf
  14. FDA. Fact Sheet for Healthcare Providers: Emergency Use Authorization for Lagevrio (molnupiravir) capsules. Revised June 2024. https://www.fda.gov/media/155054/download
  15. Hanula R, Bortolussi-Courval É, Mendel A, et al. Evaluation of oseltamivir used to prevent hospitalization in outpatients with influenza: a systematic review and meta-analysis. JAMA Intern Med. 2024;184(1):18-27. doi:10.1001/jamainternmed.2023.0699
  16. Jones JM, Manrique IM, Stone MS, et al. Estimates of SARS-CoV-2 seroprevalence and incidence of primary SARS-CoV-2 infections among blood donors, by COVID-19 vaccination status: United States, April 2021 to September 2022. MMWR Morb Mortal Wkly Rep. 2023;72(22):601-605. doi:10.15585/mmwr.mm7222a3


Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!