Flu and COVID Prevention for the Holidays: Why Timing Matters
Flu and COVID Prevention for the Holidays: Why Timing Matters

By the Jase Medical Team

The holidays are a time for gathering around the table, catching up with family, and making memories with the people we love.

They’re also a time when respiratory viruses can spread quickly, especially when families travel and multiple generations gather indoors.

If you’re planning to spend Thanksgiving with your children and grandchildren, there’s one important question to ask now:

Will your flu vaccine have enough time to work before everyone arrives?

Preventing flu and COVID isn’t about one perfect precaution. It’s about layering several practical steps together, starting before the holiday season begins.

How Long Does the Flu Shot Take to Work?

It takes approximately two weeks for your body to develop protective antibodies after a flu vaccination.

That means if you’re hoping to have vaccine protection in place for Thanksgiving on November 26, 2026, aim to get your flu shot by November 12.

You can still benefit from vaccination after that date, but your immune system needs time to build protection.

The CDC recommends annual flu vaccination for nearly everyone six months and older, with rare exceptions.

Why every year? Because flu viruses change, and immune protection decreases over time. Each season’s vaccine is designed to protect against viruses expected to circulate.

COVID vaccination also remains an important prevention tool, particularly for older adults and people with underlying medical conditions. Recommendations vary by age, risk factors, vaccination history, and current guidance, so discuss your options with your healthcare provider or pharmacist.

You’re Not Just Protecting Yourself

One of the most meaningful benefits of vaccination is that it can help protect the people around you.

Research has shown that vaccinating children against influenza can reduce infections among unvaccinated members of their communities. Other studies have found that recent COVID vaccination can reduce the likelihood of transmitting the virus within a household, although that protection decreases over time.

When more people around the holiday table are protected, vulnerable family members may benefit too.

That matters especially for grandparents, infants, and loved ones living with heart disease, diabetes, lung disease, or weakened immune systems.

Vaccination isn’t a guarantee that you won’t get sick. But it can reduce your risk of infection and, importantly, lower the likelihood of severe illness, hospitalization, and serious complications.

For older adults, that protection can make a significant difference.

What If Someone Tests Positive Before Thanksgiving?

Imagine you’re preparing for a family gathering when your grandson develops a fever and tests positive for influenza.

Or you learn that someone you spent yesterday afternoon with has COVID.

Should you wait to see whether symptoms develop?

If you’re at higher risk for complications, contact your healthcare provider promptly after a known exposure.

There are prescription antiviral medications that may help prevent certain infections after exposure, but they are not appropriate for everyone.

Flu: Prevention After Exposure

For influenza, medications such as oseltamivir (Tamiflu) and baloxavir (Xofluza) may be prescribed for post-exposure prevention in certain circumstances.

When prescribed for this purpose, timing is important. Preventive treatment is generally considered within 48 hours after the relevant exposure.

Your healthcare provider will consider factors such as your age, medical history, vaccination status, and the nature of the exposure before recommending medication.

COVID: Ask About Current Prevention and Treatment Options

COVID prevention and treatment options continue to evolve.

Prescription antivirals may be appropriate for certain patients, but medications used to treat an active COVID infection are not necessarily approved or recommended to prevent infection after exposure.

If you’ve been exposed to COVID, especially if you’re 65 or older or have a chronic medical condition, contact your healthcare provider to discuss current options, testing, and the symptoms to monitor.

Don’t start prescription antivirals on your own or use medications prescribed for someone else. A qualified healthcare professional should determine whether preventive or therapeutic treatment is appropriate.

Three Simple Ways to Protect Your Holiday Gathering

Vaccination and prescription medications aren’t the only tools available.

A few everyday precautions can reduce the likelihood of spreading respiratory viruses.

1. Stay home when you’re sick. If you have a fever, cough, sore throat, or other respiratory symptoms, don’t assume it’s just a cold. Follow current public health guidance for staying home and returning to normal activities.

2. Consider testing before visiting someone at high risk. A COVID test before gathering with an older relative or someone with a weakened immune system can provide useful information. Remember that a negative rapid test doesn’t completely rule out infection.

3. Improve indoor airflow. Opening windows when practical, using effective air filtration, and spending time outdoors can help reduce the concentration of airborne respiratory viruses.

These precautions are especially valuable when someone at your gathering has a higher risk of serious illness.

Medical Preparedness Starts Before the Holiday

Most people think about medical preparedness in terms of emergency supplies, medications, and what to do when healthcare becomes difficult to access.

But preparation also means taking steps to prevent illness before it happens.

For flu and COVID, that includes knowing when to get vaccinated, understanding your personal risk factors, and having a plan for what to do after an exposure.

If you’re traveling this holiday season, consider discussing these questions with your healthcare provider:

  • Am I up to date on the vaccines recommended for me?
  • Am I at higher risk for complications from flu or COVID?
  • If I’m exposed or develop symptoms while traveling, when should I contact a healthcare professional?
  • Are there prescription treatments or preventive options appropriate for my medical history?

At Jase Medical, our family team of doctors, PAs, and pharmacists believes appropriate medical preparation begins with informed decisions made before an emergency.

The goal isn’t to eliminate every risk. It’s to make it easier for everyone around the table to enjoy the holidays safely.

So before the turkey goes in the oven and the family starts arriving, take a moment to review your vaccination status and make a plan.

A little preparation now can help protect the people who make the holidays worth celebrating.

Medical disclaimer: This article provides general educational information and does not replace individualized medical advice. Vaccination and antiviral recommendations depend on personal health factors and current clinical guidance. Prescription antivirals should only be used following evaluation and authorization by a qualified healthcare professional. If you develop symptoms after an exposure, contact your healthcare provider promptly, especially if you’re at increased risk for severe illness.

Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.
Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

For Clinicians | How Long Does the Flu Shot Take to Work? Holiday Flu Prevention

For Clinicians | How Long Does the Flu Shot Take to Work? Holiday Flu Prevention

By Dr. Jamie Wilkey, PharmD, Director of Clinical Education
Medically reviewed and edited by Kristen Carpenter, PA-C

Hi again, everyone. Last week I had a lot of fun writing about flu treatment, but the whole time I was writing it, I felt like half the story was missing. Treating the flu is one thing. Not getting it in the first place is even better. I’m a girl who loves preventative medicine and will do just about anything to keep sickness out of my house. So today we’re talking flu prevention, because everyone’s looking at the calendar and seeing Thanksgiving right around the corner. This is the season of getting together with family from all over the country, and we’ll cover when the shot needs to happen, what to do when someone at the table tests positive, and where COVID and RSV fit into the same season.

A couple of Sundays ago, I was sitting next to one of my good friends at church, and we got to talking about shots. We both agreed we hate getting vaccines. We’re also strict about getting them every single year, because we love preventing sickness, for ourselves and for the herd immunity of everyone around us. I already gave my family their flu and COVID shots, so we’re all ready to go for this season. This isn’t something I’m just preaching. It’s something I’m doing for my own family.

How long does the flu shot take to work?

About two weeks. Flu vaccines cause antibodies to develop about two weeks after vaccination¹, so protection at Thanksgiving dinner on November 26 means a shot by November 12. Yep, that’s this week!!

The end of October was CDC’s ideal¹, but it isn’t too late, and we keep offering the shot as long as flu is circulating². Bring it up at every visit and refill call this week, in the office or at the pharmacy counter.

For patients 65 and up, reach for an enhanced vaccine: high-dose, adjuvanted, recombinant, or mRNA². If none of those is on the shelf, give the standard shot rather than wait³.

And for the patient who says the flu shot never works for them anyway that’s a great time to remind them that even when it doesn’t stop the infection, vaccinated adults hospitalized with flu are far less likely to end up in the ICU⁴.

Does the flu shot protect the people around your patient?

It can, and that’s the herd immunity my friend and I were talking about. In a cluster-randomized trial in Hutterite colonies in Canada, vaccinating the kids cut confirmed flu by 61% among the community members who didn’t get the study vaccine⁵. Kids bring flu home, so protecting them protects the people they live with.

CDC is a little more careful, saying a shot “may also protect people around you”⁴. The protection doesn’t last forever: immunity wanes and the virus changes every season, which is why this is a yearly shot.

So when a patient tells you they never get the flu and don’t need it, that’s the moment to remind them the shot isn’t only for them. It’s for the grandparent flying in for Thanksgiving and the baby too young for a flu shot of their own¹.

What should happen after a flu exposure?

Tell your high-risk patients to call the same day someone at the gathering tests positive. They need to call that day, not when they start feeling a fever come on 2-3 days later. That day.

Prevention after an exposure is based on the exposure clock, not the symptom clock:

  • Oseltamivir (Tamiflu): start within 48 hours of close contact⁶.
  • Baloxavir (Xofluza): a single dose within 48 hours of contact, for ages 5 and up⁷.

Once symptoms start, it’s a treatment question.

But alas, that’s not so easy over the next couple of months because it is a holiday problem. If someone coughs through Thursday’s turkey, tests positive Friday morning, and the 48-hour window closes Saturday night…that’s all happening on a holiday weekend when most offices are closed.

Prevention after exposure works. In the Tamiflu household trial, confirmed flu dropped from 12% to 1% in the contacts who took it⁶. The patients who most need that same-day call are the ones flu hits hardest: adults 65 and up, pregnant patients, and anyone with a chronic condition like asthma, diabetes, or heart disease⁸. 

And in case you were feeling like, well, it’s way easier to just take Tamiflu than get a shot…. it’s no substitute for the shot⁶. It’s not always easy to get, either. Generic oseltamivir is the cheap one, around $22 to $55 for a 10-capsule box, depending on the pharmacy and whether there’s a discount card⁹. Xofluza is brand-only, about $170 to $250 cash for a single dose¹⁰.  Insurance usually puts quantity limits on oseltamivir, so a prevention course can eat into what the plan covers for treatment later in the season, and Xofluza often needs a prior authorization first¹¹,¹².

And pharmacies run out during the holiday rush (I know, because I worked in one for years and we almost always ran out). Last January, ASHP listed some oseltamivir capsules and powders in short supply from local stockouts driven by demand¹³. Check stock before you send the prescription.

COVID and RSV should be considered too!
Flu is the one on everyone’s mind, but COVID and RSV travel to the same gatherings.

For COVID, AAFP recommends an updated vaccine for every adult this season, with two doses six months apart at 65 and up². A shot in the past six months also cut spread to household members by about 43%, and the effect was no longer measurable by month seven¹⁴. After an exposure, there’s now a pill for COVID too: ensitrelvir (Xocova), approved in late May for ages 12 and up and started within 72 hours of contact¹⁵. It’s a strong CYP3A inhibitor, so check the full medication list and pregnancy status first. Paxlovid is still treatment only, started within 5 days of symptoms.

For RSV, AAFP recommends a single dose for those ages 75 and up, and at 50 to 74 for anyone at increased risk². There’s no pill after an RSV exposure, and treatment is mostly supportive¹⁶, so the shot is the prevention. Babies get theirs through the maternal vaccine or an infant antibody¹⁷.

What else keeps patients well at holiday gatherings?

If someone’s sick, they stay home until they’ve gone 24 hours with symptoms getting better and no fever, without fever reducers¹⁸. For five days after that, CDC suggests extra care: cleaner air, good hygiene, a mask, some distance, and a test before being around others, especially anyone at higher risk¹⁸. Not fancy or expensive, but it works: a cracked window, clean hands, and a negative test before the hugs start.

Why plan before the gathering?

Prevention after an exposure runs all or none: the call reaches a prescriber inside 48 hours AND medication is readily available from a pharmacy, or the window closes somewhere between the leftovers and Saturday night. Most of the work can happen before anyone’s sick, though: the shot by November 12, a high-risk patient who knows to call the same day, and a written list of everything they take, supplements included. On a holiday weekend, the prescriber who picks up the phone may never have met them, and the COVID antivirals interact with a long list of common drugs. That right there is appropriate medical preparation.

At Jase, we build that layer for the times primary care isn’t there, never as a replacement for it. If you’d rather not field these calls over a holiday weekend, you can refer patients to us. A licensed provider reviews every request, and Tamiflu and Paxlovid are available as JaseCase add-ons for treatment, for emergency use only, after first seeking the assistance of a qualified healthcare provider. 

The bottom line

Get flu shots in by November 12, with an enhanced vaccine at 65 and up, and keep COVID and RSV vaccines in the same conversation. Tell high-risk patients to call the same day someone at the gathering tests positive. Then go enjoy the pie.

To refer a patient, visit jase.com. A licensed provider reviews every request and writes a prescription only when it’s appropriate.


Sources

  1. CDC. Key Facts About Seasonal Flu Vaccine. Updated September 1, 2026. https://www.cdc.gov/flu/vaccines/keyfacts.html
  2. Lin KW. Practice Alert: AAFP 2026–2027 Respiratory Vaccine Recommendations for Adults. Am Fam Physician. 2026;114(4):333-335. https://www.aafp.org/afp/2026/1000/editorials-respiratory-vaccine-recommendations-adults
  3. CDC. Prevention and Control of Seasonal Influenza with Vaccines: Recommendations of the Advisory Committee on Immunization Practices, United States, 2025-26 Influenza Season. Summary of Recommendations. MMWR 2025;74(32):500-507. https://www.cdc.gov/flu/media/pdfs/2025-2026-summary-of-recommendations.pdf
  4. CDC. Benefits of Flu Vaccination. May 28, 2026. https://www.cdc.gov/flu-vaccines-work/benefits/
  5. Loeb M, Russell ML, Moss L, et al. Effect of influenza vaccination of children on infection rates in Hutterite communities: a randomized trial. JAMA. 2010;303(10):943-950. https://doi.org/10.1001/jama.2010.250
  6. Tamiflu (oseltamivir phosphate) prescribing information. Genentech, Inc. Revised December 2025. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=ee3c9555-60f2-4f82-a760-11983c86e97b
  7. CDC. Influenza Antiviral Medications: Summary for Clinicians. Updated March 10, 2026. https://www.cdc.gov/flu/hcp/antivirals/summary-clinicians.html
  8. CDC. People at Increased Risk for Flu Complications. September 11, 2024. https://www.cdc.gov/flu/highrisk/index.htm
  9. GoodRx. Oseltamivir prices, 75 mg, 10 capsules. Accessed October 26, 2026. Prices vary by location and pharmacy. https://www.goodrx.com/oseltamivir
  10. SingleCare. Xofluza coupons and prices, 40 mg tablet. Accessed October 26, 2026. Prices vary by location and pharmacy. https://www.singlecare.com/prescription/xofluza
  11. Prime Therapeutics for Blue Cross and Blue Shield of Minnesota. Anti-Influenza Agents Quantity Limit Program Summary. Effective November 1, 2025. https://bluecrossmn.com/sites/default/files/DAM/2022-09/MN_PS_Anti-Influenza_Agent_QL_ProgSum_AR0621_r0721.pdf
  12. Blue Cross Blue Shield Association, Federal Employee Program. Xofluza, policy 5.01.049. Effective July 1, 2026. https://www.fepblue.org/-/media/PDFs/Medical-Policies/2026/July-2026/Pharmacy-Policies/Remove–Replace/501049-Xofluza-baloxavir-marboxil.pdf
  13. Journal of Urgent Care Medicine. Flu Season Brings Local Shortages of Oseltamivir. January 22, 2026. https://www.jucm.com/flu-season-brings-local-shortages-of-oseltamivir/
  14. Benist SC, Smith-Jeffcoat SE, Talbot HK, et al. Recent COVID-19 Vaccination and Risk of SARS-CoV-2 Transmission. JAMA Netw Open. 2026;9(5):e2612609. https://doi.org/10.1001/jamanetworkopen.2026.12609
  15. Xocova (ensitrelvir) prescribing information. Shionogi Inc. June 2026. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=526acf60-abc3-2cc2-e063-6294a90affa6
  16. Ng KE, Bradley N. Pharmacists’ Role in Respiratory Syncytial Virus. US Pharm. 2026;51(4):23-26. https://www.uspharmacist.com/article/pharmacists-role-in-respiratory-syncytial-virus
  17. Moulia DL, Link-Gelles R, Chu HY, et al. Use of Clesrovimab for Prevention of Severe Respiratory Syncytial Virus-Associated Lower Respiratory Tract Infections in Infants: Recommendations of the Advisory Committee on Immunization Practices, United States, 2025. MMWR Morb Mortal Wkly Rep. 2025;74(32):508-514. https://www.cdc.gov/mmwr/volumes/74/wr/mm7432a3.htm
  18. CDC. Preventing Spread of Respiratory Viruses When You’re Sick. Updated August 18, 2025. https://www.cdc.gov/respiratory-viruses/prevention/precautions-when-sick.html


Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

Flu vs. COVID Antivirals: Is It Too Late to Take Tamiflu or Paxlovid?

Flu vs. COVID Antivirals: Is It Too Late to Take Tamiflu or Paxlovid?

By the Jase Medical Team

You’ve been sick for three days. The fever isn’t improving, you’re exhausted, and you’re wondering whether an antiviral medication could help. But you’ve heard that antivirals only work if you start them within 48 hours.

So, is it too late? Not necessarily.

The 48-hour window you’ve probably heard about primarily applies to flu treatment in otherwise healthy adults. For people at higher risk of complications, including adults 65 and older, antiviral treatment may still be beneficial after that window. And COVID follows a different timeline altogether.

For flu, the usual treatment window is two days. For COVID, it’s five days for oral antivirals. But your age, health conditions, and severity of illness can change the decision. Here’s what to know before assuming you’ve missed your chance.

Is It Too Late to Take Tamiflu After 48 Hours?

Tamiflu (oseltamivir) is a prescription antiviral used to treat influenza. For otherwise healthy adults with uncomplicated flu, treatment works best when started within 48 hours of symptoms beginning. Clinical trials show that starting oseltamivir early can shorten flu symptoms by approximately one day on average. That might not sound dramatic, but an extra day without fever, body aches, or exhaustion can make a meaningful difference. However, the benefit becomes less certain when an otherwise healthy person starts treatment later.

That doesn’t mean everyone should stop considering Tamiflu after day two.

For people at higher risk of flu complications, the recommendations are different.

Over 65 or Have a Chronic Condition? The 48-Hour Rule Isn’t a Hard Cutoff

If you’re 65 or older, have a chronic medical condition, or are experiencing severe flu symptoms, don’t assume it’s too late for antiviral treatment. The CDC recommends starting antiviral treatment as soon as possible for people who are hospitalized, severely ill, or at higher risk of complications, even when more than 48 hours have passed since symptoms began.

Higher-risk groups include people with:

  • Diabetes
  • Heart disease
  • Chronic lung conditions, including COPD
  • Kidney disease
  • Weakened immune systems
  • Other conditions that increase the risk of severe influenza

Pregnant patients and young children may also be at increased risk. For these individuals, the goal isn’t simply to shorten symptoms. It’s to reduce the likelihood of serious complications. Research suggests antiviral treatment can improve outcomes in certain high-risk and hospitalized patients, particularly when started early. However, evidence that oseltamivir prevents hospitalization in otherwise healthy outpatients is less conclusive.

The takeaway: If you’re at higher risk, call your healthcare provider even if you’ve already been sick for three or four days.

A clinician can determine whether treatment is still appropriate.

Do You Need a Positive Flu Test Before Starting Tamiflu?

Not always. If influenza is circulating in your community and your symptoms strongly suggest flu, your healthcare provider may recommend antiviral treatment without waiting for test results. This is especially important for people at higher risk of complications. Waiting for a test result can delay treatment during the period when antivirals are most effective. That doesn’t mean you should diagnose yourself or begin taking leftover medication. It means your healthcare provider may make a treatment decision based on your symptoms, exposure history, risk factors, and the likelihood of influenza.

If you’re at higher risk, contact your provider promptly rather than waiting several days to confirm the diagnosis.

Paxlovid Has a Different Clock: Five Days, Not Two

COVID antivirals follow a different treatment timeline. Paxlovid (nirmatrelvir/ritonavir) is a prescription antiviral used to treat mild to moderate COVID-19 in eligible patients at higher risk of progressing to severe illness.

Paxlovid must be started within five days of symptom onset.

That means someone who’s been sick for three days may be outside the usual treatment window for uncomplicated flu but still within the window for COVID treatment.

Other COVID treatment options have their own timelines:

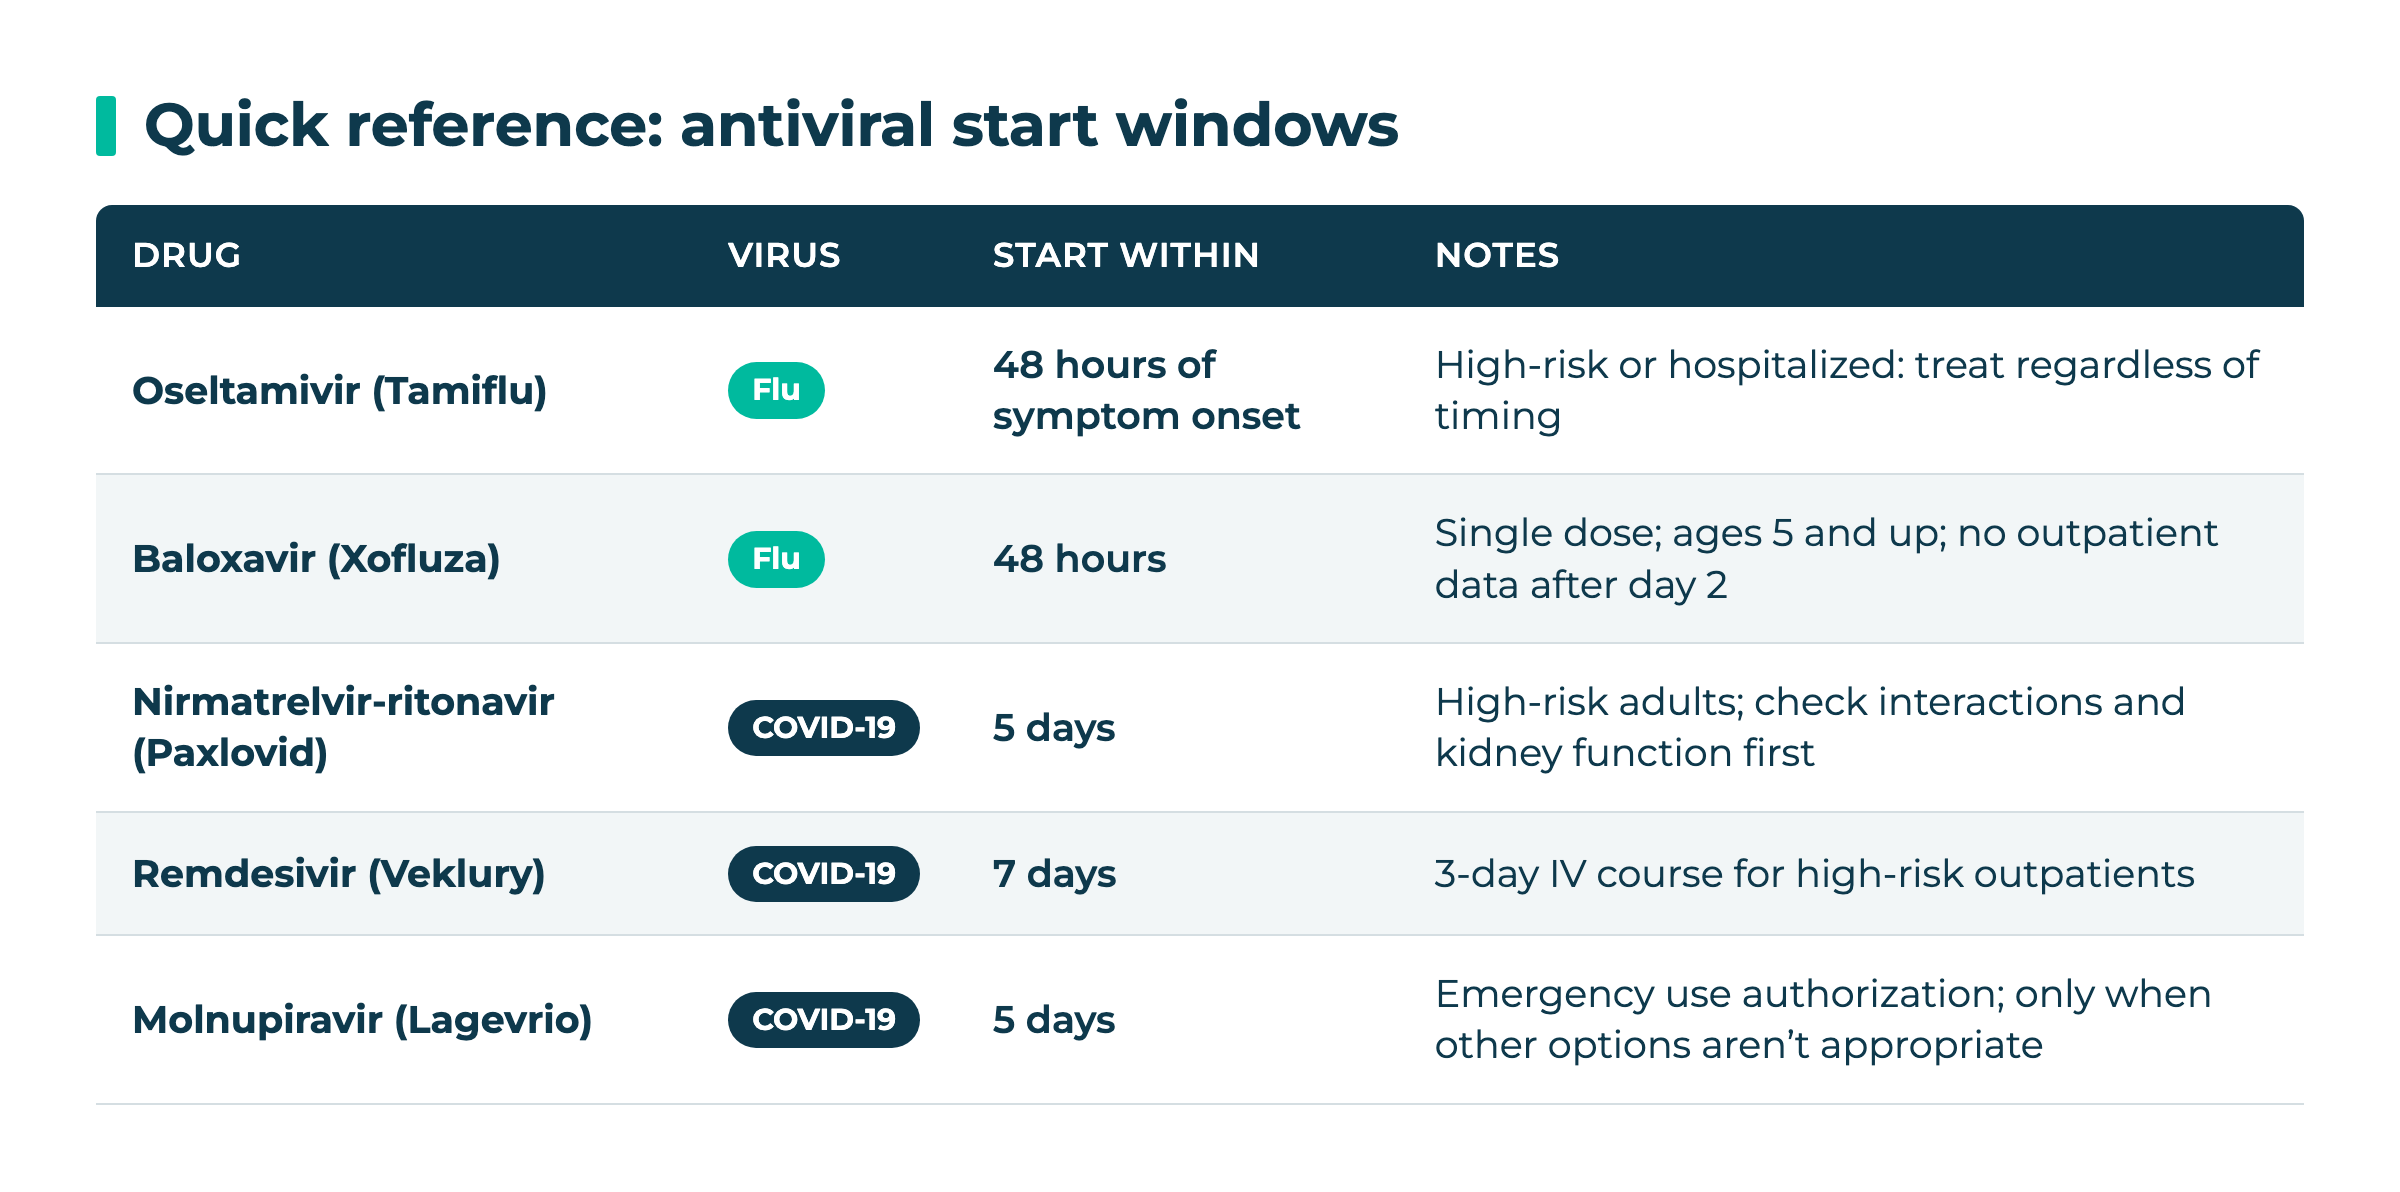
  • Paxlovid: Start within five days of symptom onset.
  • Molnupiravir: Start within five days of symptom onset when other appropriate options aren’t accessible or clinically appropriate.
  • Remdesivir: An intravenous antiviral that can be started within seven days of symptom onset for eligible outpatients.

These medications aren’t interchangeable, and each has different eligibility requirements, precautions, and potential benefits.

If you suspect COVID and are at higher risk for severe illness, contact your healthcare provider as soon as symptoms develop.

Why Your Medication List Matters Before Taking Paxlovid

Paxlovid can be highly effective for eligible patients, but it has an important consideration: drug interactions. One of its ingredients, ritonavir, affects how the body processes many common medications. That can create potentially serious interactions with certain prescriptions, including some medications used for heart conditions, cholesterol management, and other chronic health problems. Your healthcare provider or pharmacist needs to review your complete medication list before prescribing Paxlovid. That includes prescription medications, over-the-counter products, and supplements. Kidney function and other medical factors may also affect whether Paxlovid is appropriate or how it’s prescribed.

Don’t stop or adjust your regular medications on your own to make Paxlovid an option. Your healthcare team can determine whether interactions can be safely managed or whether another treatment would be better.

What If You’ve Already Missed the COVID Treatment Window?

If you’ve been sick with COVID for more than five days, Paxlovid is generally not recommended for initiation outside its authorized treatment window. However, that doesn’t mean you should ignore worsening symptoms or assume there are no options. Depending on your circumstances, a healthcare professional may consider other treatments, particularly if you’re severely ill, immunocompromised, or require hospital care. Outpatient remdesivir may be an option within seven days of symptom onset for eligible patients. If you’re experiencing worsening shortness of breath, chest pain, confusion, or other concerning symptoms, seek urgent medical attention.

The important thing is not to make treatment decisions based on the calendar alone.

Flu vs. COVID: Know Which Treatment Window Applies

Here’s a quick comparison of the typical antiviral treatment timelines:

Infection
Medication
Typical treatment window
Influenza
Tamiflu (oseltamivir)
Ideally within 48 hours; later treatment may benefit high-risk or severely ill patients
Influenza
Xofluza (baloxavir)
Within 48 hours for eligible patients
COVID-19
Paxlovid
Within 5 days
COVID-19
Molnupiravir
Within 5 days
COVID-19
Remdesivir
Within 7 days

These timelines are based on when symptoms began, not when you received a positive test. And remember, the flu treatment window isn’t an absolute cutoff for everyone. High-risk patients may still benefit from treatment after 48 hours, particularly with oseltamivir. All antiviral medications require appropriate medical evaluation and prescribing. They should not be started, changed, or used for emergency treatment without first seeking guidance from a qualified healthcare professional.

Medical Preparedness Means Knowing When to Make the Call

When you’re feeling sick, it’s easy to lose track of exactly when symptoms started. But with flu and COVID, that information can affect your treatment options. One of the simplest things you can do is write down the day your symptoms first appeared. If you’re 65 or older or have a chronic medical condition, don’t wait several days hoping symptoms will resolve before contacting your healthcare provider. Ask whether testing or antiviral treatment is appropriate for your situation.

We discussed why timely access to medical care matters during emergencies in our August Jase Medical article on post-disaster disease and treatment delays.

At Jase Medical, our family team of doctors, physician assistants, and pharmacists believes appropriate medical preparation means understanding your treatment options before you’re faced with a time-sensitive decision.

The 48-hour rule isn’t the whole story.

For an otherwise healthy person with flu, early treatment may shorten symptoms by about a day. For someone at higher risk, treatment may still be worthwhile after that window. And for COVID, the timeline for oral antivirals extends to five days. The decision belongs to your healthcare provider, but knowing when to make the call belongs to you.

Don’t assume you’ve missed your chance. Ask.

Medical disclaimer: This article provides general educational information and does not replace individualized medical advice. Antiviral medications require evaluation and prescribing by a qualified healthcare professional. Treatment eligibility depends on your symptoms, medical history, risk factors, medication interactions, and timing. If you have access to an emergency-use antiviral prescription, first attempt to contact a qualified healthcare provider and follow your individualized prescribing instructions. Seek urgent medical care for severe or worsening symptoms.

Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

For Clinicians | Tamiflu After 48 Hours, Paxlovid After 5 Days

For Clinicians | Tamiflu After 48 Hours, Paxlovid After 5 Days: Antiviral Timing for Flu and COVID

By Dr. Jamie Wilkey, PharmD, Director of Clinical Education
Medically reviewed and edited by Kristen Carpenter, PA-C

As the weather turns colder, every retail pharmacist I know is bracing for the Tamiflu rush. Yep, it’s that time again. We’re heading into the season of getting together, which means shared memories…… and a whole lot of shared germs.

I’m writing this early so we can all brush up on current antiviral recommendations before the first patient asks, in the office or at the pharmacy counter, whether it’s too late for Tamiflu. Today we’re covering the 48-hour window, who it actually applies to, why COVID runs on a different clock, and how much these drugs help.

Is it too late to take Tamiflu after 48 hours?

For an otherwise healthy adult, usually yes. The Tamiflu label covers patients who’ve had symptoms for no more than 48 hours¹, and the CDC says healthy outpatients can be treated on clinical judgment if treatment starts within two days of illness onset². We made the short version of this point in our August article on disease after disasters: for flu, a patient doesn’t need a positive test to start treatment. They need a prescriber, and they need to reach one in time.

The 48-hour window comes from how the drug works. Oseltamivir blocks neuraminidase, the enzyme flu needs to spread from an infected cell to healthy ones³, so it can only slow a virus that’s still spreading. In volunteer challenge studies, viral shedding peaked around day two, a day before symptoms hit their worst⁴. By the time a healthy patient feels terrible, the virus is already on its way down.

I know many of my patients have unrealistic expectations for what an antiviral can do. Started on time, Tamiflu gets a typical patient back on their feet about a day sooner¹. That may not sound like much, but ask anyone laid out miserable on the couch with a fever if they’d take one less day of it. So it can shorten the misery, but it isn’t a magical solution that solves a viral illness instantly.

Why doesn’t the 48-hour rule apply to high-risk patients?

For a high-risk patient, the answer does a complete 180: treat them! No matter how long they’ve been sick. CDC recommends antiviral treatment as soon as possible for anyone with suspected or confirmed flu who is hospitalized, has severe, complicated, or progressive illness, or is at higher risk for complications². That last group is way bigger than it sounds because it includes: adults 65 and older, pregnant patients, and anyone with a chronic condition like asthma, diabetes, or heart disease⁵. So now, as I write that out, it feels like half my patient list. Don’t wait on a test, either. A negative rapid test doesn’t rule out flu, and CDC says not to withhold treatment because of one⁶.

And now that we’re talking about high-risk patients please please remember that the goal changes with the patient. In a healthy adult, we’re shaving off a day of misery. In an 80-year-old with heart failure, we’re trying to keep them out of the hospital. And, dang it, the virus doesn’t always work on schedule: critically ill patients can keep replicating the virus longer than healthy patients². The evidence for a late start is observational, not randomized, but it points toward treating².

CDC says even higher-risk patients aren’t always getting prescribed antivirals⁷. So when an older patient asks at the counter, or calls the office on day three, whether it’s too late for Tamiflu, the answer is no. You can still prescribe it, and it can still help.

Why does COVID get 5 days instead of 2?

Because that’s where the trials determined it should be. Paxlovid’s main trial, EPIC-HR, enrolled high-risk patients within 5 days of symptom onset⁸, and the outpatient remdesivir trial enrolled them within 7⁹. COVID also gives us more runway than flu: in early-pandemic data, patients sick enough to be hospitalized usually started struggling to breathe.¹⁰. IDSA’s 2025 update strongly recommends Paxlovid for high-risk adults and keeps molnupiravir as a fallback¹¹.

So a patient on day 3 can be late for Tamiflu and right on time for Paxlovid. And here’s the plot twist: for COVID, you need the test that confirms it is actually COVID. Paxlovid starts after a COVID-19 diagnosis has been made⁸. You can’t pick the drug until you know which virus you’re treating.

Any antiviral a patient keeps on hand is for emergency use only, after first seeking the assistance of a qualified healthcare provider.

What has to be checked before Paxlovid?

Two things. The medication list + the kidneys.

Ritonavir has one job. It blocks CYP3A so the body can’t clear nirmatrelvir as fast, which keeps the antiviral level up⁸. It doesn’t pick favorites, though. It blocks CYP3A for everything else the patient takes, too. The most commonly reported serious interactions involved tacrolimus and cyclosporine, followed by calcium channel blockers⁸, and that last group shows up on a lot of our older patients’ lists. Some conflicts are workable: simvastatin and lovastatin are contraindicated, but they can be held from 12 hours before the first dose until 5 days after the last⁸. St. John’s Wort is on the contraindicated list too, so the medication list you check has to include OTCs and supplements.

Then check renal function. The label reduces the dose when eGFR falls below 60, dialysis included⁸.

How much do antivirals actually help?

Prescribe them for the high-risk patient. And be candid with everyone else about the size of the benefit.

For flu, the clearest benefit is the day of symptoms from earlier. Whether Tamiflu keeps outpatients out of the hospital is less clear: a 2024 meta-analysis of 15 randomized trials found no significant drop in hospitalization, older and high-risk subgroups included¹⁵. That’s why the high-risk recommendation leans on observational data².

For COVID, the gap is immunity. EPIC-HR enrolled only unvaccinated high-risk adults with no prior infection, and Paxlovid cut hospitalization or death from 6.5% to 0.9%⁸. EPIC-SR included vaccinated high-risk adults, and there Paxlovid didn’t shorten symptoms, and the drop in hospitalization or death didn’t reach significance⁸. By late 2022, nearly all US blood donors had antibodies from vaccination, infection, or both¹⁶, so most of our patients today look more like the second trial than the first.

The evidence still points one direction. The benefit is biggest in the patients most likely to end up in the hospital, and those are the patients the 48-hour-or-nothing myth talks us out of treating.

What happens when the patient can’t reach a prescriber in time?

Antiviral care runs all or none. Either the patient reaches a prescriber inside the window, or the clock runs out while they wait for an appointment or for Monday to roll around.

A lot of the clinical work doesn’t need a sick patient, though. You can tell a high-risk patient to call on day one, not day four. You can flag the simvastatin or the tacrolimus that would complicate Paxlovid, and note their kidney function. All of that can happen at a routine visit or a refill call, while everyone’s healthy. That’s the missing middle layer, and it’s what we mean by appropriate medical preparation.

At Jase, we build that layer for the times primary care isn’t there, never as a replacement for it. Tamiflu and Paxlovid are both available as JaseCase add-ons. A licensed provider reviews each request and writes the prescription only when it’s appropriate, and either medication is for emergency use only, after first seeking the assistance of a qualified healthcare provider. If you’d rather not field these requests yourself, you can refer patients to us. We’ll keep publishing the frameworks behind where we draw these lines.

The bottom line

The 48-hour window belongs to healthy outpatients with flu. For a high-risk patient, treat as soon as possible, whatever the day count, and don’t wait on a test. COVID runs on its own clock: 5 days for Paxlovid, after you’ve checked the medication list and the kidneys. The benefit is modest for most patients and biggest for the ones most likely to land in the hospital, so start there. Then go enjoy the holidays…… and wash your hands.

To refer a patient, visit jase.com. A licensed provider reviews every request and writes a prescription only when it’s appropriate.

And a final note from Kristen Carpenter, our PA-C who reviewed this article, “during cold/flu season, the timing is so important to start the medication but there are no appointments in primary care schedules since everyone is sick! The chances of a same day or next day appointment are lower! So having high risk patients prepared ahead of time for these busy seasons can be super helpful!”


Sources

  1. FDA. Tamiflu (oseltamivir phosphate) prescribing information. Genentech; revised August 2019. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=ee3c9555-60f2-4f82-a760-11983c86e97b
  2. CDC. Influenza Antiviral Medications: Summary for Clinicians. Updated March 10, 2026. https://www.cdc.gov/flu/hcp/antivirals/summary-clinicians.html
  3. CDC. Influenza Antiviral Drug Resistance. Updated June 26, 2026. https://www.cdc.gov/flu/treatment/antiviralresistance.html
  4. Carrat F, Vergu E, Ferguson NM, et al. Time lines of infection and disease in human influenza: a review of volunteer challenge studies. Am J Epidemiol. 2008;167(7):775-785. doi:10.1093/aje/kwm375
  5. CDC. People at Increased Risk for Flu Complications. Updated September 11, 2024. https://www.cdc.gov/flu/highrisk/index.htm
  6. CDC. Rapid Influenza Diagnostic Tests. Updated June 22, 2026. https://www.cdc.gov/flu/hcp/testing-methods/clinician_guidance_ridt.html
  7. CDC. Underutilization of Flu Antivirals. March 20, 2026. https://www.cdc.gov/flu/whats-new/2025-2026-underutilization-of-flu-antivirals.html
  8. FDA. Paxlovid (nirmatrelvir tablets; ritonavir tablets) prescribing information. Pfizer; revised January 2025. https://www.accessdata.fda.gov/drugsatfda_docs/label/2025/217188s008lbl.pdf
  9. Gottlieb RL, Vaca CE, Paredes R, et al. Early remdesivir to prevent progression to severe Covid-19 in outpatients. N Engl J Med. 2022;386(4):305-315. doi:10.1056/NEJMoa2116846
  10. Zhou F, Yu T, Du R, et al. Clinical course and risk factors for mortality of adult inpatients with COVID-19 in Wuhan, China: a retrospective cohort study. Lancet. 2020;395(10229):1054-1062. doi:10.1016/S0140-6736(20)30566-3
  11. Shumaker AH, Bhimraj A, et al. 2025 Clinical Practice Guideline Update by the Infectious Diseases Society of America on the Treatment and Management of COVID-19: Antiviral Treatment for Mild to Moderate COVID-19 in Adults. Clin Infect Dis. doi:10.1093/cid/ciaf680. Posted October 14, 2025. Nirmatrelvir/ritonavir for high-risk adults: strong recommendation, moderate certainty of evidence. Molnupiravir when no other options exist: conditional recommendation, low certainty of evidence.
  12. FDA. Xofluza (baloxavir marboxil) prescribing information. Genentech; revised May 2025. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=e49e1a61-1b7c-4be5-ac84-af6240b511e7
  13. FDA. Veklury (remdesivir) prescribing information. Gilead; revised July 2026. https://www.accessdata.fda.gov/drugsatfda_docs/label/2026/214787s033lbl.pdf
  14. FDA. Fact Sheet for Healthcare Providers: Emergency Use Authorization for Lagevrio (molnupiravir) capsules. Revised June 2024. https://www.fda.gov/media/155054/download
  15. Hanula R, Bortolussi-Courval É, Mendel A, et al. Evaluation of oseltamivir used to prevent hospitalization in outpatients with influenza: a systematic review and meta-analysis. JAMA Intern Med. 2024;184(1):18-27. doi:10.1001/jamainternmed.2023.0699
  16. Jones JM, Manrique IM, Stone MS, et al. Estimates of SARS-CoV-2 seroprevalence and incidence of primary SARS-CoV-2 infections among blood donors, by COVID-19 vaccination status: United States, April 2021 to September 2022. MMWR Morb Mortal Wkly Rep. 2023;72(22):601-605. doi:10.15585/mmwr.mm7222a3


Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

Do You Need Antibiotics for a Sinus Infection? What the New Guidelines Say

Do You Need Antibiotics for a Sinus Infection? What the New Guidelines Say

By the Jase Medical Team

Do you need antibiotics for a sinus infection? Usually not right away. Even when a sinus infection is caused by bacteria, many people recover without antibiotics.

Updated medical guidelines released in July 2025 reinforce an important message: for otherwise healthy adults with uncomplicated bacterial sinusitis, watching symptoms and allowing time for recovery is often the recommended first step, provided follow-up care is available.

But how do you know when it’s time to call your doctor?

The answer has less to do with the color of your mucus and more to do with how long you’ve been sick and whether your symptoms are getting better or worse.

How Do You Know If a Sinus Infection Needs Antibiotics?

Sinus infections can cause congestion, facial pressure, headaches, thick nasal drainage, and discomfort that makes even a normal day feel exhausting.

But these symptoms alone don’t tell you whether antibiotics are necessary.

Healthcare providers look for two important patterns when evaluating a possible acute bacterial sinus infection.

1. Symptoms last at least 10 days without improvement.

If you’ve experienced nasal congestion, drainage, and facial pressure for 10 days or longer without getting better, a bacterial infection becomes more likely.

2. You start feeling better, then suddenly get worse.

Sometimes a cold seems to be clearing up, only for congestion, facial pain, or nasal drainage to return or worsen.

This pattern, often called double worsening, can indicate a bacterial sinus infection.

Neither pattern automatically means you need antibiotics. Instead, these are signs that it’s time to contact your healthcare provider for an evaluation.

Does Green or Yellow Mucus Mean You Need Antibiotics?

No. The color of your mucus isn’t a reliable way to determine whether you have a bacterial infection.

Yellow or green nasal drainage can occur with viral infections, too.

As your immune system responds to an infection, inflammatory cells and other substances can change the appearance of mucus.

That’s why healthcare professionals look at your overall symptoms and their progression rather than prescribing antibiotics based on mucus color alone.

A week of green mucus doesn’t necessarily mean you need an antibiotic.

What Changed in the 2025 Sinusitis Guidelines?

In July 2025, the American Academy of Otolaryngology–Head and Neck Surgery Foundation (AAO-HNSF) updated its adult sinusitis clinical practice guideline for the first time in a decade.

One of the most important changes involves watchful waiting.

For otherwise healthy adults with uncomplicated acute bacterial sinusitis, watchful waiting is now the recommended initial approach, as long as reliable follow-up is available.

That means your healthcare provider may recommend monitoring symptoms and treating discomfort rather than immediately prescribing antibiotics.

This approach can be appropriate even when symptoms feel particularly unpleasant, provided there are no signs of complications.

Why wait?

Because many uncomplicated bacterial sinus infections improve without antibiotics, and unnecessary antibiotic use carries risks, including diarrhea, allergic reactions, and antibiotic resistance.

Waiting isn’t the same as ignoring an infection. It’s an intentional treatment decision made with your healthcare provider.

What Helps a Sinus Infection While You’re Waiting?

If your healthcare provider recommends watchful waiting, there are several ways to manage symptoms while your body recovers.

Saline nasal rinses: Saline irrigation can help clear mucus and relieve congestion. Always use distilled, sterile, or previously boiled and cooled water for nasal rinsing, not untreated tap water.

Steroid nasal sprays: Over-the-counter nasal corticosteroids, such as fluticasone, may help reduce inflammation and congestion. Ask your pharmacist or healthcare provider whether they’re appropriate for you.

Pain relievers: Acetaminophen or ibuprofen may help with headaches, facial discomfort, and fever when they’re safe for your medical history and other medications.

Rest and hydration: Getting adequate rest and drinking enough fluids can support recovery and make symptoms easier to manage.

You don’t need to eliminate every symptom immediately. Instead, pay attention to whether your overall condition is gradually improving.

When Are Antibiotics Necessary for Sinusitis?

If your symptoms persist, worsen, or don’t improve during an agreed period of watchful waiting, your healthcare provider may recommend antibiotics.

According to the updated guidance, first-line options for most adults include amoxicillin or amoxicillin-clavulanate (Augmentin).

When antibiotics are appropriate, the usual recommended treatment duration for uncomplicated adult bacterial sinusitis is five to seven days, rather than automatically prescribing a longer course.

Your clinician will determine which medication and duration are appropriate based on your health history, allergies, symptoms, and other considerations.

If you’ve already started an antibiotic and aren’t improving after three to five days, contact your healthcare provider for reassessment.

Don’t automatically start another antibiotic, extend your prescription, or switch medications on your own.

A clinician may need to reconsider the diagnosis, check for complications, or determine whether a different treatment is needed.

What If You’re Traveling or Can’t Easily Get Back to the Doctor?

There’s an important detail in the watchful-waiting recommendation: it assumes you can access follow-up care.

That’s relatively straightforward when you’re at home with a nearby clinic.

But what if you’re spending a week at a remote cabin, traveling internationally, or preparing for a storm that could temporarily close local healthcare facilities?

The medical criteria for diagnosing bacterial sinusitis don’t change simply because you’re farther from a doctor’s office.

And limited access to care isn’t, by itself, a reason to start antibiotics earlier.

Instead, it makes planning more important.

Before leaving, consider discussing these questions with your healthcare provider:

  • What symptoms should prompt me to contact you?
  • How long should I monitor symptoms before seeking reassessment?
  • What should I do if I can’t access an in-person appointment?
  • Where can I seek medical attention if my symptoms suddenly worsen?

A clear follow-up plan is especially important when you won’t have easy access to your usual healthcare team.

Sinus Infection Warning Signs: When to Seek Immediate Care

Most sinus infections aren’t medical emergencies. But certain symptoms can signal a serious complication that requires urgent evaluation.

Seek emergency medical care if you experience:

  • Swelling or significant redness around an eye, particularly with fever or pain.
  • Double vision, decreased vision, or difficulty moving an eye.
  • A severe or unusual headache, especially if it’s rapidly worsening.
  • Confusion, altered mental status, or difficulty staying awake.
  • A stiff neck or other symptoms suggesting a serious infection.

These symptoms aren’t reasons to simply begin an antibiotic at home. They require immediate medical assessment.

If you’re experiencing a less severe sinus infection but symptoms are worsening or not following the expected recovery pattern, contact your healthcare provider promptly.

Appropriate Medical Preparation Includes Knowing When to Wait

Antibiotics are valuable medications, but using them appropriately is just as important as having access to medical care.

At Jase Medical, our family team of doctors, physician assistants, and pharmacists believes medical preparedness starts with understanding when treatment is necessary and when it may do more harm than good.

Our guidance reflects the updated sinusitis recommendations, including the five-to-seven-day treatment duration for amoxicillin-clavulanate when a clinician determines it’s appropriate.

We also explored the differences between bacterial and viral infections in our July article on how to tell when an infection may need antibiotics.

The most important lesson is simple:

A sinus infection doesn’t automatically require antibiotics.

Watch for the two patterns: symptoms lasting at least 10 days without improvement, or symptoms that improve and then worsen.

Know which warning signs require urgent medical attention, and make sure you have a plan for follow-up care.

Because appropriate medical preparation isn’t always about starting treatment sooner.

Sometimes it’s knowing when waiting is the right treatment.

Medical disclaimer: This article is intended for educational purposes and does not replace individualized medical advice. Antibiotic treatment decisions should be made by a qualified healthcare professional. Seek immediate medical attention for symptoms suggesting a serious complication, and consult your healthcare provider if symptoms persist or worsen.

Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!