For Clinicians | Trick or Treatment? 5 Halloween Health Facts From a Pharmacist

For Clinicians | Trick or Treatment? 5 Halloween Health Facts From a Pharmacist

By Dr. Jamie Wilkey, PharmD, Director of Clinical Education
Medically reviewed and edited by Kristen Carpenter, PA-C

Halloween is this week, so we’re taking a break from our in-depth appropriate medical preparation articles. I just love Halloween (cutesy Halloween, at least), and as a pharmacist I love tying medications into every part of our lives. This time of year they turn up in some strange places, because unusual candy is out and people are doing things they don’t normally do.

Here are the 5 we will cover today: black licorice, costume contacts, a nightly allergy pill, a mushroom from the yard, and a bat in the bedroom. Not all of them are medications….one is a bat.  Each one will help you keep your patients safe this spooky season.

1-Is black licorice bad for you?

In big enough amounts, yes. Real licorice root contains glycyrrhizin (love that name!), which tricks the kidneys into acting like they’re swimming in aldosterone. They hang onto salt, dump potassium, and blood pressure climbs.¹

The New England Journal of Medicine published the cautionary tale in 2020. A 54-year-old construction worker switched from fruit-flavored soft candy to the licorice kind, and ate a large bag or two a day. Three weeks later he went into cardiac arrest in a fast-food restaurant. His team gave him 420 mmol of potassium in 12 hours (21 of those big 20 mEq tablets, for my pharmacist friends), and he didn’t survive.¹

For most people, a handful at a party is fine. A daily habit isn’t, and patients with high blood pressure or heart or kidney disease can get into trouble on even small amounts.² A diuretic, already flushing out potassium on its own, stacks dangerously on top.¹ (We covered the interactions that push potassium the other way in Drug Interactions in a Disaster.)

Not every bag counts, either. Many US “licorice” products are flavored with anise oil and contain no licorice at all, while licorice root itself shows up in supplements and herbal blends.²  So when a potassium comes back low for no clear reason, ask about candy and supplements.

2-Are costume contacts dangerous?

They can be. A decorative contact lens is a medical device, even if it corrects nothing and just gives you those freaky alien eyes. Selling one without a prescription is illegal, and FDA lists Halloween stores, flea markets, beach shops, and video stores (if you can still find one) as places to never buy them.³

The problem is fit. Decorative lenses aren’t one size fits all, and a lens that doesn’t fit can scratch the cornea, which opens the door for bacteria. FDA warns these infections can cause blindness, sometimes within as little as 24 hours.³

Any red, painful eye after a costume party needs to get seen right away.³ At the pharmacy counter you’ll see a patient asking for redness drops, but the better answer is a same-day exam. (Our pink eye article covers why any lens wearer with a red eye skips the wait.)

3-Can medications cause nightmares?

They sure can, and two common ones put it right on the label. Montelukast, the nightly allergy and asthma pill, got an FDA boxed warning in 2020 for mental health side effects, and “bad or vivid dreams” made the list. FDA’s counseling is that a patient who notices these changes is to stop the medication and call a health care professional right away. FDA also asks prescribers to save montelukast for allergy patients who don’t respond to, or can’t tolerate, other allergy medicines.⁴

Beta-blockers are the other one: propranolol’s label lists vivid dreams, and metoprolol’s lists nightmares.⁵,⁶ It’s not clear why these cause bad dreams, though. One theory is melatonin. The brain makes it at night on a beta-receptor signal, and in one small study, a single dose of propranolol’s active form cut nighttime melatonin to about a fifth of normal.⁷

Beta-blockers get the opposite advice from montelukast, though. Both labels warn that stopping suddenly can worsen angina, so the patient is to keep taking it and call the prescriber for next steps.⁵,⁶

So when a patient mentions new nightmares….check the medication list before blaming the horror movie marathon.

4-Why are death cap mushrooms so sneaky?

Because they play dead, like any good horror movie villain. The mushrooms that only upset the stomach make people sick within an hour or two. Death caps wait, then hit with vomiting and diarrhea, often 6 or more hours after the meal.⁸,⁹ With fluids, the patient can even start to feel better while their liver tests still look normal, which is how some get sent home with a stomach bug diagnosis.⁸

Meanwhile, the toxin has shut down the liver cells’ ability to make new proteins. Liver injury shows up on labs within a day or so, and liver failure can follow over the next several days.⁸,⁹

Death caps grow along the West Coast, including in city parks, and peak season runs October through April (happy Halloween). Northern California just had the largest outbreak in its history: 39 suspected poisonings and 4 deaths. Many of those patients had picked a mushroom that looked like a safe one they’d foraged in another country.⁹

So when vomiting and diarrhea start hours after a meal, ask about wild mushrooms. If the answer is yes, call Poison Control at 1-800-222-1222 right away, even if the patient feels better. (A pharmacist might answer. We really are everywhere.)¹⁰

5-Does a bat in the house mean rabies shots?

Sometimes. Bats caused 35 of the 42 rabies cases caught in the US since 2000.¹¹ A bat bite can be so small nobody notices it, so people don’t seek shots before symptoms start, and by then it’s too late.¹¹

That’s why any direct contact with a bat gets a rabies risk assessment. If the bat can’t be tested, waking up with one in the room calls for shots when the sleeper could have missed a bite: a deep sleeper, a young child, someone who’d been drinking, or someone on a sedating medication (pharmacists, that one’s ours).¹¹,¹²

One of the two Americans who died of bat rabies in 2024 had found a bat in her Minnesota home. She saw clinicians several times after her symptoms started, and the bat never made it into her chart.¹¹ So ask! (Our bite and scratch article has the full rabies refresher.)

The bottom line

Halloween hazards like to hide in plain sight. Here are the 5 to keep in your clinical back pocket this week:

  • Low potassium for no clear reason? Ask about licorice.
  • Red, painful eye after a costume party? Same-day eye exam.
  • New nightmares? Check the medication list.
  • Vomiting hours after a meal? Ask about wild mushrooms, and call Poison Control at 1-800-222-1222.
  • A bat in the house? Rabies risk assessment, especially for anyone who was asleep.

We’re here for the times primary care isn’t there, and in no way a replacement for it. This list is a good example: every one of these ends with a call to a clinician, an eye doctor, or Poison Control. Happy Halloween from all of us at Jase! 🎃


Sources

  1. Edelman ER, Butala NM, Avery LL, Lundquist AL, Dighe AS. Case 30-2020: a 54-year-old man with sudden cardiac arrest. N Engl J Med. 2020;383(13):1263-1275. https://pmc.ncbi.nlm.nih.gov/articles/PMC8568064/
  2. National Center for Complementary and Integrative Health. Licorice Root. Updated April 2025. https://www.nccih.nih.gov/health/licorice-root
  3. U.S. Food and Drug Administration. Colored and Decorative Contact Lenses: A Prescription Is a Must. Content current as of October 24, 2022. https://www.fda.gov/consumers/consumer-updates/colored-and-decorative-contact-lenses-prescription-must
  4. U.S. Food and Drug Administration. FDA requires Boxed Warning about serious mental health side effects for asthma and allergy drug montelukast (Singulair); advises restricting use for allergic rhinitis. Drug Safety Communication. March 4, 2020. https://www.fda.gov/drugs/drug-safety-communications/fda-requires-boxed-warning-about-serious-mental-health-side-effects-asthma-and-allergy-drug
  5. Inderal LA (propranolol hydrochloride) extended-release capsules. Prescribing information. ANI Pharmaceuticals; 2026. DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=35d28979-36b1-4630-b85e-a44e0a443734
  6. Metoprolol tartrate tablets. Prescribing information. Mylan Pharmaceuticals; 2024. DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=809c6386-0039-42ff-a03e-e42733e229b8
  7. Stoschitzky K, Sakotnik A, Lercher P, et al. Influence of beta-blockers on melatonin release. Eur J Clin Pharmacol. 1999;55(2):111-115. https://pubmed.ncbi.nlm.nih.gov/10335905/
  8. Santi L, Maggioli C, Mastroroberto M, Tufoni M, Napoli L, Caraceni P. Acute liver failure caused by Amanita phalloides poisoning. Int J Hepatol. 2012;2012:487480. https://pmc.ncbi.nlm.nih.gov/articles/PMC3395149/
  9. Brandecker KJ, Hayman C, LeSaint KT, et al. Amanita species mushroom poisonings, Northern California, November 2025-March 2026. MMWR Morb Mortal Wkly Rep. 2026;75(20):258-263. https://www.cdc.gov/mmwr/volumes/75/wr/mm7520a2.htm
  10. America’s Poison Centers. Get Poison Help. https://poisoncenters.org/page-1075452
  11. Ireland M, Fritz CL, Holzbauer S, et al. Human rabies deaths, Minnesota and California, 2024. MMWR Morb Mortal Wkly Rep. 2026;75(2):28-31. https://www.cdc.gov/mmwr/volumes/75/wr/mm7502a4.htm
  12. Manning SE, Rupprecht CE, Fishbein D, et al. Human rabies prevention, United States, 2008: recommendations of the Advisory Committee on Immunization Practices. MMWR Recomm Rep. 2008;57(RR-3):1-28. https://www.cdc.gov/mmwr/preview/mmwrhtml/rr57e507a1.htm
  13.  


Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

Five Halloween Hazards That Look Harmless

Five Halloween Hazards That Look Harmless

Five Halloween Hazards That Look Harmless By the Jase Medical Team The scariest things this Halloween might not look scary at all. A bag of black licorice. A pair of costume contacts. A medication you take every night. A mushroom growing in the yard. A bat that...

read more

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

After a Tick Bite: Why the Lyme Disease Rash Doesn’t Always Look Like a Bull’s-Eye

After a Tick Bite: Why the Lyme Disease Rash Doesn’t Always Look Like a Bull’s-Eye

By the Jase Medical Team

You found a tick attached to your skin. You removed it. Now what?

Most people know to watch for signs of Lyme disease after a tick bite. But there’s a problem with the picture we’ve all been taught to recognize.

The Lyme disease rash doesn’t always look like a bull’s-eye. In fact, many don’t.

And depending on which tick bit you, Lyme disease might not even be the main concern.

Different ticks carry different health risks. A blacklegged tick can transmit Lyme disease, while a lone star tick can trigger an unusual allergy that makes certain foods dangerous to eat.

That’s why the most important questions after a tick bite aren’t just whether you removed the tick or whether the bite looks infected. They’re which tick bit you, and what should you watch for over the next month?

First, Which Tick Bit You?

Not every tick carries the same diseases, and not every tick bite leads to an infection.

Two ticks worth knowing about are the blacklegged tick and the lone star tick.

Blacklegged tick (deer tick): Blacklegged ticks can transmit the bacteria that cause Lyme disease. They’re especially common in the Northeast, mid-Atlantic, and upper Midwest, although their geographic range extends beyond those regions.

Lone star tick: Lone star ticks are common across much of the South and East. The adult female is recognizable by a single white spot on her back. These ticks are not recognized as carriers of Lyme disease, but their bites can trigger alpha-gal syndrome, an allergy associated with reactions to certain mammalian foods.

If you find an attached tick, remove it promptly using fine-tipped tweezers, grasping close to the skin and pulling steadily upward. Clean the bite area afterward. If possible, take a clear photo of the tick to help with identification, but don’t delay removal.

If you’re unsure what kind of tick it was, that’s okay. Your location, exposure history, and any symptoms that develop can still help a healthcare professional assess your risk.

The Lyme Disease Rash Usually Doesn’t Look Like the Picture

The classic Lyme disease rash is called erythema migrans.

You’ve probably seen it illustrated as a red bull’s-eye, with a darker center surrounded by a lighter ring and another red circle.

That pattern can happen, but it isn’t required for Lyme disease.

In many cases, the rash looks more like a flat, expanding patch of redness. It may be evenly red or pink, or it may have a darker center without the distinctive target-shaped rings. On darker skin, the discoloration may be less visibly red and can appear violet or brown.

The important feature isn’t the pattern. It’s that the rash gradually expands.

An erythema migrans rash usually appears between 3 and 30 days after an infected tick bite. It often grows over several days and can become quite large. It may feel warm, but it’s not typically intensely painful or itchy.

A small area of redness immediately after removing a tick is common and doesn’t automatically mean Lyme disease. That local irritation usually fades rather than continuing to expand.

If you notice a spreading rash in the days or weeks after a possible tick exposure, don’t dismiss it because it doesn’t look like a bull’s-eye.

Get it evaluated.

Why an Early Lyme Disease Test Can Be Negative

Here’s another reason people sometimes miss early Lyme disease: they assume a blood test will immediately provide the answer.

Lyme disease blood tests look for antibodies your immune system produces in response to infection. But those antibodies take time to develop.

During the first few weeks of infection, testing can be negative even when someone has Lyme disease.

That’s why medical guidelines recommend diagnosing a typical erythema migrans rash based on its appearance and the patient’s exposure history, rather than waiting for a positive blood test.

If a rash is unusual or the diagnosis is uncertain, a healthcare professional may recommend testing and, in some situations, repeat testing later.

For patients, the lesson is simple:

Don’t wait for a perfect bull’s-eye rash or assume an early negative test rules out Lyme disease.

Tell your healthcare provider when you found the tick, where you may have been exposed, and how the rash or other symptoms have changed.

What If You Never Develop a Rash?

Not everyone with Lyme disease notices a rash.

Other early symptoms can include fever, chills, fatigue, headache, muscle aches, and joint pain. Those symptoms can resemble a common viral illness, making recent tick exposure an important detail to share with your healthcare provider.

Untreated Lyme disease can sometimes progress to more serious complications involving the joints, nervous system, or heart.

That doesn’t mean every headache after hiking is Lyme disease. Most tick bites do not result in Lyme disease.

But if you develop unexplained symptoms in the weeks after a tick bite, especially in an area where Lyme disease occurs, don’t leave the exposure out of your medical history.

A Lone Star Tick Can Cause an Allergy Instead

Now for the less familiar risk.

A lone star tick bite can trigger alpha-gal syndrome, an allergy that can cause reactions after eating certain mammalian products.

That includes foods such as beef, pork, and lamb. Some people also react to dairy products or other products containing mammalian ingredients.

Unlike a typical food allergy, which often causes symptoms shortly after eating, alpha-gal reactions can be delayed.

Symptoms frequently appear two to six hours after a meal.

Imagine eating a hamburger for dinner, feeling completely fine afterward, and then waking up hours later with hives, stomach pain, nausea, or an allergic reaction.

You might blame something else entirely because the meal happened so long ago. That’s part of what makes alpha-gal syndrome difficult to recognize.

Symptoms can range from gastrointestinal discomfort and itching to severe allergic reactions, including anaphylaxis.

Alpha-gal syndrome is not an infection, so antibiotics don’t treat or prevent it. Diagnosis involves reviewing symptoms and exposure history, often alongside a blood test for alpha-gal-specific IgE antibodies.

If you begin experiencing unexplained allergic reactions after eating mammalian foods, especially following tick exposure, talk with your healthcare provider about whether alpha-gal syndrome should be considered.

If you experience difficulty breathing, throat swelling, fainting, or other signs of anaphylaxis, seek emergency care immediately and use prescribed epinephrine if available.

Should You Take Antibiotics After Every Tick Bite?

No.

Antibiotics are not automatically recommended after every tick bite.

For certain high-risk blacklegged tick bites, a healthcare provider may recommend a preventive dose of doxycycline. But that decision depends on specific criteria, including the tick species, geographic location, estimated attachment time, and how recently the tick was removed.

Those criteria matter because unnecessary antibiotics carry risks, and preventive treatment is not appropriate for every exposure.

We covered the full criteria in our July article on doxycycline after a tick bite.

If you’ve recently removed a tick and are concerned about Lyme disease, contact a healthcare professional promptly. The window for considering preventive treatment is limited.

And remember, antibiotics used to prevent Lyme disease do not prevent alpha-gal syndrome.

What Should You Watch for Over the Next Month?

After removing a tick, pay attention to changes in your health over the following days and weeks.

An expanding rash, fever, unusual fatigue, headache, muscle aches, or joint symptoms can be reasons to contact your healthcare provider. Some tick-borne infections can cause illness without producing a recognizable rash.

For possible lone star tick exposure, also be aware of unusual or delayed allergic reactions after eating mammalian foods. Alpha-gal symptoms can begin weeks or longer after the bite, so the connection may not be immediately obvious.

Seek urgent medical evaluation for severe symptoms, including difficulty breathing, fainting, chest pain, a new facial droop, or a severe headache accompanied by neck stiffness or fever.

You don’t need to spend the next month worrying about every sensation. But knowing what to watch for helps you recognize when something deserves medical attention.

Medical Preparedness Starts With Knowing What to Look For

Tick bites are a good example of why appropriate medical preparation involves more than keeping medications on hand.

The most useful preparation may be recognizing that the rash you’ve been taught to expect isn’t always the rash you’ll see. Or knowing that a tick common in your region can trigger a food allergy rather than Lyme disease. Or understanding that an early negative blood test doesn’t necessarily close the case.

At Jase Medical, our family team of medical doctors, PAs, and pharmacists focuses on evidence-based medical preparation that complements the care you receive from your regular healthcare providers.

The goal isn’t to diagnose yourself or take antibiotics just in case. It’s to recognize the signs that deserve attention and know when to seek care.

So the next time you find a tick, remember:

The tick helps determine the risk. And the symptoms that follow may not look anything like you expected.


The Jase Medical Team is a family team of medical doctors, PAs, and pharmacists focused on appropriate medical preparation: clinically grounded readiness that complements, rather than replaces, the healthcare professionals you already trust.

This article was prepared by the Jase Medical content team for informational purposes only and does not constitute medical advice. Prescription requirements, emergency dispensing rules, insurance coverage, and controlled-substance regulations vary by medication, jurisdiction, and individual circumstances. Consult a licensed healthcare provider or pharmacist regarding your specific medications.

Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

Five Halloween Hazards That Look Harmless

Five Halloween Hazards That Look Harmless

Five Halloween Hazards That Look Harmless By the Jase Medical Team The scariest things this Halloween might not look scary at all. A bag of black licorice. A pair of costume contacts. A medication you take every night. A mushroom growing in the yard. A bat that...

read more

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

For Clinicians | After the Tick Bite: The Tick Decides the Risk

For Clinicians | After the Tick Bite: The Tick Decides the Risk

By Dr. Jamie Wilkey, PharmD, Director of Clinical Education
Medically reviewed and edited by Aaron Asay, PA-C, DMSc, FIBODM, FAWM

Ticks have been on my radar my whole life. I grew up in Wyoming, where there are very few trees around (and those that exist are either aspens or pine trees), so needless to say,  a treehouse in my yard wasn’t an option. Instead, I had a fort out on the hill in my backyard in the sagebrush: a hole in the ground with planks over the top. Even then playing in the sagebrush all day I kept an eye out for ticks. I’ve never had a tick bite (knock on wood), which feels kind of amazing, because our family cabin has ticks everywhere and I still hike in the Utah mountains most mornings.

This article is for the clinicians helping outdoor people like me who just can’t stay away from the outdoors. We’ll cover basic tick identification, what a Lyme rash really looks like, when to test and treat, and the tick bite that ends in a red-meat allergy instead of an infection.

Which tick was it?

Whether it comes up in the office or at the pharmacy counter, start with two questions: what did the tick look like, and where was the patient when it bit?

  • Blacklegged tick (deer tick): carries Lyme. Common in the Northeast, mid-Atlantic, and upper Midwest, with a western cousin along the Pacific coast¹. The nymph is about the size of a poppy seed, so most patients never notice the bite².
  • Lone star tick: the adult female has one white spot on her back. Common in the South, East, and Midwest.³ It doesn’t carry Lyme, but it’s the main cause of alpha-gal syndrome¹,⁴.
  • Rocky Mountain wood tick: the common tick in the Rocky Mountain states³. It doesn’t carry Lyme¹(So my sagebrush fort was safe, at least from Lyme, whew!).However, it can transmit other serious infections, including Rocky Mountain spotted fever, Colorado tick fever, and tularemia.

[IMAGES: row of three, PHIL 28383, PHIL 8676, PHIL 10865]
Blacklegged tick, adult female (left) and nymph (right). Photo: CDC/Lauren Bishop.
Lone star tick, adult female. Photo: CDC/James Gathany.
Rocky Mountain wood tick. Photo: CDC/James Gathany.
Source for all: CDC Public Health Image Library.

If the patient can’t name the tick, their geographic exposure can help narrow the possibilities, although tick species and their ranges may overlap.

What does a Lyme rash actually look like?

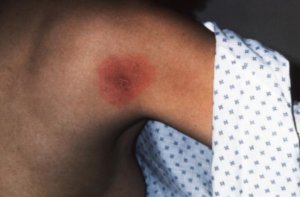
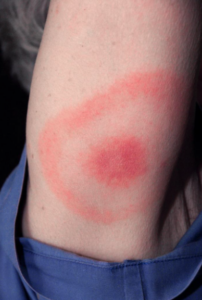
Most of us learned the Lyme rash as a bull’s-eye presentation. In the US, most erythema migrans (EM) rashes are evenly red, or reddest in the center, with no rings at all²,⁵. A typical EM is diagnosed on sight ⁶.

The rash is the bacteria spreading outward through the skin from the bite, which is why it grows². What to look for:

  • A red patch at the bite site that keeps expanding over several days, sometimes to 12 inches or more
  • Shows up 3 to 30 days after the bite, about a week on average
  • Warm to the touch, but rarely itchy or painful⁷.

A small red bump right after the bite that looks like a mosquito bite and fades in a day or two is a bite reaction, not Lyme⁷.

Should you test a typical EM?

No. For a typical EM rash, skip the blood test and treat ⁶.

The rash shows up before the immune system has made enough antibodies to measure. If you were to test 10 patients with a fresh rash, 6 to 8 of them would come back negative⁸. Antibody testing has limited sensitivity during early localized Lyme disease, so a negative result does not exclude infection. When a patient has a typical erythema migrans rash and credible exposure, treatment should not wait for laboratory confirmation.

Two more tests to skip after a tick bite ⁶:

  • Testing the tick itself for Lyme bacteria. A positive or negative tick doesn’t predict whether the patient gets infected. (Identifying the species is still useful.)
  • Testing a patient who has no symptoms.

Save the blood test for a rash that doesn’t look typical. If that first draw is negative, IDSA suggests a second sample taken later to catch the antibodies as they rise⁶.

[IMAGES: side by side, PHIL 9875 and PHIL 14474]
The Lyme rash everyone pictures (left) and a more typical one (right). Photos: CDC/James Gathany (left), CDC (right). Source: CDC Public Health Image Library.

How long do you treat a Lyme rash?

Treat a typical EM with 10 days of doxycycline, or 14 days of amoxicillin or cefuroxime ⁶. Longer courses aren’t recommended. Azithromycin for 7 days is the backup for patients who can’t take doxycycline or a beta-lactam ⁶. Doxycycline isn’t off-limits for young kids anymore, either. IDSA notes a growing consensus that courses of up to 14 days are safe in young children (plus, newer research casts doubt on that old tooth-staining worry ⁶).

Doxycycline counseling is the same as always: take it with a full glass of water and wear sunscreen⁹,¹⁰. And finish the course as written, even after the rash fades.

What about a single dose of doxycycline right after the bite? It’s an option for a high-risk bite within 72 hours of removing the tick, and the criteria are strict. We walked through who qualifies in our July article on doxycycline uses.

What is alpha-gal syndrome?

Alpha-gal is a sugar found in most mammals, but not in people, birds, or fish. A tick bite, most often from a lone star tick, can sensitize the immune system to it⁴,¹¹. Lone star ticks aren’t the only suspect, though: Maine has reported a case after a blacklegged tick bite¹². It’s an allergy, not an infection, so antibiotics don’t treat or prevent it. The doxycycline from the last section does nothing here.

Consider alpha-gal when a patient has hives, stomach symptoms, or anaphylaxis 2 to 6 hours after eating red meat or dairy¹¹,¹³. The delay is a big part of why it gets missed. So is unfamiliarity: in a CDC survey of 1,500 clinicians, about 4 in 10 had never heard of it ¹³. 

The workup is an alpha-gal IgE blood test, read alongside the history, because a positive result alone doesn’t make the diagnosis¹⁴. From there, it’s avoidance, an allergist, and an epinephrine plan for anyone with systemic reactions¹⁵,¹⁶.

Pharmacists, something good for you to keep in mind as well: some medications made with gelatin can trigger a reaction¹.Not every patient reacts to dairy, gelatin, or mammalian-derived medications. Avoidance recommendations should be individualized according to reaction history and allergy evaluation.

Where the gap is after a tick bite


Most tick bites don’t happen conveniently next to a clinic during office hours. They happen on a trail, at a cabin, or on a hunting trip. And right now, care after a bite is all or none: the patient reaches a clinician while it still matters, or they’re left with a rash, an internet search, and a bull’s-eye picture that doesn’t match what’s on their leg.

That missing middle is the work we do. We call it appropriate medical preparation: teaching patients what to watch for before they head out, with a clinician-built plan for when care isn’t reachable. It’s in no way a replacement for primary care. It’s for the times when primary care isn’t there.

Tick bites are part of that work. Doxycycline is in every JaseCase, and its card covers two tick situations: the single preventive dose, only when every criterion on the card is met, and the 10-day course for an EM rash. Both are for emergency use only, after the patient has first tried to reach a qualified healthcare provider.

If you’d rather not prescribe in this space, you can refer patients to us. A licensed provider reviews every request and writes every prescription. And we’ll keep publishing how we draw these lines, the same way we did here.

The bottom line
Ask which tick made the bite and where it happened. Diagnose a typical Lyme rash on sight, and don’t wait for a bull’s-eye or a positive test to treat it. Skip testing the tick, and skip testing the patient with no symptoms. Think alpha-gal when a lone star bite is followed by delayed reactions to red meat, and remember antibiotics won’t touch it.

People who love the outdoors aren’t going to stay inside, and I’m one of them. To refer a patient, visit Jase.com, where a licensed provider reviews every request.


Sources

  1. CDC. How Lyme disease spreads. Updated September 24, 2024. https://www.cdc.gov/lyme/causes/index.html
  2. Nadelman RB. Erythema migrans. Infect Dis Clin North Am. 2015;29(2):211-239. https://doi.org/10.1016/j.idc.2015.02.001
  3. CDC. Where ticks live. Updated July 30, 2025. https://www.cdc.gov/ticks/about/where-ticks-live.html
  4. CDC. About alpha-gal syndrome. Updated January 5, 2026. https://www.cdc.gov/alpha-gal-syndrome/about/index.html
  5. Smith RP, Schoen RT, Rahn DW, et al. Clinical characteristics and treatment outcome of early Lyme disease in patients with microbiologically confirmed erythema migrans. Ann Intern Med. 2002;136(6):421-428. https://doi.org/10.7326/0003-4819-136-6-200203190-00005
  6. Lantos PM, Rumbaugh J, Bockenstedt LK, et al. Clinical practice guidelines by the Infectious Diseases Society of America (IDSA), American Academy of Neurology (AAN), and American College of Rheumatology (ACR): 2020 guidelines for the prevention, diagnosis, and treatment of Lyme disease. Clin Infect Dis. 2021;72(1):e1-e48. https://doi.org/10.1093/cid/ciaa1215
  7. CDC. Signs and symptoms of untreated Lyme disease. Updated May 15, 2024. https://www.cdc.gov/lyme/signs-symptoms/index.html
  8. Horn EJ, Menefee B, Schotthoefer AM, et al. Evaluation of standard and modified two-tiered testing algorithms using well-characterized early Lyme disease samples. J Clin Microbiol. 2026;64(5):e0118725. https://doi.org/10.1128/jcm.01187-25
  9. MedlinePlus. Doxycycline. Revised May 15, 2026. https://medlineplus.gov/druginfo/meds/a682063.html
  10. Medsafe (New Zealand Medicines and Medical Devices Safety Authority). Oesophagitis with doxycycline and others. Prescriber Update. 2003;24(2):30. https://www.medsafe.govt.nz/profs/puarticles/doxoesoph.htm
  11. CDC. Alpha-gal syndrome for healthcare providers. April 12, 2022. https://stacks.cdc.gov/view/cdc/131343
  12. Saunders EF, Sohail H, Myles DJ, et al. Alpha-gal syndrome after Ixodes scapularis tick bite and statewide surveillance, Maine, USA, 2014–2023. Emerg Infect Dis. 2025;31(4). https://doi.org/10.3201/eid3104.241265
  13. Carpenter A, Drexler NA, McCormick DW, et al. Health care provider knowledge regarding alpha-gal syndrome: United States, March–May 2022. MMWR Morb Mortal Wkly Rep. 2023;72(30):809-814. https://doi.org/10.15585/mmwr.mm7230a1
  14. CDC. Clinical diagnosis and testing (alpha-gal syndrome). Updated January 5, 2026. https://www.cdc.gov/alpha-gal-syndrome/hcp/diagnosis-testing/index.html
  15. Nationwide Children’s Hospital. Alpha-gal syndrome (AGS): clinical FAQ for health care professionals. October 2025. https://pediatricsnationwide.org/wp-content/uploads/2026/04/W2043400-RUSH_Alpha-Gal-Syndrome_Clinical-FAQ-for-Providers_FINAL.pdf
  16. CDC. Managing alpha-gal syndrome. Updated January 5, 2026. https://www.cdc.gov/alpha-gal-syndrome/managing/index.html


Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

Five Halloween Hazards That Look Harmless

Five Halloween Hazards That Look Harmless

Five Halloween Hazards That Look Harmless By the Jase Medical Team The scariest things this Halloween might not look scary at all. A bag of black licorice. A pair of costume contacts. A medication you take every night. A mushroom growing in the yard. A bat that...

read more

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

Diabetes Sick-Day Rules in a Disaster

Diabetes Sick-Day Rules in a Disaster

By the Jase Medical Team

Diabetes sick-day rules are usually written for an ordinary week.

You get the flu. Your stomach is upset. You check your blood sugar more often, keep drinking fluids, follow your medication plan, and call your healthcare provider if certain symptoms or numbers appear.

But what happens when the phone doesn’t work?

A hurricane, prolonged power outage, wildfire, flood, or boil-water advisory can make diabetes harder to manage at exactly the same time healthcare becomes harder to reach. Vomiting and diarrhea can cause dehydration. Heat can affect hydration and blood sugar. Missed meals can complicate medication management. Other illnesses, infections, or medications prescribed for an acute condition can affect glucose, too.

That’s why diabetes sick-day rules should be written down before the disaster, not explained for the first time during it.

First: Don’t Stop Insulin on Your Own

If you use insulin, one of the most important sick-day principles is that becoming sick does not mean you should simply stop taking it.

Illness can actually increase blood sugar even when you’re eating less than usual. Your body releases stress hormones while fighting an infection or other illness, and those hormones can push glucose higher.

Exactly how much insulin you need may depend on your diabetes type, glucose readings, ketones, food intake, hydration, and the individualized instructions you’ve received from your healthcare team.

So the rule isn’t to improvise.

Do not stop or change your insulin without following your prescribed sick-day plan or receiving guidance from a qualified healthcare professional.

We’ve covered the importance of maintaining access to insulin and other time-sensitive medications separately in our guide to which medications cannot wait during an emergency.

The Harder Question: What About Your Other Medications?

This is where diabetes sick-day planning gets more complicated.

Many adults with type 2 diabetes aren’t managing one medication. You may take several medications for diabetes along with medications for blood pressure, heart disease, kidney protection, or other chronic conditions.

During an illness involving dehydration, vomiting, diarrhea, or significantly reduced food and fluid intake, a healthcare provider may want certain medications temporarily held. The concern can include dehydration, kidney function, low blood sugar, or other complications depending on the medication and your health history.

In the UK, clinicians sometimes teach this concept using the acronym SADMANS, which refers to several medication classes that may require special consideration during a dehydrating illness.

The acronym is less important than the problem it reveals: your sick-day medication plan may involve prescriptions from more than one clinician, and nobody should be trying to sort that out for the first time while sick during a power outage.

Should You Stop Metformin or Jardiance When You’re Sick?

These are exactly the kinds of questions to answer with your prescriber or pharmacist before you need the answer.

People searching for “metformin sick-day rules” or “Jardiance sick-day rules” will find general recommendations online. But whether a medication should be held, when it should be restarted, and what monitoring is appropriate depends on the medication, the illness, your hydration, kidney function, glucose control, and your individual medical history.

Don’t create your own stop-and-restart schedule from a generic internet list.

Instead, ask your healthcare provider or pharmacist to review all of your regular medications and identify which, if any, require different instructions when you’re dehydrated, vomiting, having diarrhea, or unable to eat and drink normally.

Then write those instructions down.

Any decision to hold, restart, or change a prescription medication should follow instructions from your licensed healthcare provider. If you cannot reach your regular provider during an emergency, try to reach another qualified healthcare professional whenever possible before changing your medication regimen.

Your Sick-Day Plan Should Live With Your Medication List

A medication list tells someone what you take.

A sick-day plan tells you what your prescriber wants you to do when normal conditions change.

Ideally, the two should stay together.

Your written plan should make it easy to find your usual diabetes medications and doses, how often your healthcare team wants you checking glucose when you’re sick, whether and when they want you checking ketones, what they want you to do if you cannot eat or drink normally, and which symptoms or readings mean you need medical care.

If any of your medications have special sick-day instructions, those should be written beside the medication rather than left to memory.

This is especially useful for people whose medication list spans multiple conditions or prescribers.

Ketones Aren’t Only a Type 1 Diabetes Conversation

Ketones are most strongly associated with type 1 diabetes, but some people with type 2 diabetes may also need ketone monitoring during illness, particularly depending on their medications and individual risk factors.

Your healthcare provider should tell you whether you need ketone testing as part of your sick-day plan, when they want you to test, and what results require action.

This matters because diabetic ketoacidosis, or DKA, is a medical emergency. It can develop when the body does not have enough effective insulin and begins producing high levels of ketones.

Symptoms can include nausea, vomiting, abdominal pain, excessive thirst, frequent urination, unusual fatigue, confusion, and rapid or deep breathing.

If your diabetes plan includes ketone testing, make sure you understand it before you’re sick.

Know the Numbers That Mean It’s Time to Go

A written plan should also make clear where home management ends.

The American Diabetes Association advises contacting a healthcare provider or seeking emergency care for concerning sick-day situations, including persistent vomiting or diarrhea, moderate to large ketones, and very high glucose readings that aren’t responding as expected.

For example, ADA sick-day guidance identifies vomiting or diarrhea lasting more than four hours and glucose above 300 mg/dL on two readings despite correction as reasons to contact your provider or go to the emergency room. Moderate to large ketones are another warning sign requiring prompt attention.

Your own healthcare team may give you different or additional thresholds based on your diabetes and medical history.

The important part during a disaster is that you already know those thresholds.

If you cannot keep fluids down, are becoming severely dehydrated, have significant ketones, are confused or unusually drowsy, have difficulty breathing, or have another severe or rapidly worsening symptom, don’t wait for normal clinic operations to resume.

A disaster can change how difficult it is to reach care. It doesn’t make a diabetes emergency less urgent.

Illness Isn’t the Only Thing That Can Push Blood Sugar Around

Disasters tend to stack problems on top of one another.

Maybe you’re eating differently because the refrigerator lost power. Maybe extreme heat is affecting your hydration. Maybe a stomach illness is making it difficult to keep fluids down. Maybe wildfire smoke triggered a COPD or asthma exacerbation, and you’ve been prescribed a corticosteroid as part of your respiratory treatment.

Corticosteroids can raise blood glucose, sometimes significantly.

That doesn’t mean you should avoid a medication your healthcare provider has determined you need. It means your diabetes plan should account for the possibility that another illness or treatment could change your glucose management.

If you have diabetes alongside asthma, COPD, or another chronic condition that may require acute treatment, ask your healthcare team how those plans interact before an emergency.

The Best Time to Write Your Diabetes Sick-Day Rules Is When You’re Well

You don’t need to create a complicated disaster protocol.

Start with one question at your next appointment or pharmacy consultation:

“If I’m sick, dehydrated, and can’t reach you, what do you want me to do with each of these medications?”

Bring your complete medication list.

Ask how often you should check glucose when sick. Ask whether you should check ketones and under what circumstances. Ask which medications, if any, have special sick-day instructions. Ask exactly what conditions need to be met before a medication that was held can be restarted. And ask which numbers or symptoms mean you should stop trying to manage the situation at home and seek care.

Then put those instructions on paper and keep them with your medication list.

At Jase Medical, our family team of medical doctors, PAs, and pharmacists focuses on appropriate medical preparation held to high clinical standards. JaseCase provides physician-prescribed contingency medications for specific medical situations after review by a licensed provider. These medications are intended for emergency use after first trying to reach a qualified healthcare provider and should be used only according to the instructions provided.

JaseCase doesn’t replace your diabetes medications or your individualized diabetes care plan. But the same principle behind appropriate medical preparation applies here: make the decision with the right healthcare professional before the moment when reaching them becomes difficult.

Because diabetes sick-day rules shouldn’t depend on the phone working.

The plan should already be in your hands.

The Jase Medical Team is a family team of medical doctors, PAs, and pharmacists focused on appropriate medical preparation that complements, rather than replaces, the healthcare professionals you already trust.

This article is for informational purposes only and does not constitute individualized medical advice. Do not stop, restart, or change prescription medications based solely on this article. Work with your healthcare provider or pharmacist to develop an individualized diabetes sick-day plan, and seek prompt medical care for severe or rapidly worsening symptoms.


The Jase Medical Team is a family team of medical doctors, PAs, and pharmacists focused on appropriate medical preparation: clinically grounded readiness that complements, rather than replaces, the healthcare professionals you already trust.

This article was prepared by the Jase Medical content team for informational purposes only and does not constitute medical advice. Prescription requirements, emergency dispensing rules, insurance coverage, and controlled-substance regulations vary by medication, jurisdiction, and individual circumstances. Consult a licensed healthcare provider or pharmacist regarding your specific medications.

Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

Five Halloween Hazards That Look Harmless

Five Halloween Hazards That Look Harmless

Five Halloween Hazards That Look Harmless By the Jase Medical Team The scariest things this Halloween might not look scary at all. A bag of black licorice. A pair of costume contacts. A medication you take every night. A mushroom growing in the yard. A bat that...

read more

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

For Clinicians | Diabetes Sick-Day Rules in a Disaster

For Clinicians | Diabetes Sick-Day Rules in a Disaster

By Dr. Jamie Wilkey, PharmD, Director of Clinical Education
Medically reviewed and edited by Kristen Carpenter, PA-C

Diabetes is already hard to manage. Sick days just make everything worse. And a sick day in a disaster, when healthcare isn’t readily available, compounds the hardship. Put the three together and it’s 1 + 1 + 1. For someone’s health, that doesn’t equal 3.
It equals 20. 

And the disaster itself counts as its own 1, even before anyone gets sick. In a Puerto Rico cohort of adults who didn’t have diabetes, new cases showed up at about twice the pre-storm rate in the years spanning Hurricanes Irma and Maria¹.

Disaster guidance for diabetes focuses mostly on a supply list (have plenty of insulin on hand and stored properly!). Sick days barely come up as a management topic. That’s a big gap when about 40 million Americans have diabetes, 2.1 million of them type 1². Their care really does change in a disaster, whether that’s a hurricane or a week when they can’t reach their clinic or pharmacy. We have to address that.

Today we’ll cover:

  • what a diabetes sick day is
  • which medications pause (+ why insulin never pauses)
  • how ketones work, and why a normal meter reading can fool you
  • what to look for in the OTC aisle
  • how to write the plan before storm season

What is a diabetes sick day?

I’m including this here to start because even as a pharmacist I have to admit (abashedly) that I didn’t know much about this topic. 99% of my diabetic counseling focused on medications in general and blood sugar testing.

A diabetes sick day is any illness that changes how the body handles glucose, fluids, or medications: a stomach bug, a fever, a UTI, or a really rough flu. The hormones the body releases to fight illness push blood sugar up ³…. even in a patient who has barely eaten all day. Vomiting, diarrhea, and fever drain fluid, and the kidneys feel it first. That’s where the medication problems start.  Several of the drugs these patients take every day either depend on the kidneys or make dehydration worse. And when insulin runs short, the body breaks down fat for fuel and starts making ketones.

Sick-day rules exist to catch all of that early: check glucose more often, keep fluids going, check ketones, and call when the numbers cross a line. The ADA’s patient guide ends with “call your doctor or go to the ER” ⁴. Yep, every version ends there, which doesn’t really work.

A disaster amplifies everything. Bad water brings on vomiting and diarrhea. Heat causes dehydration. Meals get skipped. Smoke or mold sets off someone’s asthma, and the steroid burst that settles their breathing raises glucose on its own (we covered that in our asthma and COPD flare article). The clinic is often closed, flooded, or not picking up, so care isn’t available.

Which medications pause on a diabetes sick day?

Canadian clinicians teach the pause list as SADMANS, a Diabetes Canada mnemonic ⁵, and UK sick-day cards carry close versions of it⁶,⁷. Each class gets much riskier when a patient is dehydrated or not eating, and most of the list comes back to the kidney’s filter, which needs pressure to work. Picture a garden hose with me for the kidneys. Blood volume is the water from the spigot. When the water runs low, the kidney keeps the spray going two ways: it holds the inflow open, and it puts a thumb over the end of the hose so pressure builds inside, where the filtering happens. That’ll help you picture how the SADMANS medications affect the patient’s kidney.

  • S: sulfonylureas like glipizide and glimepiride keep pushing insulin out when the patient isn’t eating. Some linger as kidney function drops.
  • A: ACE inhibitors like lisinopril shut off angiotensin II, and angiotensin II is the kidney’s thumb. Take it away from a dehydrated patient and filtering pressure drops.
  • D: diuretics like HCTZ and furosemide turn the spigot down further on a patient who’s already losing fluid.
  • M: metformin doesn’t hurt the kidneys, but they’re its only way out. When they slow down, metformin builds up, and so does the risk of lactic acidosis.
  • A: ARBs like losartan take the thumb off the same way ACE inhibitors do.
  • N: NSAIDs like ibuprofen and naproxen kink the hose near the spigot by blocking the prostaglandins that hold the inflow open. (Spigot down, hose kinked, thumb off: that’s the triple whammy from our drug interactions article)
  • S: SGLT2 inhibitors like Jardiance and Farxiga pull glucose and water out through the urine, deepening dehydration, and raise DKA risk, sometimes with a normal glucose (more on that next).

GLP-1 drugs like semaglutide aren’t in the mnemonic, but the ADA Standards note they may need holding when GI symptoms are significant ⁸.

SADMANS isn’t a US guideline, and the evidence behind sick-day lists is mostly expert opinion⁵. The ADA Standards say to consider holding metformin and SGLT2 inhibitors when the patient can’t keep up with eating and drinking or kidney injury is a concern ⁸, and Jardiance’s label says to withhold it, if possible, in situations that could predispose to ketoacidosis ⁹. The ADA’s patient guide says to keep taking diabetes medications as prescribed unless the doctor advises otherwise ⁴. That “unless” is our job. Which pills pause for which patient, and when they restart (UK practice is usually after 24 to 48 hours of normal eating and drinking⁶, are prescriber decisions that belong in the written plan. The plan is for emergency use only, after the patient has tried to reach their prescriber or pharmacist first.

And just to be clear here, insulin never pauses. Basal insulin keeps going even when the patient isn’t eating⁸. Mealtime doses follow the food¹⁰, and the total dose can change while they’re sick ³, which is exactly the kind of adjustment that belongs in the plan. Stopping basal insulin because they can’t eat is the classic road to DKA, and in type 1 that road is short. (For keeping insulin cool when the power’s out, see our insulin storage article.)

Who owns the sick-day conversation?

The ADA already tells patients to make a sick-day action plan with their doctor before they ever get sick ⁴. I don’t think many of us are having that conversation, in the office or at the pharmacy. In more than 10 years as a pharmacist, I’ve had five or fewer of them. I’m not proud of that at all, but patients rarely, if ever, proactively brought up the topic. At my busy 24-hour pharmacy, counseling got to the single most important thing a patient needs to start the medication (and sick days didn’t usually make the cut). 

Part of the problem is that nobody owns the med list. The pills that pause on a sick day often come from two prescribers: metformin and an SGLT2 inhibitor from primary care, lisinopril and a diuretic from cardiology. Each prescriber may only see their half. The pharmacy profile shows every prescription filled there, from every prescriber, and our interaction software checks across all of it.

That makes this a pharmacy counter conversation as much as an office one. For a patient on metformin, Jardiance, lisinopril, and HCTZ, here’s how it would sound coming from me:

“When you’re sick, it can really change your diabetes and your medications and you have to be extra careful. Here’s what to know in a nutshell. If you’re throwing up or can’t keep fluids down, some of your pills may need to pause until you’ve been eating and drinking normally for a day or two. For you, that’s probably all four, but your doctor makes that call, so let’s ask them to put it in writing now. I’ll send a fax requesting that right now.  Because you’re on Jardiance, check your ketones when you’re sick, even if your sugar looks normal. Call your doctor or the pharmacy first. If you can’t reach anyone, these symptoms mean you need to get to emergency care ASAP: throwing up or diarrhea for more than 4 hours, moderate or large ketones, or a sugar over 300 twice.“

How ketones work, and why a normal meter reading can fool you

Ketones are what the liver makes from fat when cells can’t get enough insulin to use glucose. A little after a long fast is normal. When insulin runs short in a dehydrated patient, ketones build faster than the body clears them. Then the blood turns acidic, and that’s DKA (diabetic ketoacidosis).

On an SGLT2 inhibitor, the kidneys keep dumping glucose into the urine, so the meter can read 150 while ketones climb. Jardiance’s label warns that glucose at presentation can sit below what we’d expect for DKA, for example under 250 ⁹, and the ADA defines euglycemic DKA as DKA with a glucose under 200 ¹¹. The glucose number stops being a warning light, so an SGLT2 user’s plan needs to be checking ketones when sick, whatever the meter reads.

The tool matters too. There are two main ketones in the blood, and urine strips only see one of them. In DKA, most of the ketones are the other kind¹², so a strip can read low while the real level is high. That’s why the ADA wants at-risk SGLT2 users to have a blood ketone meter¹³. From what I’ve seen working in the pharmacy a lot of urine strips and keto meters are being bought up by the keto, weight-loss, and muscle-building crowds, so they can be kind of hard to find sometimes. (Funny twist, since the ADA also tells us to steer SGLT2 users away from keto eating¹³.) Put the strips, or a blood meter, on the written plan and make sure that patients actually have some on hand so they’re handy before they are needed.

The Wilderness Medical Society tells insulin users heading into the backcountry to carry a ketone kit, and it treats DKA as an emergency that calls for evacuation¹⁴. A hurricane week at home isn’t the backcountry, but it shares the part the guideline is written around: limited access to care. Moderate or large ketones means to get to emergency care, not wait for the phone.

What to look for in the OTC aisle

The ADA’s guide tells patients to work out which OTC medications are safe with their doctor before they get sick ⁴, but it doesn’t say which ones. The pharmacist is the natural person to fill in that blank. Every pick comes back to the two questions from the pause list: what it does to the kidneys, and what it does to glucose.

  • Ibuprofen and naproxen are the N in SADMANS, and they hide in combination products (one 12-hour sinus product pairs naproxen with pseudoephedrine). The plan should name the swap for pain and fever, usually acetaminophen if the liver allows.
  • Pseudoephedrine’s Drug Facts tell anyone with diabetes to ask a doctor before using it¹⁵. 
  • The ADA’s guide says to alternate water and electrolyte drinks ⁴, and sugar isn’t automatically the enemy. A patient who can’t eat still needs about 50 grams of carbohydrate every 4 hours ³, and regular juice or soda may be how they get it.
  • Glucose tabs or gel are on the ADA’s sick-day supply list ⁴, and they matter most for anyone on a sulfonylurea or insulin who can’t eat.

Like everything else on the plan, these are emergency-use answers, for when the patient has tried to reach their pharmacist or prescriber first and can’t get through.

How to write the plan before storm season

The ADA’s guide already lists what belongs in a sick-day plan ⁴. The disaster version fills in every line with this patient’s medication names and strengths written on paper, kept with their medication list:

  • Which of their pills pause, by name, and when each one restarts
  • For insulin users, the basal dose that keeps going and how to adjust mealtime and correction doses
  • How often to check glucose and ketones, and with what (urine strips or a blood meter)
  • The OTC picks for fever and pain, congestion, fluids, and lows
  • The numbers that mean get to emergency care when no one answers:
    • vomiting or diarrhea for more than 4 hours
    • moderate or large ketones, or the blood ketone number you set
    • glucose over 300 on two readings despite corrections
    • fever over 101°F lasting more than 24 hours
    • signs of dehydration, like dizziness or dark urine
  • Who to call first, their number, and when they are reachable: the prescriber or the pharmacy

The plan is for emergency use only, after the patient has tried those calls and can’t get through.

The bottom line

Sick-day care for diabetes is all or nothing right now. Either the clinic or the pharmacy picks up, or the patient is alone with four bottles and a meter just guessing and winging it with what they look up online. A written plan is the missing middle layer: the decision made ahead of time by the person who should make it, ready for the day nobody answers. That’s appropriate medical preparation at its simplest. It’s in no way a replacement for primary care; we’re here for the times when primary care isn’t there. Our team of physicians, PAs, and pharmacists is building the version of this plan for the week the clinic’s phone is dead, and we’ll publish the framework as we go.

Before the next storm, write the plan for every patient on an SGLT2 inhibitor, metformin, or insulin. Pharmacists, start it at the counter.

A sick day in a disaster will never be easy. A plan on paper keeps 1 + 1 + 1 a lot closer to 3.


Sources

  1. Martínez-Lozano M, Noboa C, Alvarado-González G, Joshipura KJ. Hurricanes Irma and Maria and diabetes incidence in Puerto Rico. BMC Public Health. 2023;23:1019. https://pmc.ncbi.nlm.nih.gov/articles/PMC10227808/
  2. Centers for Disease Control and Prevention. National Diabetes Statistics Report. Updated September 16, 2026. https://www.cdc.gov/diabetes/php/data-research/index.html
  3. Centers for Disease Control and Prevention. Managing sick days. Updated May 15, 2024. https://www.cdc.gov/diabetes/living-with/managing-sick-days.html
  4. American Diabetes Association. Sick Day Guide for People with Diabetes (patient version). September 2025. Based on the Standards of Care in Diabetes-2025. https://professional.diabetes.org/sites/dpro/files/2025-09/SickDayGuide_Final.pdf
  5. Watson KE, Dhaliwal K, McMurtry E, et al. Sick day medication guidance for people with diabetes, kidney disease, or cardiovascular disease: a systematic scoping review. Kidney Med. 2022;4(9):100491. https://pmc.ncbi.nlm.nih.gov/articles/PMC9420951/
  6. Healthcare Improvement Scotland. Medicines sick day guidance card, version 4. 2026. https://www.healthcareimprovementscotland.scot/wp-content/uploads/2026/05/Medicines-sick-day-guidance-card-A6-June-2026.pdf
  7. Northern Ireland Formulary. Sick day rules. Accessed October 5, 2026. https://niformulary.hscni.net/formulary/6-0-endocrine/6-1-drugs-used-in-diabetes/6-1-2-antidiabetic-drugs/sick-day-rules/
  8. American Diabetes Association Professional Practice Committee for Diabetes. 6. Glycemic goals, hypoglycemia, and hyperglycemic crises: Standards of Care in Diabetes-2026. Diabetes Care. 2026;49(Suppl 1):S132-S149. https://pmc.ncbi.nlm.nih.gov/articles/PMC12690178/
  9. Jardiance (empagliflozin) prescribing information. Boehringer Ingelheim Pharmaceuticals; revised January 2026. DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=faf3dd6a-9cd0-39c2-0d2e-232cb3f67565
  10. RxFiles. Protecting the kidneys. September 2025. https://www.rxfiles.ca/RxFiles/uploads/documents/SADMANS-Rx.pdf
  11. American Diabetes Association Professional Practice Committee for Diabetes. 16. Diabetes care in the hospital: Standards of Care in Diabetes-2026. Diabetes Care. 2026;49(Suppl 1):S339-S355. doi:10.2337/dc26-S016
  12. Umpierrez GE, et al. Hyperglycemic crises in adults with diabetes: a consensus report. Diabetes Care. 2024;47(8):1257-1275. https://pmc.ncbi.nlm.nih.gov/articles/PMC11272983/
  13. American Diabetes Association Professional Practice Committee for Diabetes. 9. Pharmacologic approaches to glycemic treatment: Standards of Care in Diabetes-2026. Diabetes Care. 2026;49(Suppl 1):S183-S215. https://pmc.ncbi.nlm.nih.gov/articles/PMC12690185/
  14. VanBaak KD, et al. Wilderness Medical Society clinical practice guidelines for diabetes management. Wilderness Environ Med. 2019;30(4 Suppl):S121-S140. Written for wilderness athletes; recommendations cited: carry a ketone testing kit (grade 1B), and evacuate for DKA or HHS (grade 1A). https://pmc.ncbi.nlm.nih.gov/articles/PMC7510348/
  15. Sudafed Sinus Congestion 12 Hour (pseudoephedrine HCl) Drug Facts label. Kenvue; revised November 8, 2024. DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=d600b5d5-7d95-4ad6-a95b-6d73502743d7


Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

Five Halloween Hazards That Look Harmless

Five Halloween Hazards That Look Harmless

Five Halloween Hazards That Look Harmless By the Jase Medical Team The scariest things this Halloween might not look scary at all. A bag of black licorice. A pair of costume contacts. A medication you take every night. A mushroom growing in the yard. A bat that...

read more

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!