How to Rehydrate Someone Properly When There Is No IV

How to Rehydrate Someone Properly When There Is No IV

By the Jase Medical Team

When someone is losing fluid from vomiting or diarrhea, rehydration isn’t simply a matter of getting them to drink something.

The type of fluid matters. The amount matters. And especially when someone is vomiting, the rate matters.

That’s the science behind oral rehydration therapy, a remarkably effective approach to dehydration that has been used around the world for decades. The World Health Organization’s oral rehydration solution (ORS) contains glucose and sodium in carefully balanced concentrations, 75 mmol/L of each, with a total osmolarity of 245 mOsm/L. The glucose helps the intestine absorb sodium, and sodium helps bring water with it.

In other words, oral rehydration isn’t just “drink more water.”

It’s using the gut’s own transport system to move water back into the body.

An Electrolyte Drink Isn’t Necessarily an Oral Rehydration Solution

Walk down the hydration aisle and you’ll see sports drinks, electrolyte powders, flavored waters, hydration packets, and products promising rapid hydration.

They aren’t all the same thing.

A true oral rehydration solution is formulated with a specific balance of glucose and electrolytes designed for replacing fluid lost through illnesses such as diarrhea and vomiting. WHO’s reduced-osmolarity ORS contains 75 mmol/L of sodium and 75 mmol/L of glucose.

That is different from a beverage designed primarily for exercise, flavor, or everyday hydration.

So if someone is dehydrated from a stomach illness, prepackaged oral rehydration solution should be your first choice when it’s available. Look for a product specifically labeled for oral rehydration rather than assuming anything marketed as an “electrolyte drink” serves the same purpose.

And don’t assume you can turn a sports drink into ORS simply by diluting it. Adding water changes all of its concentrations—including the sodium you’re trying to replace.

When Someone Is Vomiting, How They Drink Matters

One of the most common problems with oral rehydration happens when a very thirsty person tries to drink a large amount at once.

Their stomach may send it right back up.

Instead, oral rehydration can be given in small, frequent amounts and gradually increased as tolerated. CDC guidance for children with vomiting describes starting with about 5 mL, roughly one teaspoon, every five minutes and increasing gradually. A spoon or oral syringe can make those small amounts easier to control.

That may feel painfully slow when a child is thirsty and you know they need fluid. But getting a small amount to stay down repeatedly can be more useful than having them drink a large glass and vomit it back up.

Vomiting also doesn’t automatically mean oral rehydration has failed. CDC guidance notes that most children with vomiting accompanying acute gastroenteritis can still be successfully rehydrated orally when ORS is given in limited, frequent amounts.

How Much Oral Rehydration Solution Does Someone Need?

This is where age, weight, degree of dehydration, ongoing fluid losses, and medical history matter.

For children, clinicians use weight-based approaches to determine how much fluid is needed for rehydration and how much additional ORS should be given to replace continuing losses from diarrhea or vomiting. WHO guidance also provides age-based amounts of ORS after loose stools when preventing dehydration: for example, 50–100 mL after each loose stool for children under 2 and 100–200 mL for children ages 2–10.

That doesn’t mean every sick child should be managed at home by calculating a formula.

If you’re unsure how much fluid a child needs, or you’re concerned they’re already significantly dehydrated, contact their pediatrician or another qualified medical professional.

The useful household principle is simpler: oral rehydration isn’t one big drink. It’s a process of replacing what has already been lost while continuing to replace what the person is still losing.

What If You Don’t Have Commercial ORS?

Prepackaged oral rehydration solution is preferable because the concentrations have already been measured for you. WHO describes ORS as a pharmaceutical product and recommends manufacturing it according to quality standards.

If proper ORS truly isn’t available, a homemade sugar-and-salt solution may be used as an emergency fallback following established public-health instructions.

Do not improvise the proportions.

Too much salt can be dangerous, particularly for infants and young children. Don’t use heaping spoonfuls, estimate quantities by eye, or decide that making the solution “stronger” will make it work better.

For that reason, we recommend keeping commercially prepared ORS packets or ready-to-use oral rehydration solution available rather than relying on memory for an emergency recipe.

If you do need to make a homemade solution, use a recipe from a recognized public-health authority and follow the measurements exactly using level measures and the specified amount of clean water.

Pedialyte vs. Gatorade: Does It Matter?

For ordinary exercise or replacing fluid after sweating, a sports drink may be perfectly reasonable for many people.

But rehydrating someone who is losing significant fluid through vomiting or diarrhea is a different job.

Products formulated as oral rehydration solutions are designed around the balance of glucose and electrolytes needed to promote absorption and replace losses. Sports drinks are formulated for a different purpose and may contain considerably different amounts of sodium and sugar.

So when the problem is dehydration from gastroenteritis, don’t choose solely by which bottle says “electrolytes” on the front.

Look for an actual oral rehydration solution.

When Oral Rehydration Stops Being a Home Problem

Oral rehydration is powerful, but it isn’t appropriate for every situation.

Severe dehydration or shock requires urgent medical treatment and may require IV fluids. CDC guidance specifically identifies shock or near-shock as situations requiring initial IV treatment.

Seek urgent medical care for concerning signs such as severe lethargy or difficulty waking, confusion, fainting, very little or no urine, inability to keep even small amounts of fluid down, blood in the stool or vomit, severe abdominal pain, or other signs that the person is becoming seriously ill.

Infants deserve an especially low threshold for contacting a pediatrician because dehydration can progress quickly.

And if your instinct is telling you that someone is getting worse rather than better, don’t let the fact that you’re giving ORS create false reassurance. Oral rehydration is a treatment tool, not a substitute for medical evaluation when someone is seriously ill.

Why Knowing Oral Rehydration Still Matters

It’s easy to think of IV fluids as the “real” treatment and oral fluids as the backup.

The healthcare system has repeatedly been reminded why that isn’t always true.

After Hurricane Helene damaged Baxter’s North Cove manufacturing facility in 2024, the disruption affected a facility that had been producing approximately 60% of the IV solutions used each day in the United States. Hospitals and health systems had to conserve IV fluids and reconsider when patients could safely receive hydration through other routes.

But households never had an IV bag hanging in the kitchen in the first place.

What you can have is an appropriate oral rehydration solution and an understanding of how to use it: the right fluid, the right amount, and the right pace.

At Jase Medical, we’re a family team of physicians, PAs, and pharmacists focused on appropriate medical preparation. That doesn’t mean trying to turn your home into an emergency department. It means understanding which simple, evidence-based tools can help when ordinary access to care is delayed and knowing exactly where home care needs to stop.

For vomiting and diarrhea, that starts with something surprisingly basic:

Don’t just replace water. Rehydrate properly.


The Jase Medical Team is a family team of medical doctors, PAs, and pharmacists focused on appropriate medical preparation: clinically grounded readiness that complements, rather than replaces, the healthcare professionals you already trust.

This article was prepared by the Jase Medical content team for informational purposes only and does not constitute medical advice. Prescription requirements, emergency dispensing rules, insurance coverage, and controlled-substance regulations vary by medication, jurisdiction, and individual circumstances. Consult a licensed healthcare provider or pharmacist regarding your specific medications.

Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

Why You Can’t Dose a Child From an Adult Tablet

Why You Can’t Dose a Child From an Adult Tablet

Why You Can't Dose a Child From an Adult Tablet You cannot reliably turn an adult medication into a child's dose just by cutting the tablet smaller. That can be frustrating to hear at 9 p.m. when the children's ibuprofen bottle is empty, the pharmacy is closed, and...

read more
What is Plague?

What is Plague?

What Is Plague? By the Jase Medical Team Plague is back in the headlines, and people are suddenly Googling a disease they may not have thought about since history class. A 28-year-old laboratory worker at an anti-plague research institute in Siberia recently died...


read more

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

For Clinicians | Oral Rehydration When IV Fluids Aren’t Available

For Clinicians | Oral Rehydration When IV Fluids Aren’t Available

By Dr. Jamie Wilkey, PharmD, Director of Clinical Education
Medically reviewed and edited by Kristen Carpenter, PA-C

Hi again, it’s Jamie, your pharmacist who loves writing about appropriate medical preparation.

In the past we’ve focused on specific medications and natural disasters, but haven’t properly covered hydration. Today we are fixing that! Getting fluids into someone when an IV isn’t available, or when it’s just not convenient. Sometimes that’s a real access problem. More often it’s 9pm, urgent care closed at 8, and you’re standing in your own kitchen holding a liquid that a sick kid has decided is their mortal enemy.

I’ve dealt with this from behind the counter and I’ve dealt with it at home as a mom of 4 boys. Today we’re covering what oral rehydration is, what it does, and how it works; especially without an IV available. I’ll speak generally about kids specifically in this article, but it applies to teens and adults (you kids at heart) as well. 

Why plain water doesn’t rehydrate

Quick refresher, because this is one of those things we all learned and then filed away. I know I needed this refresher to write this article.

A patient who is vomiting and having diarrhea isn’t just down a volume of water. They’re down sodium, potassium and chloride, and they’re losing more with every episode. Plain water replaces the volume, but none of the salts. If the patient is only drinking water and still has ongoing losses then the plain water dilutes the sodium that’s left. Juice, soda and broth have either too much sugar, not enough sodium, or sodium with nothing to carry it across those cell membranes. 

Before I wrote this article I thought off the top of my head that an oral rehydration solution is a salt delivery system and the sugar is just in there for taste. But I was wrong! The sugar is the mechanism to get the salts out of the gut and into the blood stream.

One of the doors into the gut wall only opens when glucose and sodium show up together. They cross the wall coupled, and water follows the sodium across by osmosis. That’s why an oral rehydration solution is built at roughly equal parts sodium and glucose. ¹ The ratio is the design. Enough glucose to work that door, and no more than that, because sugar past that point doesn’t move any more sodium and it raises the osmolarity of what’s sitting in the gut, which pulls water in the wrong direction.

Plenty of drinks contain both. Very few contain them in the amounts that make the transport work. Both ingredients being present doesn’t make something an oral rehydration solution.

What to use, and what to make when there’s nothing in the house

A packaged oral rehydration solution is the first choice every time. It’s already mixed to the ratio, and it carries two things the kitchen version can’t: potassium, to replace what’s going out in the stool, and citrate, which buffers the acidosis that comes with it. Nobody has to measure anything at 2am.

Here’s the recipe for a rehydration solution made at home: one litre of clean water, 3 g of table salt, and 18 g of sugar, which is about four level teaspoons. ¹

WHO writes that 3 g as “one level teaspoonful.” Don’t pass that along to an American patient. A level US teaspoon of table salt holds closer to 6 g, the full 2,300 mg of sodium you see on a nutrition label, and it doubles the salt in the litre. Counsel half a level teaspoon, or 3 g on a kitchen scale. Level spoons for the sugar too, not heaping ones, and not a soup spoon out of the drawer.


* And one note for those of you doing the math in your head wondering how in the heck this salt and sugar recipe is a 1:1 ratio. Eighteen grams of sugar against 3 g of salt doesn’t look like equal parts of anything. The molecule counts are the same though. A sugar molecule weighs about six times what a unit of table salt weighs, so 6 to 1 by weight comes out to 1 to 1 by molecule. What the transporter responds to is how many molecules of each are in the glass, not how much they weigh.

WHO prints that recipe and then says it isn’t generally recommended, for three specific reasons: the recipe gets forgotten, the ingredients aren’t always there, and people end up giving too little of it. ¹ That caution is written for public health programs deciding what to teach at scale. We at Jase are usually talking to someone whose options have already narrowed to what’s in the kitchen, and for them a recipe they can remember beats a packet they can’t reach. Know it. Use it when there’s nothing better.

So the counseling on this is to for sure use a proper rehydration packet if your patients have one or can reasonably get access to one. If they’re mixing it themselves, have them use an actual measuring spoon and level it off, because the difference between a level teaspoon and a heaping one is a big difference, especially for kids.

The homemade version carries no potassium and no citrate. It’s the bridge to getting a rehydration packet, not a complete replacement for one.

Most electrolyte drinks are not oral rehydration solutions

I’m guilty of this one too. If the label said electrolytes, I assumed it would do the job for a kid who needed fluids.

So, here’s the yardstick. An oral rehydration solution built at the WHO ratio, poured into a 16 oz glass, is about 800 mg of sodium and about 6 g of sugar. ¹ WHO set that 75 mmol/L by lowering it from an older 90, because less sodium worked better in ordinary childhood diarrhea than the cholera-era formula did. The studies behind that change ran down to 50 mmol/L, so the American products sitting under 75 are sitting inside the evidence, not outside it. Anywhere in that range is an oral rehydration solution. Far below it is a beverage.

  • Pedialyte Classic: about 520 mg sodium, about 7 g sugar ²
  • DripDrop: about 660 mg sodium, about 14 g sugar³
  • Gatorade Thirst Quencher: about 216 mg sodium, about 27 g sugar⁴
  • LMNT: 1,000 mg sodium per stick, zero sugar⁵

Pedialyte lands in range. It’s the only one on the list that was built for this, and it shows on both numbers.

DripDrop gets the sodium into the neighborhood and then doubles the sugar. The idea is right; the sugar is twice what the transport needs, and the extra is the part that raises osmolarity. Probably not a big deal clinically, but not ideal.

Gatorade misses on both ends, a quarter of the sodium and more than four times the sugar. That isn’t a mistake on their end. It’s built to replace what comes out in sweat during a workout, not what comes out in stool during a rotavirus.

LMNT is the big example of a drink that isn’t going to help here, and it’s the poster child I’d use to teach this whole thing. All salt, no sugar at all. Go back to that door in the gut, the one that only opens when salt and sugar show up together. Without the sugar, the salt doesn’t have a ride across. It sits in the gut, pulls water in with it, and makes a miserable kid more miserable.

How much they need to drink, and how fast

So now we know what should be in the cup. That’s one part of it…but not the end. We still have to know how much they need to drink and how often, because the right liquid in the wrong amount doesn’t rehydrate anybody.

The working numbers are 50 mL per kilogram over four hours for mild dehydration, 100 mL per kilogram for moderate, plus another 10 mL per kilogram after each diarrheal stool, capped at about a cup per stool.⁶ WHO’s plan for a small child uses a flat 75 mL per kilogram. ¹

In kids, for mild dehydration:

A 2-year-old at 30 lb needs about 680 mL over four hours. Call it three cups.
A 10-year-old at 80 lb needs about 1.8 litres. Seven or eight cups.

Double both of those if they’re moderately dehydrated. One problem with doubling it. You’re now asking a 2-year-old to drink a cup and a half an hour. WHO says a kid that size tops out around a cup.¹

For an adult the weight formula stops being useful, and the instruction becomes replacing what’s going out: about a cup after every loose stool, and drinking to thirst rather than on a schedule.

Especially for kids, this goes by spoon or cup, never a bottle.¹ WHO’s rate for a child under 2 is a teaspoonful every one to two minutes. Older kids and adults can take frequent sips straight from the cup.¹ If they’re vomiting, start slower, around a teaspoon every five minutes, and build up as they keep it down.⁶ A big gulp on an irritated stomach comes right back. And if they do vomit, wait 5 to 10 minutes and start again more slowly, a spoonful every two or three minutes.¹

The spacing is the whole thing. A teaspoon every five minutes, held there for four hours, comes to about one cup. Every one to two minutes gets you somewhere between two and five. The 2-year-old needs three. So five minutes is where you start when they’re throwing up, not where you stay.

When they can’t keep anything down

And this is where oral rehydration falls apart out there in the real world. Not on the science. Because it’s a lot of liquid, it generally tastes awful, and a sick kid fights every ounce of it. The kid who throws up the first three teaspoons makes the family quickly lose faith in this rehydration approach because it can be so hard and stressful to help kids who are miserable keep the dang liquid down. I know, because I’ve been there many late nights with my own boys and I was ready to pull my hair out because it feels like there’s no way to get liquid down a gullet that doesn’t want to swallow. 

Ondansetron is the medication for this with solid evidence. In 2006 a trial was run with 215 children between 6 months and 10 years with gastroenteritis and mild to moderate dehydration. They got a single oral dose or placebo, then started a standardized rehydration protocol. Vomiting during rehydration: 14% with ondansetron, 35% with placebo. Needing IV fluids: 14% versus 31%.⁷

Then in July 2025 a much larger trial tested children 6 months to 18 years who went home from six pediatric emergency departments with six doses of ondansetron or placebo for caregivers to give over the next 48 hours as vomiting continued. Moderate to severe gastroenteritis over the following week: 5.1% with ondansetron, 12.5% with placebo.⁸ Side effects were comparable between groups, with a small increase in diarrheal stools among the children who took three doses or more.

So, if throwing up or severe nausea is a problem, give an antiemetic first, then the fluid. Ondansetron doesn’t treat the illness itself. It buys the window where oral rehydration can actually succeed.

The treatment layer that doesn’t exist

A family either reaches a clinician or they’re alone with whatever is in the cabinet. What’s usually in their house is a sports drink. There’s nothing sanctioned in between.

Hospitals hit a similar wall twice in seven years. Hurricane Maria took out Baxter’s Puerto Rico plants in 2017. Helene took out North Cove in 2024, the plant making roughly 60% of the country’s IV fluids.⁹ Surveyed afterward, most affected hospitals had converted IV medications to oral, and well over half had written themselves an oral hydration protocol.¹⁰ They built the middle layer under pressure, because the alternative had disappeared.

That right there is the layer we work on at Jase, and appropriate medical preparation is what we call it: the clinical decision made ahead of the illness instead of during it, so the person standing in the kitchen at 9pm already has the right rehydration packet and a plan for how often to give it. Whether an antiemetic belongs in a particular house is a prescribing decision. A licensed provider reviews every Jase request and writes the prescription, and anything dispensed that way is for emergency use only, after first trying to reach a qualified provider.

None of this replaces primary care. It complements it, for the hours when primary care isn’t reachable. If this is a conversation you’d rather hand off in your own clinic, you can refer patients to us, and we’ll keep publishing the criteria we use so you can judge them yourselves.

Where oral rehydration stops

Now I want to make it really, really clear: oral rehydration is only for mild to moderate dehydration. It is not the answer for severe dehydration, shock, or a child who isn’t mentally there. That really does require an IV, and urgently.

If you’re having trouble judging how severe it is, here’s the general checklist. Lethargic or unconscious. Sunken eyes. Skin that tents and stays tented. Not able to drink at all.¹ Two or more of those are past what a cup is going to fix, and they need to get to care with an IV urgently.

The end!

Thanks for joining us on dehydration. Dehydration shows up from so many different directions: throwing up and diarrhea, sure, but also a fever that runs for days, a sore throat or mouth sores that make a kid refuse to drink, a hot afternoon with too much play and not enough water, and plain lack of access to clean water. The cause changes. The ratio, the volume and the rate don’t.


Sources

  1. World Health Organization. The Treatment of Diarrhoea: A Manual for Physicians and Other Senior Health Workers. 4th rev. Geneva: WHO; 2005. Source for the reduced-osmolarity ORS composition (sodium 75 mmol/L, glucose 75 mmol/L, total osmolarity 245 mOsm/L), the home-made salt and sugar solution and WHO’s reasons for not generally recommending it, Treatment Plan B at 75 mL/kg over four hours, administration by spoon or cup rather than a bottle with a 5 to 10 minute pause after vomiting, and the Table 1 signs used to classify severe dehydration.. https://www.who.int/publications/i/item/9241593180
  2. Abbott Nutrition. Pedialyte Classic. Nutrition panel read 21 September 2026: 390 mg sodium and 5 g total sugars per 12 fl oz (360 mL), which works out to about 520 mg sodium and about 7 g sugar per 16 fl oz. https://www.abbottnutrition.com/our-products/pedialyte-classic
  3. DripDrop. Product FAQ. Read 21 September 2026: 660 mg sodium per 16 fl oz prepared, with about 14 g sugar per 16 fl oz. https://dripdrop.com/pages/faq
  4. Gatorade. Gatorade Thirst Quencher, 20 fl oz. Product FAQ read 21 September 2026: about 270 mg sodium per 20 fl oz, which works out to about 216 mg per 16 fl oz. Total sugars of 34 g per 20 fl oz, about 27 g per 16 fl oz, from the nutrition panel recorded 18 September 2026. https://www.gatorade.com/sports-drinks/gatorade-thirst-quencher/orange
  5. LMNT. Ingredients and formulation. Read 21 September 2026: 1,000 mg sodium, 200 mg potassium and 60 mg magnesium per stick, and no sugar. https://drinklmnt.com/pages/ingredients
  6. Merck Manual Professional Edition. Oral Rehydration Therapy. Confirmed 21 September 2026: 50 mL/kg over four hours for mild dehydration and 100 mL/kg for moderate, an additional 10 mL/kg (up to 240 mL) for each diarrheal stool, starting at 5 mL every five minutes and increasing as tolerated. https://www.merckmanuals.com/professional/pediatrics/dehydration-and-fluid-therapy-in-children/oral-rehydration-therapy
  7. Freedman SB, Adler M, Seshadri R, Powell EC. Oral ondansetron for gastroenteritis in a pediatric emergency department. N Engl J Med. 2006;354(16):1698-1705. Single oral dose of orally disintegrating ondansetron versus placebo in 215 children aged 6 months through 10 years, given before a standardized oral rehydration protocol. Vomiting during rehydration 14% versus 35% (RR 0.40, 95% CI 0.26 to 0.61); intravenous rehydration 14% versus 31% (RR 0.46, 95% CI 0.26 to 0.79). Hospital admission rates did not differ between the groups. https://pubmed.ncbi.nlm.nih.gov/16625009/
  8. Freedman SB, Williamson-Urquhart S, Plint AC, et al., for the Pediatric Emergency Research Canada Innovative Clinical Trials Study Group. Multidose ondansetron after emergency visits in children with gastroenteritis. N Engl J Med. 2025;393(3):255-266. Randomized, double-blind trial in six Canadian pediatric emergency departments; 1,030 children aged 6 months to under 18 years received six take-home doses of ondansetron or placebo for use over 48 hours. Moderate-to-severe gastroenteritis over the following 7 days occurred in 5.1% versus 12.5% (adjusted odds ratio 0.50, 95% CI 0.40 to 0.60). https://pubmed.ncbi.nlm.nih.gov/40673584/
  9. American Hospital Association. Supply chain updates following temporary closure of Baxter’s plant in North Carolina due to Hurricane Helene. 2024. Source for the North Cove facility supplying roughly 60% of US IV solutions. https://www.aha.org/special-bulletin/supply-chain-updates-following-temporary-closure-baxters-plant-north-carolina-due-hurricane-helene
  10. Gorgens S, Alshadad A, Malek A, et al. The impact on healthcare facilities of the 2024 IV fluids shortage after Hurricane Helene: a mixed methods study. PLoS One. 2026;21(4):e0344524. Survey of 17 respondents drawn from a 200-member national critical care task force, an 8.5% response rate: 88.2% of hospitals affected by the shortage, 58.8% created an oral hydration protocol, 81.3% converted IV medications to oral. https://journals.plos.org/plosone/article?id=10.1371/journal.pone.0344524


Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

Why You Can’t Dose a Child From an Adult Tablet

Why You Can’t Dose a Child From an Adult Tablet

Why You Can't Dose a Child From an Adult Tablet You cannot reliably turn an adult medication into a child's dose just by cutting the tablet smaller. That can be frustrating to hear at 9 p.m. when the children's ibuprofen bottle is empty, the pharmacy is closed, and...

read more
What is Plague?

What is Plague?

What Is Plague? By the Jase Medical Team Plague is back in the headlines, and people are suddenly Googling a disease they may not have thought about since history class. A 28-year-old laboratory worker at an anti-plague research institute in Siberia recently died...

read more

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

Why You Can’t Dose a Child From an Adult Tablet

Why You Can’t Dose a Child From an Adult Tablet

You cannot reliably turn an adult medication into a child’s dose just by cutting the tablet smaller.

That can be frustrating to hear at 9 p.m. when the children’s ibuprofen bottle is empty, the pharmacy is closed, and the only thing in the medicine cabinet is the adult version.

The temptation is obvious. Look up the dose, do a little math, cut the tablet, and make it work.

But pediatric medication dosing is not just smaller adult dosing. A child’s weight matters. The formulation matters. The concentration matters. The way the medication releases into the body matters.

And the place pediatric medication errors often happen is not necessarily in determining what medication a child needs. It is translating the prescribed dose into what actually goes into the child’s mouth.

Instead of learning how to improvise, there are four things parents can check now that make improvisation much less likely later.

1. Know Your Child’s Current Weight in Kilograms

Pediatric medications are often dosed based on weight, which means the number you remember from last year’s physical may no longer be particularly useful.

Children grow quickly.

Keep your child’s current weight somewhere accessible and record it in kilograms as well as pounds. If you only know pounds, ask your child’s healthcare provider to confirm the current kilogram weight at their next visit.

This is particularly useful when you’re calling an after-hours nurse line, speaking with an unfamiliar clinician, or trying to answer questions while traveling.

The goal is not to calculate a dose yourself.

The goal is to give the clinician or pharmacist accurate information so they can.

2. Check the Concentration on the Bottle

Two bottles can contain the same medication without giving you the same amount of medication in the same volume of liquid.

That’s why instructions for one product should not automatically be transferred to another bottle simply because the medication name looks familiar.

Before giving a liquid medication, look at the label for the concentration. It will typically tell you how many milligrams of medication are contained in a specific number of milliliters.

Then use the instructions provided for that specific medication and formulation.

This is also why remembering that your child “usually gets 5 mL” is not enough. Milliliters tell you how much liquid you’re giving. The concentration tells you how much medication is inside that liquid.

If the product has changed, confirm the dose rather than assuming the old volume still applies.

3. Use the Syringe, Not a Kitchen Spoon

A teaspoon sounds like a standard measurement.

The spoon in your silverware drawer is not.

Household spoons vary significantly in size, which makes them a poor tool for measuring medication. Research has also found that medication dosing errors are more common when parents use teaspoon-based instructions rather than milliliter-only instructions.

The measuring device matters too.

Studies have found fewer dosing errors with oral syringes than with dosing cups, particularly when measuring smaller amounts.

So if a children’s liquid medication comes with an oral syringe, keep the syringe with the medication and use the markings on it.

Measure in milliliters. Skip the kitchen spoon.

It’s a small change that removes one unnecessary opportunity for error.

4. Know Which Medications You Should Not Improvise

This is where the adult tablet becomes particularly problematic.

Even if you know your child’s weight, that does not mean you can calculate a pediatric dose and create it by cutting an adult tablet.

Some tablets are coated or manufactured specifically to control where or how quickly the medication is released. Labels such as EC, SR, ER, XR, or XL can indicate formulations that should not simply be crushed, split, or altered without professional guidance.

Even tablets that can physically be split do not necessarily divide into perfectly equal amounts of medication.

And pediatric dosing can leave much less room for error than simply estimating half a tablet or a quarter of a tablet.

If the children’s medication you need isn’t available, call your child’s pediatrician, an after-hours clinical line, or a pharmacist for guidance rather than trying to convert an adult tablet yourself.

What About Children’s Dosing Charts by Age?

Age-based charts are convenient, but weight is often more useful for pediatric medication decisions.

Two healthy 6-year-olds can weigh very different amounts. Growth patterns also change over time, which means broad age categories cannot account for every child.

If a medication’s official label provides age-based instructions, follow the product labeling and your child’s healthcare provider’s guidance. But don’t use a general age chart from the internet to reverse-engineer an adult medication into a pediatric dose.

If you have access to your child’s current weight, give that information to the clinician or pharmacist helping you.

Why Adult Tablets Aren’t a Backup Plan

It can feel wasteful to keep a separate children’s formulation when the medicine cabinet already contains an adult version of the same medication.

But the formulation is part of the safety system.

A pediatric liquid lets the appropriate amount be measured much more precisely. Its label provides the concentration. Its measuring device is designed for small volumes. And when the medication is prescribed, the formulation can be selected specifically for the child.

An adult tablet removes many of those safeguards and leaves the parent trying to recreate them at the kitchen counter.

That’s not the kind of medical preparedness we want families relying on.

The Four-Point Pediatric Medication Check

You don’t need to memorize pediatric dosing calculations to be better prepared.

Instead, check four things:

  1. Current weight: Do you know your child’s current weight in kilograms?
  2. Concentration: Have you checked the concentration printed on the medication you’re actually holding?
  3. Measuring device: Do you have the appropriate oral syringe or dosing device with it?
  4. Medication restrictions: Do you know whether the medication and formulation are appropriate for your child’s age?

If your child takes a prescription medication every day, add one more layer. Keep a written record of the drug, dose, prescriber, and pharmacy somewhere another caregiver could access it.

That is far more useful than hoping someone can reconstruct the information from memory when your child is sick.

Pediatric Preparedness Should Reduce Improvisation

At Jase Medical, we’re a family team of physicians, PAs, and pharmacists. We built KidCase for children ages 2 to 11 around the same principle: parents shouldn’t have to improvise pediatric medication from adult supplies when normal access to care is disrupted.

KidCase provides pediatric formulations and dosing selected for the individual child after a licensed provider reviews each request.

It is intended for emergency use only, after first trying to reach your child’s healthcare provider. It complements your child’s regular pediatric care rather than replacing it.

Because good medical preparedness isn’t about becoming your child’s pharmacist at the kitchen counter.

It’s about having the right information, the right formulation, and a plan already in place before Saturday night arrives and the children’s bottle is empty.

The goal isn’t to get better at improvising. It’s to make improvisation unnecessary.


The Jase Medical Team is a family team of medical doctors, PAs, and pharmacists focused on appropriate medical preparation: clinically grounded readiness that complements, rather than replaces, the healthcare professionals you already trust.

This article was prepared by the Jase Medical content team for informational purposes only and does not constitute medical advice. Prescription requirements, emergency dispensing rules, insurance coverage, and controlled-substance regulations vary by medication, jurisdiction, and individual circumstances. Consult a licensed healthcare provider or pharmacist regarding your specific medications.

Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

Why You Can’t Dose a Child From an Adult Tablet

Why You Can’t Dose a Child From an Adult Tablet

Why You Can't Dose a Child From an Adult Tablet You cannot reliably turn an adult medication into a child's dose just by cutting the tablet smaller. That can be frustrating to hear at 9 p.m. when the children's ibuprofen bottle is empty, the pharmacy is closed, and...

read more
What is Plague?

What is Plague?

What Is Plague? By the Jase Medical Team Plague is back in the headlines, and people are suddenly Googling a disease they may not have thought about since history class. A 28-year-old laboratory worker at an anti-plague research institute in Siberia recently died...
read more

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

For Clinicians | Pediatric Dosing 101: What Parents Need From You Before They’re Dosing Alone

For Clinicians | Pediatric Dosing 101: What Parents Need From You Before They’re Dosing Alone

By Dr. Jamie Wilkey, PharmD, Director of Clinical Education
Medically reviewed and edited by Aaron Asay, PA-C, DMSc, FIBODM, FAWM

Pharmacy school drills one line into you over and over again: children are not small adults. A child’s body absorbs, distributes, and clears a drug on a different timeline than yours does, and the margin around a correct dose is narrower because there’s less child to absorb the error. That’s why every pediatric dose is calculated from weight instead of pulled off a standard adult label.

That’s complicated, but not too hard when a pharmacist or prescriber is just a phone call or message away for parents dosing their kids.  It’s a different problem at 9pm when nobody is reachable and a parent is reading a label written in mg/kg and only knows their child’s weight in pounds.

Today we are going to talk about appropriate medical preparation in children and how to help train parents with pediatric dosing at home. I’ve seen a lot of pediatric dosing errors in my years in practice and I want to help as much as I can to prevent these going forward, especially when information is limited for parents. 

Why children often need more drug per kilogram, not less

The elimination machinery grows up early, and glomerular filtration rate reaches adult levels by 8 to 12 months¹, so by the time a child is 2, the kidneys are clearing drugs roughly the way yours do. What stays different through the grade-school years is body composition and liver metabolism, because a higher share of a child’s weight is water, which spreads water-soluble drugs through a larger relative volume, and phase I metabolism runs above adult rates for some drugs through the first few years¹.

It feels backwards that per kilogram kids often need more than you do rather than less, but a 20 kg child on high-dose amoxicillin for an ear infection takes 1,800 mg a day² while an adult on 875 mg twice daily takes 1,750 mg, which means the 44 pound patient is taking more than the grown-up. That’s not always the case, since I used a high dose example, but it illustrates the point well. Parents round down because it feels safer, and a rounded-down antibiotic course won’t reach therapeutic levels. 

Pediatric dosing is weight-based, and the weight is in kilograms

Every pediatric dose starts from a number the parent usually doesn’t have: their child’s weight in kilograms. Medication doses are written in mg/kg while bathroom scales read pounds, and that conversion is the first place the dose goes wrong. Pounds divided by 2.2 gives kilograms, so a 40 pound child is 18 kg. A parent should be able to run that calculation themselves rather than guessing at it. A tired, sleep-deprived parent doing it at 1am on a phone calculator is introducing risk into the dosing, and they don’t have the clinician spidey sense that goes off when a result comes out too high or too low.

For a family that has a scale but a child who won’t hold still on it, the trick is subtraction: weigh the adult alone, weigh the adult holding the child, and the difference is the child’s weight. When nobody can weigh at all, the current APLS estimates are (age x 2) + 8 kilograms for ages 1 to 5 and (age x 3) + 7 for ages 6 to 12³, though both of them run low, so treat the result as a rough estimate rather than a real answer.

2 places the dose goes wrong after the math is right

If you hand a parent nine doses to measure, 84.4% will get at least one of them wrong, and one in five will be off by more than double on at least one⁴. That was 2,110 parents of children 8 and under, measuring in a study and under observation, with no sick kid howling on their shoulder and none of the sleep deprivation that comes with the real version of that night.

The units are the first of those two places, and here again they confuse parents: the ol’ mL versus teaspoon conundrum. Parents who think in teaspoons reach for a kitchen spoon 30% of the time, while parents who think in milliliters do it 1% of the time⁵, and dosing cups carry more than four times the odds of an error against an oral syringe⁴. Send an oral syringe home whenever you can. I know as a pharmacist I always gave them away for free from behind the counter when patients asked.

Concentration is the second place that errors can be introduced, and it’s the one a good syringe can’t rescue, because a dose in mg/kg gives you milligrams while the bottle is marked in milliliters, and the strength changes from bottle to bottle. Amoxicillin suspension is dispensed at 125, 200, 250, or 400 mg per 5 mL⁶, so the same 5 mL can be three times the dose depending on which bottle came home, and infant ibuprofen drops are double the concentration of the children’s suspension at 40 mg per mL against 20⁷, which matters in any house with a toddler and a second grader keeping both. A volume that worked last time only works again if the strength matches, so have parents read the concentration off the label every time, even on a refill of the same drug.

Accidental double doses to watch out for

Families unintentionally go over the 24-hour maximum in two ways. The first is that acetaminophen turns up inside products that don’t say Tylenol anywhere on the front, so a parent treating a fever with one bottle and a cough with another can give two full doses of the same drug in the same hour without ever seeing it happen. DayQuil and NyQuil Cold & Flu both carry it acetaminophen, as do Theraflu and Mucinex Fast-Max, along with the prescription pain combinations built on it, and ibuprofen hides the same way inside Advil Cold & Sinus and Advil PM.

The second way is simpler: when a parent alternates acetaminophen and ibuprofen through a long night and by midnight it can start to get confusing what went in when. I’ve found that in my own family, writing down the medication, the dose, and the time it was given keeps those long, tired nights clear.

What to send home before they need it

Everything above is executable at 1am only if the parent already has the pieces and basic know-how. Send them home with the child’s weight in kilograms written somewhere they’ll find it, an oral syringe, and the habit of checking the concentration on whatever bottle they’re holding, plus a written drug, dose, prescriber and pharmacy list for any child on daily medication. Parents can also put in Google 25lbs to kg and they can get an answer without having to do math themselves (or use it to double check their own math). Also this is obvious, but worth mentioning that obviously kids are growing, the weight at their physical 9 months ago, might not be accurate anymore! 

All of that assumes there’s something in the cabinet to measure, which is where the real gap sits: a family’s options are a reachable prescriber with an open pharmacy, or nothing, with no sanctioned middle where an age-appropriate formulation is already in the house at a strength that matches the child. Appropriate medical preparation is the name for that middle layer, and it’s what Jase builds for ages 2 through 11, with a licensed provider reviewing every request and writing the prescription. It’s for emergency use only, after first seeking the assistance of a qualified healthcare provider, and it’s in no way a replacement for the pediatrician who knows the child.

The bottom line

Pediatric dosing goes wrong a few ways in the translation and the math. The things parents need to succeed are: the weight in kilograms, an oral syringe, the concentration on the bottle in front of them and what their child’s dose clearly is (for Rx medications). If you’d rather not run it with every family, refer them to us and we’ll do the clinical work on the front end.


Sources

  1. Merck Manual Professional Edition. Pharmacokinetics in Children. https://www.merckmanuals.com/professional/pediatrics/principles-of-drug-treatment-in-children/pharmacokinetics-in-children
  2. American Academy of Pediatrics. The Diagnosis and Management of Acute Otitis Media. Pediatrics. 2013;131(3):e964. High-dose amoxicillin 80 to 90 mg/kg/day in two divided doses. https://publications.aap.org/pediatrics/article/131/3/e964/30912/The-Diagnosis-and-Management-of-Acute-Otitis-Media
  3. Advanced Life Support Group. Advanced Paediatric Life Support: The Practical Approach, 5th edition. Oxford: Blackwell, 2011. Formulas as described in Ali K, Sammy I, Nunes P. Is the APLS formula used to calculate weight-for-age applicable to a Trinidadian population? BMC Emergency Medicine. 2012;12:9. https://pmc.ncbi.nlm.nih.gov/articles/PMC3506443/
  4. Yin HS, Parker RM, Sanders LM, et al. Liquid Medication Errors and Dosing Tools: A Randomized Controlled Experiment. Pediatrics. 2016;138(4):e20160357. https://publications.aap.org/pediatrics/article-abstract/138/4/e20160357/52278/
  5. Eunice Kennedy Shriver National Institute of Child Health and Human Development. Spoon measurements contribute to many child drug-dosing errors. August 29, 2014. Describing Yin HS et al., Unit of Measurement Used and Parent Medication Dosing Errors, Pediatrics 2014. https://www.nichd.nih.gov/newsroom/releases/082914-podcast-pediatric-med-dosing
  6. AMOXIL (amoxicillin) prescribing information. US Food and Drug Administration. Powder for oral suspension 125 mg/5 mL, 200 mg/5 mL, 250 mg/5 mL, 400 mg/5 mL. https://www.accessdata.fda.gov/drugsatfda_docs/label/2015/50542s02950754s01950760s01950761s016lbl.pdf
  7. Institute for Safe Medication Practices. Don’t Mix Up Concentrated “Ibuprofen Infant Drops” with “Children’s Ibuprofen.” https://www.consumermedsafety.org/safety-articles/dont-mix-up-concentrated-ibuprofen-infant-drops-with-childrens-ibuprofen


Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

Why You Can’t Dose a Child From an Adult Tablet

Why You Can’t Dose a Child From an Adult Tablet

Why You Can't Dose a Child From an Adult Tablet You cannot reliably turn an adult medication into a child's dose just by cutting the tablet smaller. That can be frustrating to hear at 9 p.m. when the children's ibuprofen bottle is empty, the pharmacy is closed, and...

read more
What is Plague?

What is Plague?

What Is Plague? By the Jase Medical Team Plague is back in the headlines, and people are suddenly Googling a disease they may not have thought about since history class. A 28-year-old laboratory worker at an anti-plague research institute in Siberia recently died...

read more

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

What is Plague?

What Is Plague?

By the Jase Medical Team

Plague is back in the headlines, and people are suddenly Googling a disease they may not have thought about since history class.

A 28-year-old laboratory worker at an anti-plague research institute in Siberia recently died after developing pneumonia of unknown origin. Unofficial reports raised the possibility of pneumonic plague, but Russian health authorities say testing has not identified plague or another dangerous pathogen associated with her work. The World Health Organization has assessed the broader public health risk as low while continuing to seek information.

In other words, we don’t know that this was plague, and we’re not going to guess.

But the headlines offer a good reason to answer a more useful question:

What actually is plague?

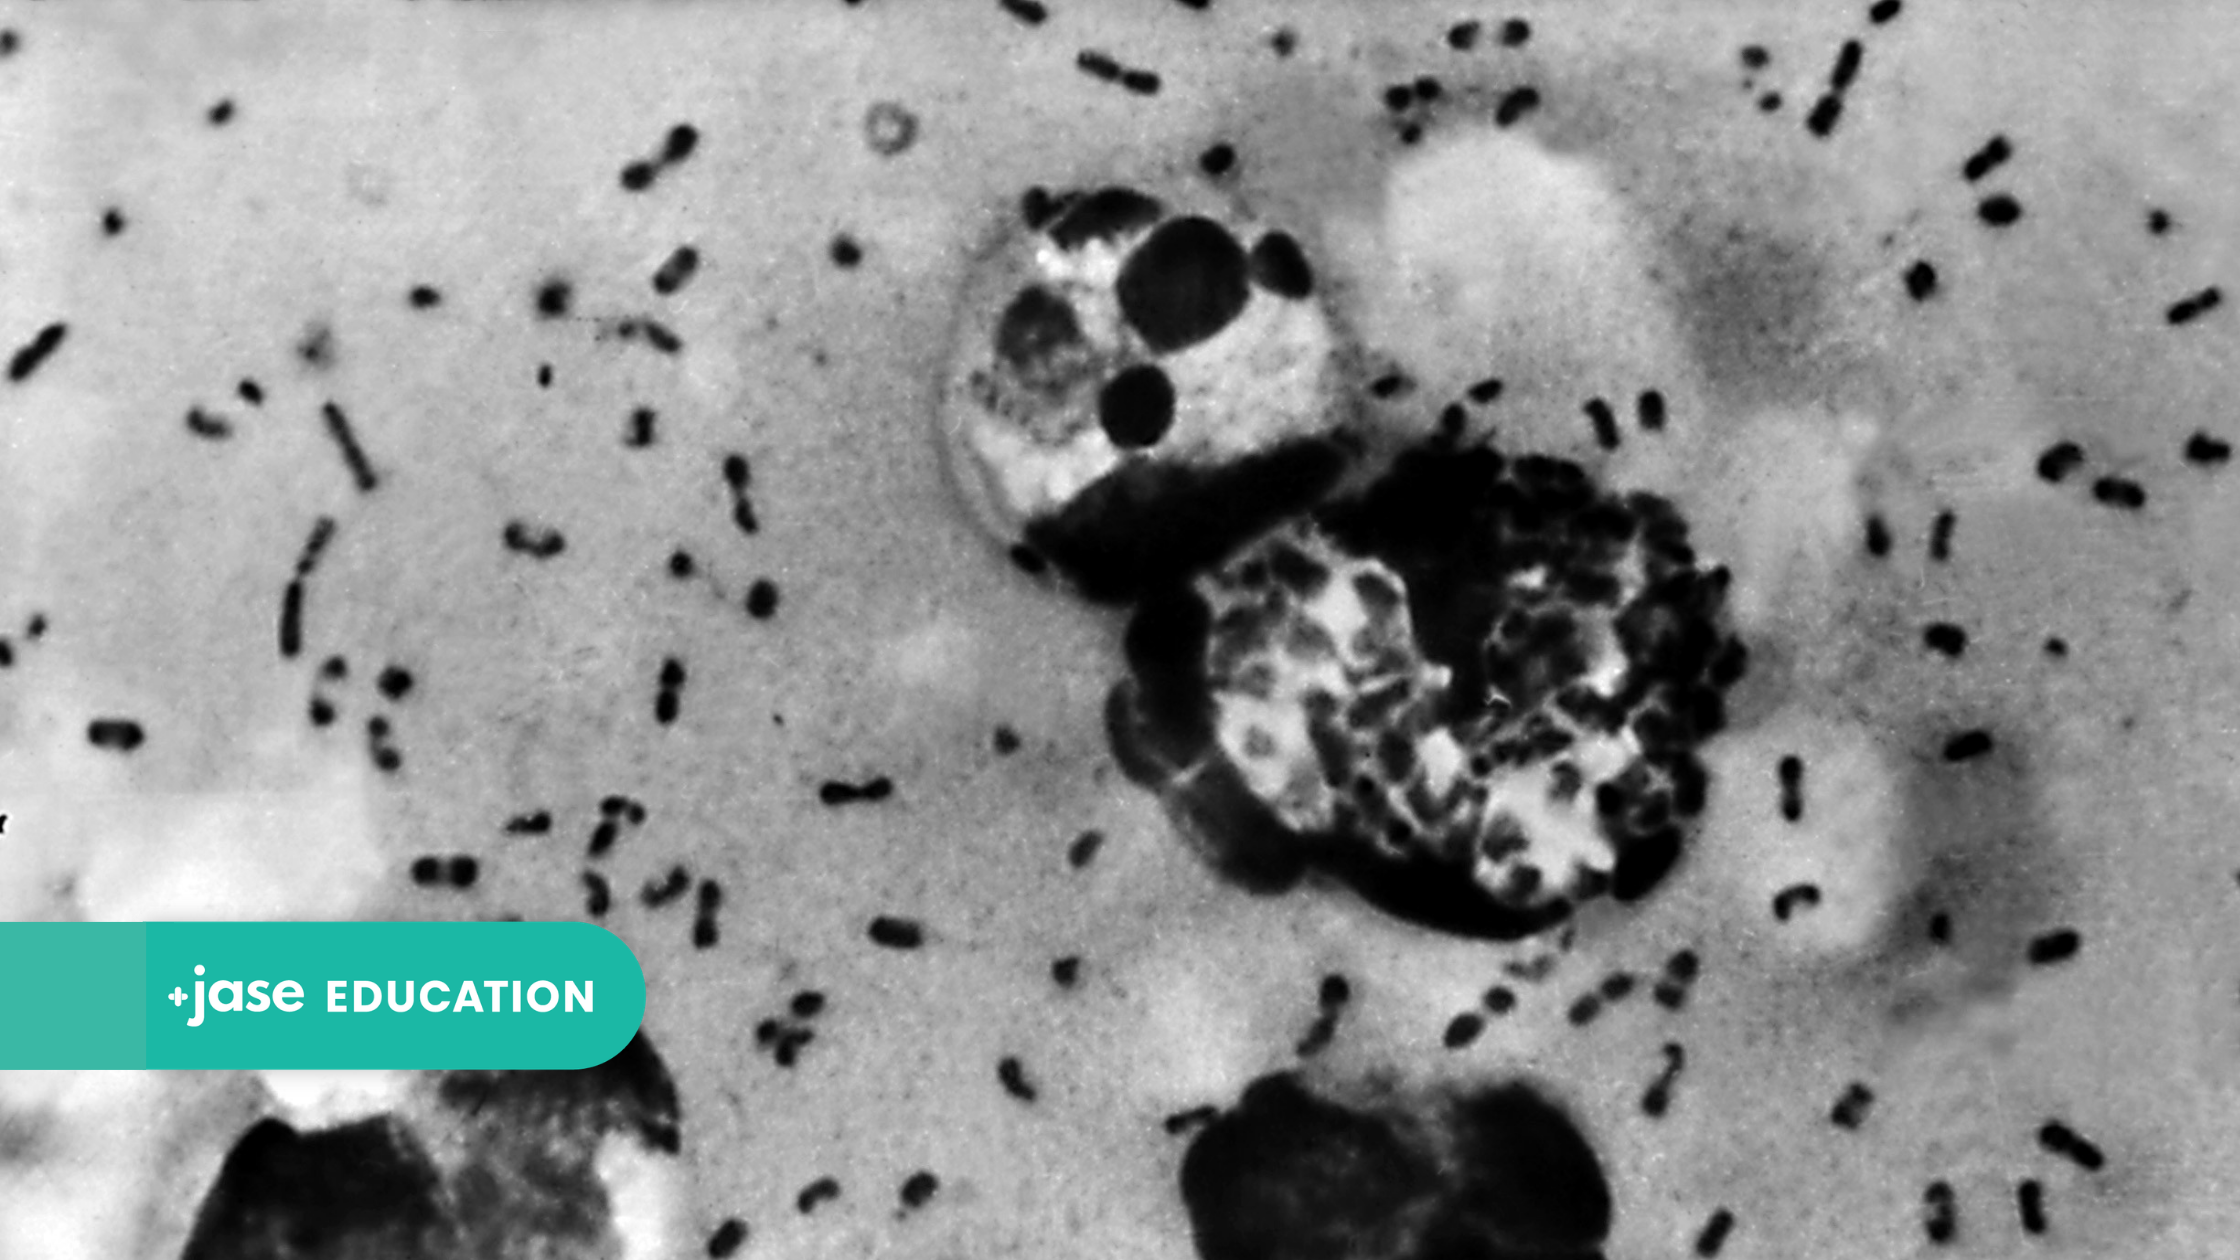
The simplest explanation is this: one bacterium can cause three major forms of disease, depending largely on where the infection takes hold in the body.

That bacterium is Yersinia pestis.

And despite its medieval reputation, plague still exists today.

First Myth: Plague Is Not a Virus

Plague is a bacterial infection.

That’s an important distinction because bacterial plague can be treated with antibiotics. Prompt diagnosis and treatment dramatically improve the odds of survival.

Before effective antibiotics became available, about two out of every three documented U.S. plague cases with known outcomes were fatal. After antibiotics were introduced, that fell to roughly one in six.

Treatment matters, and timing matters.

Untreated plague can progress rapidly, particularly when the bacteria reach the bloodstream or lungs.

One Bacterium, Three Diseases

The three forms you’ve probably heard about are bubonic, septicemic, and pneumonic plague.

They’re not three unrelated diseases. They’re different manifestations of infection with the same bacterium.

Think of it as a question of location.

Bubonic Plague: The Lymph Nodes

This is the classic form associated with the Black Death, and it’s still the most common form seen in the United States.

An infected flea bites a person and introduces Yersinia pestis through the skin. The bacteria can then travel through the lymphatic system to a nearby lymph node, where they multiply.

The result can be a dramatically swollen and painful lymph node called a bubo.

People may also develop sudden fever, chills, headache, weakness, and other signs of serious infection.

More than 8 in 10 U.S. plague cases have been bubonic.

Without prompt treatment, however, the bacteria don’t necessarily stay in the lymph node. They can spread elsewhere in the body.

Septicemic Plague: The Bloodstream

When Yersinia pestis infects the bloodstream, the result is septicemic plague.

It can develop as a complication of bubonic plague, or infection can sometimes present primarily in the bloodstream without an obvious bubo.

People can develop fever, severe weakness, abdominal symptoms, shock, bleeding, and tissue damage as the infection progresses.

This is one reason plague isn’t always as visually obvious as the history-book version. Someone doesn’t necessarily develop a giant swollen lymph node first.

Pneumonic Plague: The Lungs

When plague infects the lungs, it’s called pneumonic plague.

This is the fastest-moving and most dangerous major form. It can develop when untreated infection elsewhere in the body spreads to the lungs, or someone can develop primary pneumonic plague after inhaling infectious respiratory droplets.

Pneumonic plague is also the form that can spread from one person to another through respiratory droplets during close contact.

That doesn’t mean plague spreads casually through a community like a common cold. Person-to-person transmission requires exposure to someone with pneumonic plague, and public health officials can use antibiotics, isolation, and monitoring of close contacts to interrupt transmission.

But suspected pneumonic plague is treated seriously because illness can progress rapidly.

Is Plague Contagious?

Sometimes.

Bubonic plague is usually acquired from an infected flea or through contact with an infected animal. It doesn’t ordinarily spread from person to person.

Pneumonic plague is different because infection in the lungs can produce infectious respiratory droplets.

So when someone asks, “Is plague contagious?” the better answer is:

It depends on the form.

That’s one of the reasons understanding the three forms matters.

Is Plague Curable?

Plague is treatable with antibiotics, and treatment should begin as quickly as possible when plague is suspected.

That fact completely changed the disease’s prognosis.

Historical U.S. data show that about 66% of documented plague cases were fatal before antibiotics became available. After their introduction, overall mortality fell dramatically.

But modern treatment doesn’t make plague harmless. Pneumonic and septicemic disease can progress particularly quickly, and delays in treatment increase the danger.

This is not an infection to watch at home and see how you feel tomorrow.

Is Plague Still in the United States?

Yes, but it’s rare.

The United States averages about seven human plague cases per year, and most occur in rural areas of the West.

Cases are concentrated particularly in parts of New Mexico, Arizona, Colorado, California, Oregon, and Nevada, where Yersinia pestis circulates among wild rodents and their fleas.

That means the person who should actually know a little about plague isn’t necessarily someone worried about an international headline.

It may be someone who hikes, camps, hunts, works outdoors, or lives around wildlife in the rural West.

Fleas, Rodents, and Yes, Your Cat

Plague is fundamentally a zoonotic disease, meaning it can move between animals and humans.

Rodents and their fleas play an important role in maintaining the bacteria in the environment. When an infected animal becomes sick or dies, fleas can seek another host.

That can include humans.

People can also become infected through direct contact with tissues or fluids from an infected animal.

And domestic animals aren’t automatically outside that equation.

Cats can become infected after encountering infected rodents or fleas, and human plague cases have been associated with contact with infected cats. If you live in or travel through an area where plague occurs, flea control for pets isn’t simply about keeping them comfortable.

It’s part of reducing exposure.

What Should You Actually Do About Plague?

For most Americans, plague doesn’t require a new preparedness protocol.

If you’re spending time outdoors in areas where plague occurs, use insect repellent as appropriate, keep fleas off pets, avoid handling sick or dead wild animals with bare hands, and don’t encourage rodents to live around your home or campsite.

If you need to handle a potentially infected animal, use appropriate protection rather than direct bare-hand contact.

And pay attention to symptoms after a plausible exposure.

A sudden fever accompanied by an unusually painful, swollen lymph node deserves prompt medical evaluation, particularly after time in an area where plague occurs or after contact with rodents, fleas, or a sick animal.

Tell the healthcare professional where you’ve been and what you’ve been around.

Those details can make a rare diagnosis easier to recognize.

A Scary Headline Becomes Less Scary When You Understand the Disease

The current situation in Siberia is still being investigated. Russian authorities have not confirmed plague as the cause of the laboratory worker’s death, and international health officials continue to seek information.

That’s where the facts stop.

We don’t need to fill the gap with speculation.

At Jase Medical, we’re a family team of medical doctors, PAs, and pharmacists, and we’d rather explain a scary medical word than simply repeat it.

Plague is not a mysterious medieval force. It’s a bacterial infection caused by Yersinia pestis. It can take three major forms depending on where the infection develops. Bubonic plague affects the lymphatic system. Septicemic plague involves the bloodstream. Pneumonic plague affects the lungs and can spread between people through respiratory droplets.

It still occurs in the United States, but it’s rare. And unlike during the Black Death, we have effective antibiotics to treat it when it’s recognized and treated promptly.

So if plague appears in your news feed, remember the framework:

One bacterium. Three major forms. Early treatment matters.

And if you’re one of the Americans who actually lives, works, hikes, hunts, or camps where plague occurs, the practical advice is much less dramatic than the headline:

Avoid fleas. Be careful around wild animals. And if sudden fever and a painful swollen lymph node appear after a possible exposure, get seen quickly and tell them where you’ve been.


The Jase Medical Team is a family team of medical doctors, PAs, and pharmacists focused on appropriate medical preparation: clinically grounded readiness that complements, rather than replaces, the healthcare professionals you already trust.

This article was prepared by the Jase Medical content team for informational purposes only and does not constitute medical advice. Prescription requirements, emergency dispensing rules, insurance coverage, and controlled-substance regulations vary by medication, jurisdiction, and individual circumstances. Consult a licensed healthcare provider or pharmacist regarding your specific medications.

Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

Why You Can’t Dose a Child From an Adult Tablet

Why You Can’t Dose a Child From an Adult Tablet

Why You Can't Dose a Child From an Adult Tablet You cannot reliably turn an adult medication into a child's dose just by cutting the tablet smaller. That can be frustrating to hear at 9 p.m. when the children's ibuprofen bottle is empty, the pharmacy is closed, and...

read more
What is Plague?

What is Plague?

What Is Plague? By the Jase Medical Team Plague is back in the headlines, and people are suddenly Googling a disease they may not have thought about since history class. A 28-year-old laboratory worker at an anti-plague research institute in Siberia recently died...

read more

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!