For Clinicians | Tamiflu After 48 Hours, Paxlovid After 5 Days

For Clinicians | Tamiflu After 48 Hours, Paxlovid After 5 Days: Antiviral Timing for Flu and COVID

By Dr. Jamie Wilkey, PharmD, Director of Clinical Education
Medically reviewed and edited by Kristen Carpenter, PA-C

As the weather turns colder, every retail pharmacist I know is bracing for the Tamiflu rush. Yep, it’s that time again. We’re heading into the season of getting together, which means shared memories…… and a whole lot of shared germs.

I’m writing this early so we can all brush up on current antiviral recommendations before the first patient asks, in the office or at the pharmacy counter, whether it’s too late for Tamiflu. Today we’re covering the 48-hour window, who it actually applies to, why COVID runs on a different clock, and how much these drugs help.

Is it too late to take Tamiflu after 48 hours?

For an otherwise healthy adult, usually yes. The Tamiflu label covers patients who’ve had symptoms for no more than 48 hours¹, and the CDC says healthy outpatients can be treated on clinical judgment if treatment starts within two days of illness onset². We made the short version of this point in our August article on disease after disasters: for flu, a patient doesn’t need a positive test to start treatment. They need a prescriber, and they need to reach one in time.

The 48-hour window comes from how the drug works. Oseltamivir blocks neuraminidase, the enzyme flu needs to spread from an infected cell to healthy ones³, so it can only slow a virus that’s still spreading. In volunteer challenge studies, viral shedding peaked around day two, a day before symptoms hit their worst⁴. By the time a healthy patient feels terrible, the virus is already on its way down.

I know many of my patients have unrealistic expectations for what an antiviral can do. Started on time, Tamiflu gets a typical patient back on their feet about a day sooner¹. That may not sound like much, but ask anyone laid out miserable on the couch with a fever if they’d take one less day of it. So it can shorten the misery, but it isn’t a magical solution that solves a viral illness instantly.

Why doesn’t the 48-hour rule apply to high-risk patients?

For a high-risk patient, the answer does a complete 180: treat them! No matter how long they’ve been sick. CDC recommends antiviral treatment as soon as possible for anyone with suspected or confirmed flu who is hospitalized, has severe, complicated, or progressive illness, or is at higher risk for complications². That last group is way bigger than it sounds because it includes: adults 65 and older, pregnant patients, and anyone with a chronic condition like asthma, diabetes, or heart disease⁵. So now, as I write that out, it feels like half my patient list. Don’t wait on a test, either. A negative rapid test doesn’t rule out flu, and CDC says not to withhold treatment because of one⁶.

And now that we’re talking about high-risk patients please please remember that the goal changes with the patient. In a healthy adult, we’re shaving off a day of misery. In an 80-year-old with heart failure, we’re trying to keep them out of the hospital. And, dang it, the virus doesn’t always work on schedule: critically ill patients can keep replicating the virus longer than healthy patients². The evidence for a late start is observational, not randomized, but it points toward treating².

CDC says even higher-risk patients aren’t always getting prescribed antivirals⁷. So when an older patient asks at the counter, or calls the office on day three, whether it’s too late for Tamiflu, the answer is no. You can still prescribe it, and it can still help.

Why does COVID get 5 days instead of 2?

Because that’s where the trials determined it should be. Paxlovid’s main trial, EPIC-HR, enrolled high-risk patients within 5 days of symptom onset⁸, and the outpatient remdesivir trial enrolled them within 7⁹. COVID also gives us more runway than flu: in early-pandemic data, patients sick enough to be hospitalized usually started struggling to breathe.¹⁰. IDSA’s 2025 update strongly recommends Paxlovid for high-risk adults and keeps molnupiravir as a fallback¹¹.

So a patient on day 3 can be late for Tamiflu and right on time for Paxlovid. And here’s the plot twist: for COVID, you need the test that confirms it is actually COVID. Paxlovid starts after a COVID-19 diagnosis has been made⁸. You can’t pick the drug until you know which virus you’re treating.
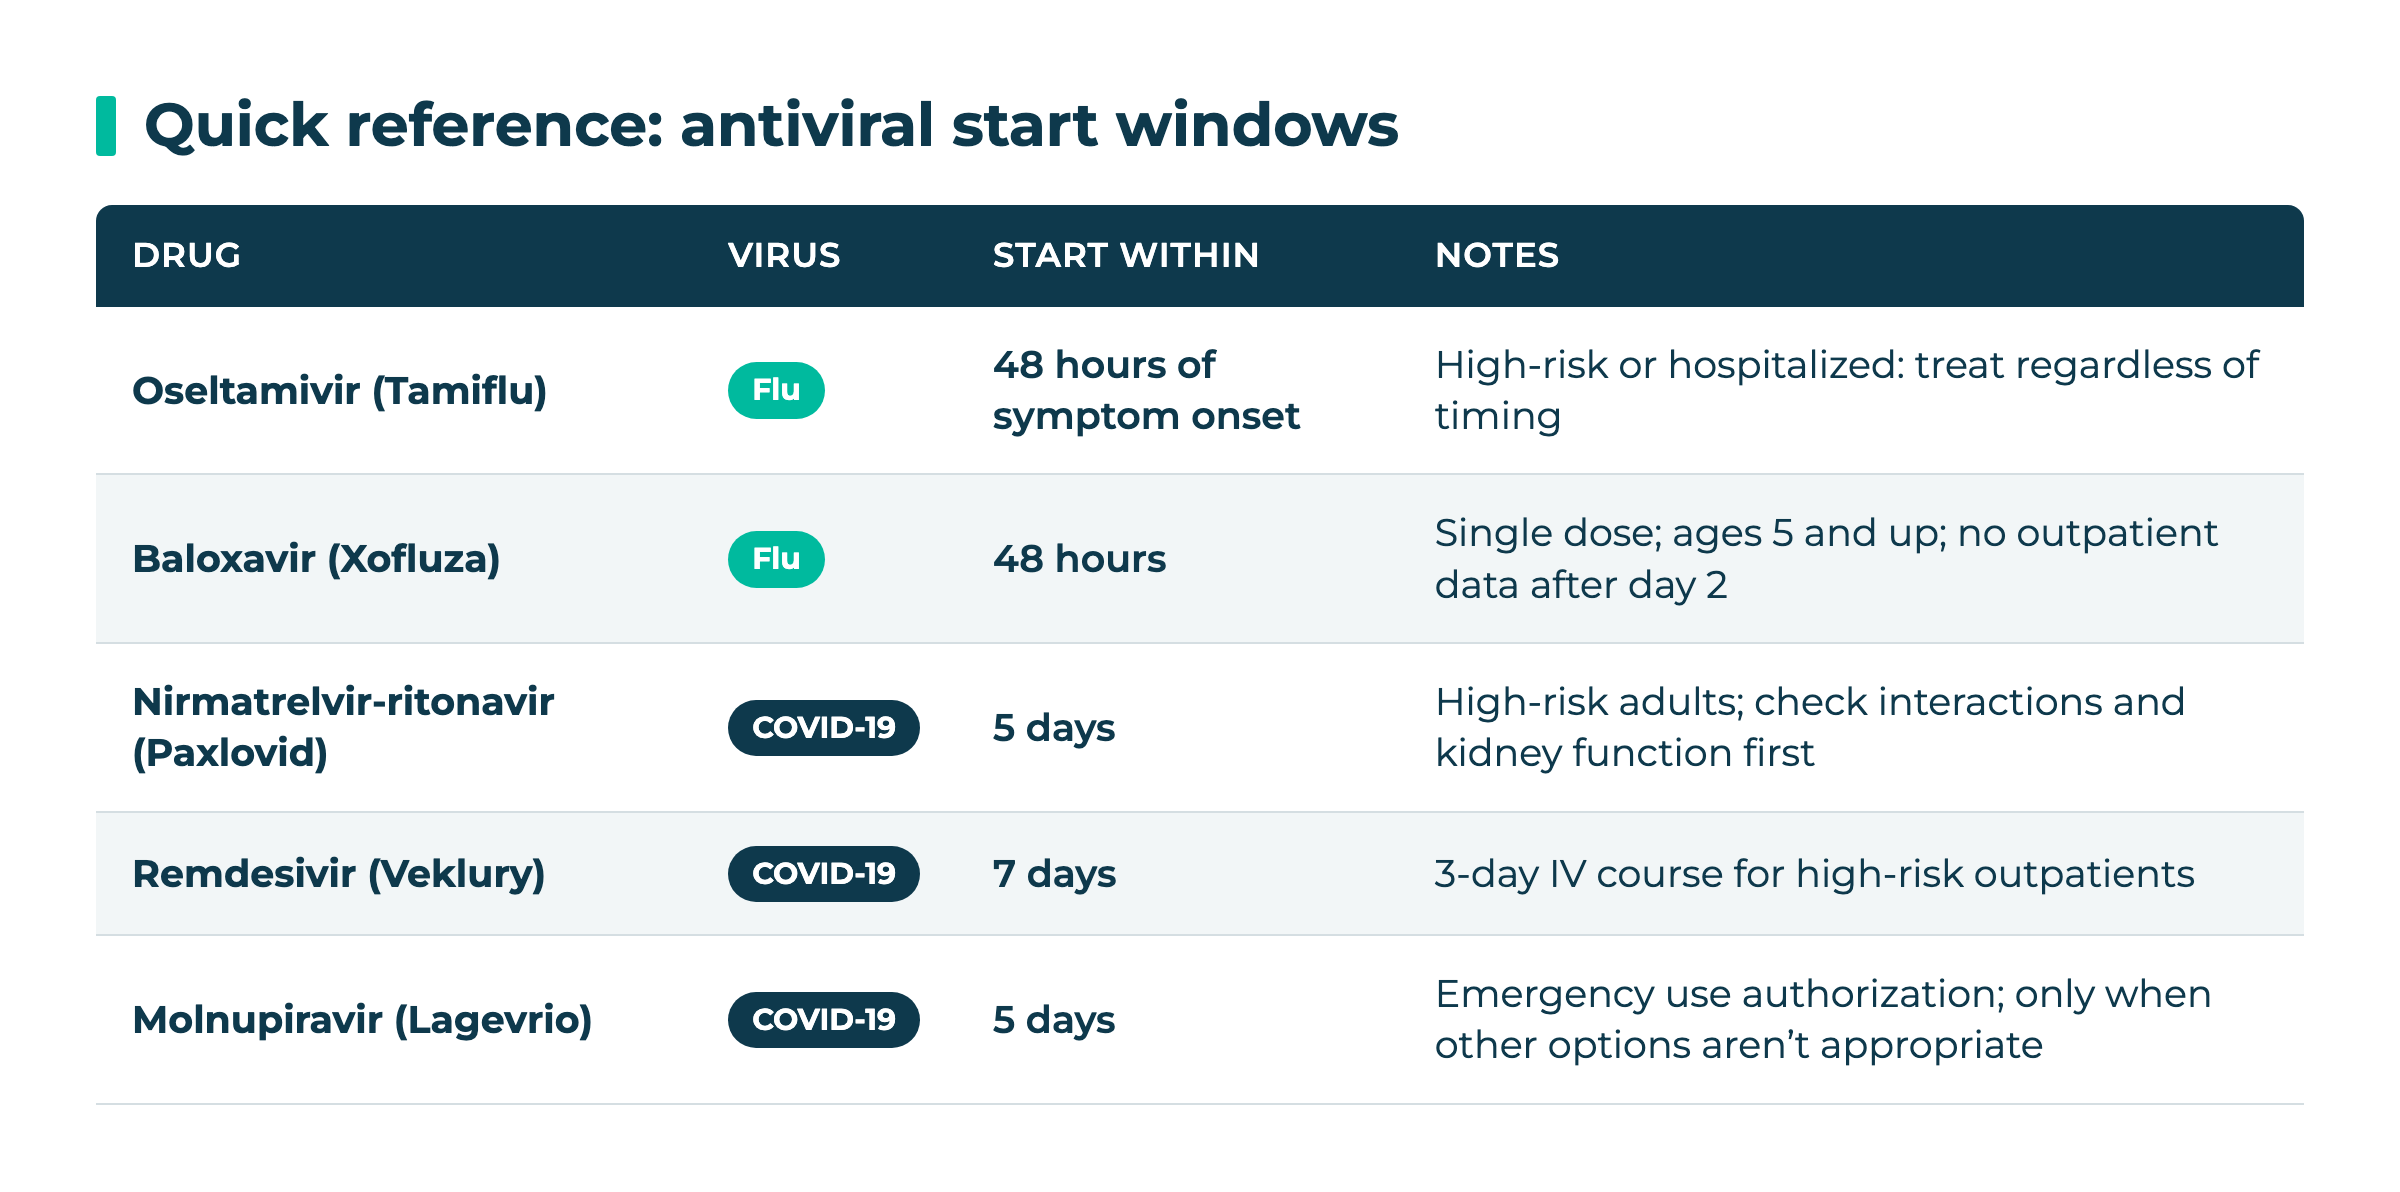
Any antiviral a patient keeps on hand is for emergency use only, after first seeking the assistance of a qualified healthcare provider.

What has to be checked before Paxlovid?

Two things. The medication list + the kidneys.

Ritonavir has one job. It blocks CYP3A so the body can’t clear nirmatrelvir as fast, which keeps the antiviral level up⁸. It doesn’t pick favorites, though. It blocks CYP3A for everything else the patient takes, too. The most commonly reported serious interactions involved tacrolimus and cyclosporine, followed by calcium channel blockers⁸, and that last group shows up on a lot of our older patients’ lists. Some conflicts are workable: simvastatin and lovastatin are contraindicated, but they can be held from 12 hours before the first dose until 5 days after the last⁸. St. John’s Wort is on the contraindicated list too, so the medication list you check has to include OTCs and supplements.

Then check renal function. The label reduces the dose when eGFR falls below 60, dialysis included⁸.

How much do antivirals actually help?

Prescribe them for the high-risk patient. And be candid with everyone else about the size of the benefit.

For flu, the clearest benefit is the day of symptoms from earlier. Whether Tamiflu keeps outpatients out of the hospital is less clear: a 2024 meta-analysis of 15 randomized trials found no significant drop in hospitalization, older and high-risk subgroups included¹⁵. That’s why the high-risk recommendation leans on observational data².

For COVID, the gap is immunity. EPIC-HR enrolled only unvaccinated high-risk adults with no prior infection, and Paxlovid cut hospitalization or death from 6.5% to 0.9%⁸. EPIC-SR included vaccinated high-risk adults, and there Paxlovid didn’t shorten symptoms, and the drop in hospitalization or death didn’t reach significance⁸. By late 2022, nearly all US blood donors had antibodies from vaccination, infection, or both¹⁶, so most of our patients today look more like the second trial than the first.

The evidence still points one direction. The benefit is biggest in the patients most likely to end up in the hospital, and those are the patients the 48-hour-or-nothing myth talks us out of treating.

What happens when the patient can’t reach a prescriber in time?

Antiviral care runs all or none. Either the patient reaches a prescriber inside the window, or the clock runs out while they wait for an appointment or for Monday to roll around.

A lot of the clinical work doesn’t need a sick patient, though. You can tell a high-risk patient to call on day one, not day four. You can flag the simvastatin or the tacrolimus that would complicate Paxlovid, and note their kidney function. All of that can happen at a routine visit or a refill call, while everyone’s healthy. That’s the missing middle layer, and it’s what we mean by appropriate medical preparation.

At Jase, we build that layer for the times primary care isn’t there, never as a replacement for it. Tamiflu and Paxlovid are both available as JaseCase add-ons. A licensed provider reviews each request and writes the prescription only when it’s appropriate, and either medication is for emergency use only, after first seeking the assistance of a qualified healthcare provider. If you’d rather not field these requests yourself, you can refer patients to us. We’ll keep publishing the frameworks behind where we draw these lines.

The bottom line

The 48-hour window belongs to healthy outpatients with flu. For a high-risk patient, treat as soon as possible, whatever the day count, and don’t wait on a test. COVID runs on its own clock: 5 days for Paxlovid, after you’ve checked the medication list and the kidneys. The benefit is modest for most patients and biggest for the ones most likely to land in the hospital, so start there. Then go enjoy the holidays…… and wash your hands.

To refer a patient, visit jase.com. A licensed provider reviews every request and writes a prescription only when it’s appropriate.

And a final note from Kristen Carpenter, our PA-C who reviewed this article, “during cold/flu season, the timing is so important to start the medication but there are no appointments in primary care schedules since everyone is sick! The chances of a same day or next day appointment are lower! So having high risk patients prepared ahead of time for these busy seasons can be super helpful!”


Sources

  1. FDA. Tamiflu (oseltamivir phosphate) prescribing information. Genentech; revised August 2019. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=ee3c9555-60f2-4f82-a760-11983c86e97b
  2. CDC. Influenza Antiviral Medications: Summary for Clinicians. Updated March 10, 2026. https://www.cdc.gov/flu/hcp/antivirals/summary-clinicians.html
  3. CDC. Influenza Antiviral Drug Resistance. Updated June 26, 2026. https://www.cdc.gov/flu/treatment/antiviralresistance.html
  4. Carrat F, Vergu E, Ferguson NM, et al. Time lines of infection and disease in human influenza: a review of volunteer challenge studies. Am J Epidemiol. 2008;167(7):775-785. doi:10.1093/aje/kwm375
  5. CDC. People at Increased Risk for Flu Complications. Updated September 11, 2024. https://www.cdc.gov/flu/highrisk/index.htm
  6. CDC. Rapid Influenza Diagnostic Tests. Updated June 22, 2026. https://www.cdc.gov/flu/hcp/testing-methods/clinician_guidance_ridt.html
  7. CDC. Underutilization of Flu Antivirals. March 20, 2026. https://www.cdc.gov/flu/whats-new/2025-2026-underutilization-of-flu-antivirals.html
  8. FDA. Paxlovid (nirmatrelvir tablets; ritonavir tablets) prescribing information. Pfizer; revised January 2025. https://www.accessdata.fda.gov/drugsatfda_docs/label/2025/217188s008lbl.pdf
  9. Gottlieb RL, Vaca CE, Paredes R, et al. Early remdesivir to prevent progression to severe Covid-19 in outpatients. N Engl J Med. 2022;386(4):305-315. doi:10.1056/NEJMoa2116846
  10. Zhou F, Yu T, Du R, et al. Clinical course and risk factors for mortality of adult inpatients with COVID-19 in Wuhan, China: a retrospective cohort study. Lancet. 2020;395(10229):1054-1062. doi:10.1016/S0140-6736(20)30566-3
  11. Shumaker AH, Bhimraj A, et al. 2025 Clinical Practice Guideline Update by the Infectious Diseases Society of America on the Treatment and Management of COVID-19: Antiviral Treatment for Mild to Moderate COVID-19 in Adults. Clin Infect Dis. doi:10.1093/cid/ciaf680. Posted October 14, 2025. Nirmatrelvir/ritonavir for high-risk adults: strong recommendation, moderate certainty of evidence. Molnupiravir when no other options exist: conditional recommendation, low certainty of evidence.
  12. FDA. Xofluza (baloxavir marboxil) prescribing information. Genentech; revised May 2025. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=e49e1a61-1b7c-4be5-ac84-af6240b511e7
  13. FDA. Veklury (remdesivir) prescribing information. Gilead; revised July 2026. https://www.accessdata.fda.gov/drugsatfda_docs/label/2026/214787s033lbl.pdf
  14. FDA. Fact Sheet for Healthcare Providers: Emergency Use Authorization for Lagevrio (molnupiravir) capsules. Revised June 2024. https://www.fda.gov/media/155054/download
  15. Hanula R, Bortolussi-Courval É, Mendel A, et al. Evaluation of oseltamivir used to prevent hospitalization in outpatients with influenza: a systematic review and meta-analysis. JAMA Intern Med. 2024;184(1):18-27. doi:10.1001/jamainternmed.2023.0699
  16. Jones JM, Manrique IM, Stone MS, et al. Estimates of SARS-CoV-2 seroprevalence and incidence of primary SARS-CoV-2 infections among blood donors, by COVID-19 vaccination status: United States, April 2021 to September 2022. MMWR Morb Mortal Wkly Rep. 2023;72(22):601-605. doi:10.15585/mmwr.mm7222a3


Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

For Clinicians | New World Screwworm in Humans

For Clinicians | New World Screwworm in Humans

For Clinicians | New World Screwworm in Humans: The Wound Check, the Larvae, and the Risk By Dr. Jamie Wilkey, PharmD, Director of Clinical EducationMedically reviewed and edited by Kristen Carpenter, PA-C New World screwworm is the latest health headline. This one...


read more

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

For Clinicians | Sinusitis: When Antibiotics Are Necessary

For Clinicians | Sinusitis: When Antibiotics Are Necessary

By Dr. Jamie Wilkey, PharmD, Director of Clinical Education
Medically reviewed and edited by Kristen Carpenter, PA-C

Adult sinusitis guidance changed in July 2025, when the AAO-HNSF published its first guideline update since 2015 [AAO-HNSF 2025]. Three changes affect us in the office or at the pharmacy counter: watchful waiting is now the starting point for every uncomplicated case (yep, even once you’ve called it bacterial), amoxicillin with or without clavulanate is first-line on a shorter course, and a patient who isn’t improving gets reassessed sooner. Today we’re covering all three, plus the clause in the watchful-waiting recommendation that assumes your patient can come back.

What changed in the 2025 sinusitis guideline?

For an adult with uncomplicated acute bacterial sinusitis, waiting used to be one of two options. Now it’s where we start [AAO-HNSF 2025]:

  • Watchful waiting became the default. Since 2015 we had the option either to offer watchful waiting or prescribe an antibiotic [AAO-HNSF 2015]. The 2025 version axes the “or prescribe”.  Offer watchful waiting without antibiotics, with assurance of follow-up. The fixed day count for when to start one is gone too. How long to wait now depends on when and how the diagnosis was made.
  • The course got shorter. Amoxicillin with or without clavulanate stays first-line, for 5 to 7 days in most adults instead of 5 to 10.
  • Treatment failure got redefined. It’s now judged against the antibiotic the patient is already taking. If it’s still bacterial, the solution is a different antibiotic.

You’re thinking, ok, but my patient is miserable and wants something today. They feel like it is a waste to leave our appointment without an Rx in-hand.  The guideline did address these folks: pain relievers, intranasal steroids, and saline irrigation are options for viral and bacterial sinusitis alike [AAO-HNSF 2025]. Those are also the three things a pharmacist can point to on the shelf when the patient asks for help with sinusitis.

When does sinusitis need an antibiotic?

Before writing that antibiotic script, check for one of two patterns. Neither changed in 2025 [AAO-HNSF 2025]:

  • Symptoms that persist without improvement for at least 10 days after the cold starts.
  • Symptoms that get better, then worse again within 10 days. (Double worsening)

Most of these patients never needed an antibiotic. Bacterial infection occurs in only 0.5 to 2 percent of episodes of acute rhinosinusitis, and acute bacterial rhinosinusitis may also be a self-limited disease³. It most commonly occurs as a complication of viral infection².

Mucus color isn’t on the list. Neither is how miserable the patient looks. Individual symptoms such as purulent nasal discharge or facial pain can’t accurately distinguish bacterial from viral sinusitis. Kristen Carpenter, PA-C, who reviewed this article, put it this way: “Fever and nasal discharge really don’t mean bacterial. Those symptoms can be viral too, so we don’t really give antibiotics just based on those symptoms. Everyone thinks they have a bacterial infection because of these things.” We covered why in our July article on bacterial vs. viral infection, so we won’t re-teach it here.

Where we struggle is applying the criteria. A Mayo Clinic cohort of adult sinusitis visits from early 2024 found that four of every five visits that didn’t meet any guideline criterion still ended with an antibiotic [Hannan 2026]. And the study counted generously: IDSA’s severe-onset pattern qualified too. The strongest predictor of an unneeded script was a patient on day 7, 8, or 9.

And I get it. Patients get so annoyed when we don’t give them that antibiotic right from the beginning. For them, day 8 of being sick feels like forever when you can’t breathe through your nose. Some of us (me, included) were trained on an older rule of thumb that anything past a week was probably bacterial. The 2025 guideline still draws the line at a full 10 days.

Some patients are worth starting earlier, and that comes down to their own history and health status. Kristen has a low threshold for starting antibiotics on the earlier side if the patient:

  • Is immunocompromised (diabetes, etc.)
  • Smokes
  • Has uncontrolled asthma (maybe)
  • Has a weird dental or nasal history
  • Has had a recent change in atmospheric pressure (e.g., deep sea diving)

“I’m sure there are others,” she says, “but again it would be based on some individual health status.”

Amoxicillin or Augmentin for a sinus infection? (And why not the Z-Pak)

Once a patient meets criteria and an antibiotic is the right call, then focus on amoxicillin or amoxicillin-clavulanate [AAO-HNSF 2025]. Either one is first-line. For a penicillin allergy, IDSA lists doxycycline as an alternative [IDSA 2012].

What we shouldn’t reach for is the Z-Pak. At the office or the pharmacy counter, it’s the antibiotic patients ask for by name, because it’s short, it’s easy, and “it worked last time”. (Or the last sinus infection was viral and got better on its own, Z-Pak or no Z-Pak.) IDSA recommends against macrolides for empiric sinusitis therapy because resistance rates are too high. They’re not alone. TMP-SMX is on the same list for the same reason [IDSA 2012]. Fluoroquinolones carry their own limit: since 2016, FDA has said to reserve them for acute sinusitis when no other option exists [FDA 2016].

A patient who isn’t better, or is worse, after 3 to 5 days on an appropriate antibiotic gets reassessed: confirm it’s still bacterial sinusitis, look for another cause, and check for complications [AAO-HNSF 2025]. If it’s still ABRS, switch the antibiotic. That’s the ideal follow up visit.

When the clinic isn’t reachable

Watchful waiting comes with a condition: assurance of follow-up [AAO-HNSF 2025]. The recheck is the safety net. It catches the patient who crosses into a bacterial pattern and the rare one heading toward a complication.

Most of us read past that clause, because most of our patients can come back. Some can’t, and some can’t get in the first time either. The patient on an international trip, the family at a remote cabin, the town where a storm closes the clinic.

Here’s what makes sinusitis different from strep: the diagnosis rests on the history and the calendar. There’s no rapid test to run, and an uncomplicated case doesn’t need imaging [AAO-HNSF 2025]. So no clinic doesn’t have to mean no clinician. A phone or telehealth visit can apply the same two patterns, at the first visit or the second.

Whichever visit is missing, the counseling has to do its job ahead of time, at the office or the pharmacy counter. In plain words:

  • The two patterns: no improvement by day 10, or better and then worse. Either one means it’s time to reach a clinician, by phone or telehealth if that’s what they have.
  • The signs that mean go now, wherever they are: swelling around the eye, changes in vision, a severe headache, confusion, a stiff neck, or a high fever that won’t come down [IDSA 2012].

A patient who already has a prescribed antibiotic at home doesn’t get a different standard. It’s for emergency use only, after first seeking help from a qualified healthcare provider, and the two patterns still decide whether it’s needed.

None of this is a reason to start sooner. Distance from a clinic isn’t on Kristen’s list, and the 10-day line holds wherever the patient is.

Holding our own guidance to the update

We’re a family team of medical doctors, PAs, and pharmacists, and we hold our own guidance to the same update. The Jase amoxicillin-clavulanate card reads 5 to 7 days for sinusitis, and it did before the 2025 guideline made that the standard.

The bigger work is the part this guideline hands to a visit the patient may not be able to make. Right now care runs all or none: the patient gets in, or they’re on their own with an internet search bar and a leftover Z-Pak. Appropriate medical preparation is the step between. It’s clinical work done ahead of time. For sinusitis, that work is mostly teaching patients to count the days, and most of them will be better before they reach 10[IDSA 2012]. It’s in no way a replacement for primary care. We’re here for the times when primary care isn’t there, and we’ll keep publishing how we draw these lines so you can check our work.

The bottom line

The 2025 update kept the diagnosis and changed the default: wait first, with follow-up, and keep the course short when an antibiotic is needed. For most patients, the hardest stretch is days 7 through 9, when they’re tired of being sick and we’re tempted to start antibiotics too early.


Sources

  1. Payne SC, McKenna M, Buckley J, et al. Clinical Practice Guideline: Adult Sinusitis Update. Otolaryngol Head Neck Surg. 2025;173(Suppl 1):S1-S56. https://doi.org/10.1002/ohn.1344
  2. Rosenfeld RM, Piccirillo JF, Chandrasekhar SS, et al. Clinical practice guideline (update): adult sinusitis. Otolaryngol Head Neck Surg. 2015;152(2 Suppl):S1-S39. https://doi.org/10.1177/0194599815572097
  3. Arensman Hannan K, Ilges D, Le KT, Cole K, Stevens RW, Jensen K. Ambulatory antibiotic prescribing for acute sinusitis: a multicenter, retrospective cohort study evaluating appropriateness. Antimicrob Steward Healthc Epidemiol. 2026;6(1):e193. https://doi.org/10.1017/ash.2026.10743
  4. Chow AW, Benninger MS, Brook I, et al. IDSA clinical practice guideline for acute bacterial rhinosinusitis in children and adults. Clin Infect Dis. 2012;54(8):e72-e112. https://doi.org/10.1093/cid/cis370
  5. U.S. Food and Drug Administration. CIPRO (ciprofloxacin hydrochloride) prescribing information, section 1.12, Acute Sinusitis. Revised July 2016. https://www.accessdata.fda.gov/drugsatfda_docs/label/2016/019537s086lbl.pdf


Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

For Clinicians | New World Screwworm in Humans

For Clinicians | New World Screwworm in Humans

For Clinicians | New World Screwworm in Humans: The Wound Check, the Larvae, and the Risk By Dr. Jamie Wilkey, PharmD, Director of Clinical EducationMedically reviewed and edited by Kristen Carpenter, PA-C New World screwworm is the latest health headline. This one...

read more

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

For Clinicians | New World Screwworm in Humans

For Clinicians | New World Screwworm in Humans: The Wound Check, the Larvae, and the Risk

By Dr. Jamie Wilkey, PharmD, Director of Clinical Education
Medically reviewed and edited by Kristen Carpenter, PA-C

New World screwworm is the latest health headline. This one came from an elk in Texas. On October 21, USDA confirmed the parasite in an elk on a Pecos County game ranch, the first US wildlife case of this outbreak¹. We don’t ride the hype wagon that turns every news story into a healthcare emergency, and CDC still rates the risk to the US public as very low². But when our clinical team reviewed the cases, we were kind of struck by who this has actually reached. The people who’ve gotten it look a lot like the patients we serve at Jase.

Fair warning: this article isn’t for the squeamish. We’re talking about maggots in wounds. You’re clinicians, so we know you can handle it.

Today we’re covering who’s actually at risk for screwworms in the US, what an infested wound looks like, what to do with the larvae, and what antibiotics can and can’t do. 

Can people in the US get New World screwworm?

Yes, but only in one very specific and super gross way. A female fly lays her eggs on an open wound or a mucous membrane, and the larvae hatch and burrow in to feed on living flesh³. Most maggots you’ve seen in a wound stay up on the surface. These go deep deep deep, which is the problem.

The fly is the only route. Screwworm doesn’t pass from person to person, and nobody catches it from an infested animal⁴. So the clinical question is narrow: does this patient have an open wound somewhere the flies are? Right now that means parts of Texas and New Mexico, plus travel to Mexico or Central America. And CDC means any open wound, even a scratch, an insect bite, or a recent surgical site³.

That elk that is all over the headlines these days is why we’re writing now. Wildlife is harder to track and control than cattle, and CDC listed wildlife detection as one of the developments that would change its risk assessment⁴. Whether cold weather holds the fly back this winter is still an open question.

Screwworm finds older patients with chronic wounds

Clinicians, you won’t be surprised that most of these infestations are on the legs and feet. If something is eating a patient’s foot and they don’t know it, our brains go straight to the likely reasons. They probably can’t feel it because of diabetic neuropathy, or they have a hard time reaching or seeing that part of their body. A heel or the back of a calf is easy to miss when bending over is hard, and a diabetic foot ulcer or a venous stasis ulcer can stay open for months. That gives the fly both things it needs: an open wound and time.

The people actually at risk look exactly like that. In Mexico’s 202 confirmed human cases between April 2025 and March 2026, the average patient was 61, most had at least one chronic condition (diabetes was the most common), and more than half of the infestations were on the legs or feet⁵. CDC describes the same group: older adults and people with limited mobility, whose infestations can go unnoticed until treatment is late⁴. The deaths in the Mexico series happened in even older patients, and the authors attributed only one of the six directly to the larvae⁵.

These patients aren’t necessarily frail, either. Plenty of them still work cattle, hunt every fall, or spend the winter in South Texas, and they just don’t notice a wound on a foot they can’t feel. In the office, that means taking the sock off and looking at the feet of your patients with diabetes who live in or travel to these areas. At the pharmacy counter, it means asking a few questions when someone buys dressings for a foot or leg wound that won’t heal and has started to smell.

What does an infested wound look like, and what do you do with the larvae?

You’ll probably smell it before you see it. Texas health officials describe a very painful, foul-smelling wound with visible larvae, sometimes with an egg mass in or around the wound or a body opening, and often more tissue damage underneath than the surface suggests⁶. When a wound like that shows up in a patient who lives in, works in, or recently traveled through an area with the fly, screwworm belongs on your list.

The protocol from there is short:

  • Remove every larva. They burrow deep, so the ones you can see are not all of them, and getting the rest out may take surgical debridement⁶.
  • Collect larvae from different depths of the wound and drop them into a leak-proof container with enough 70% ethanol to cover them⁶.
  • Never throw live larvae in the trash or on the ground. Kill them in the alcohol, then dispose of the sealed container as medical waste, because a live larva in the dumpster is how the fly gets a new foothold⁶.
  • Recheck the wound in 24 to 48 hours to make sure nothing in there is still alive⁶.
  • Call your local or state health department right away. Texas treats a suspected case as immediately reportable, and the health department will help get the larvae identified⁶. Reporting rules vary by state, so check yours.

For patients with open wounds, your front desk or MA can add one intake question: have you been in Texas, New Mexico, Mexico, or Central America recently? At the pharmacy counter, send the patient to be seen that same day and tell them not to pick the maggots out at home. CDC says patients shouldn’t try, since getting every larva out can take a clinician and sometimes surgery².

What can antibiotics do for screwworm?

Antibiotics do less here than patients will hope. Larvae aren’t bacteria, so an antibiotic does nothing to the infestation itself. What it can treat is a secondary bacterial infection in a wound that’s been chewed open, and Texas health officials remind clinicians that it may need antibiotic therapy⁶. That call follows the same logic as any other infected wound, starting with whether you’re looking at a purulent pocket or a spreading cellulitis.

Nothing treats the larvae themselves. CDC says no licensed human vaccine or medication currently prevents or treats screwworm in people⁴. The treatment with evidence behind it is the protocol above: get every larva out and keep caring for the wound.

Your patients may have read otherwise, because there are plenty of guesses online that whatever works on cattle will work on people. Don’t follow treatment advice that comes only from social media or forums. Stick with what the medical literature has shown to be safe and effective in humans. For screwworm, that’s still a clinician with nerves of steel and a pair of tweezers.

The bottom line: the wound nobody’s checking

Right now, care for a wound like this is all or nothing. Either a clinician sees it, or the patient is alone with a sore on a foot they can’t feel. The step in between is counseling. Tell your patients in fly areas to wash open wounds with soap and running water, keep every wound covered, even a tiny scratch or a bug bite², check their feet and legs every day, and get seen the same day if they ever see or feel maggots. 

For patients who spend long days outside, like hunters, ranchers, and anyone working cattle, add the fly side of it. CDC recommends loose-fitting long sleeves and pants, a hat, and socks, clothing and gear treated with a 0.5% permethrin product (the kind made for fabric, not skin), an EPA-registered insect repellent, and sleeping indoors or somewhere screened². Fall hunting season is a good time to bring it up.

That’s appropriate medical preparation, with no prescription anywhere in it. It complements the primary care you’re already giving, and it covers the stretch between visits when nobody else is looking at that foot.

The health risk to the US public is very low, and the patients who are actually at risk are a narrow group you already know. The protocol is short, and no drug treats the larvae. We’ll keep publishing how we think through headlines like this one, so you have a clear clinical picture to point to when your patients bring them in or pepper you with questions from what they’re reading.


Sources

  1. USDA Animal and Plant Health Inspection Service. USDA Confirms First Detection of New World Screwworm in U.S. Wildlife. October 21, 2026. https://www.aphis.usda.gov/news/agency-announcements/usda-confirms-first-detection-new-world-screwworm-us-wildlife
  2. Centers for Disease Control and Prevention. New World Screwworm Outbreak. Updated October 22, 2026. https://www.cdc.gov/new-world-screwworm/situation-summary/index.html
  3. Centers for Disease Control and Prevention. Clinical Overview of New World Screwworm. Updated February 24, 2026. https://www.cdc.gov/new-world-screwworm/hcp/clinical-overview/index.html
  4. Centers for Disease Control and Prevention. Risk to People in the United States from the New World Screwworm Outbreak (2026). Assessment as of October 7, 2026. https://www.cdc.gov/cfa-qualitative-assessments/php/data-research/risk-to-people-in-the-united-states-from-the-new-world-screwworm-outbreak-2026.html
  5. Delgado-Cuellar O, Mosso-González C, Castañeda-Gómez J, et al. Human Myiasis Resulting from Reemergence of Cochliomyia hominivorax Screwworm, Mexico, 2025-2026. Emerg Infect Dis. 2026;32(10):1581-1589. https://wwwnc.cdc.gov/eid/article/32/10/26-1235_article
  6. Texas Department of State Health Services. New World Screwworm Information for Healthcare Providers. Accessed October 26, 2026. https://www.dshs.texas.gov/notifiable-conditions/zoonosis-control/zoonosis-control-diseases-and-conditions/new-world-screwworm/new-world-screwworm-information-healthcare-providers


Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

For Clinicians | New World Screwworm in Humans

For Clinicians | New World Screwworm in Humans

For Clinicians | New World Screwworm in Humans: The Wound Check, the Larvae, and the Risk By Dr. Jamie Wilkey, PharmD, Director of Clinical EducationMedically reviewed and edited by Kristen Carpenter, PA-C New World screwworm is the latest health headline. This one...

read more

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

For Clinicians | Trick or Treatment? 5 Halloween Health Facts From a Pharmacist

For Clinicians | Trick or Treatment? 5 Halloween Health Facts From a Pharmacist

By Dr. Jamie Wilkey, PharmD, Director of Clinical Education
Medically reviewed and edited by Kristen Carpenter, PA-C

Halloween is this week, so we’re taking a break from our in-depth appropriate medical preparation articles. I just love Halloween (cutesy Halloween, at least), and as a pharmacist I love tying medications into every part of our lives. This time of year they turn up in some strange places, because unusual candy is out and people are doing things they don’t normally do.

Here are the 5 we will cover today: black licorice, costume contacts, a nightly allergy pill, a mushroom from the yard, and a bat in the bedroom. Not all of them are medications….one is a bat.  Each one will help you keep your patients safe this spooky season.

1-Is black licorice bad for you?

In big enough amounts, yes. Real licorice root contains glycyrrhizin (love that name!), which tricks the kidneys into acting like they’re swimming in aldosterone. They hang onto salt, dump potassium, and blood pressure climbs.¹

The New England Journal of Medicine published the cautionary tale in 2020. A 54-year-old construction worker switched from fruit-flavored soft candy to the licorice kind, and ate a large bag or two a day. Three weeks later he went into cardiac arrest in a fast-food restaurant. His team gave him 420 mmol of potassium in 12 hours (21 of those big 20 mEq tablets, for my pharmacist friends), and he didn’t survive.¹

For most people, a handful at a party is fine. A daily habit isn’t, and patients with high blood pressure or heart or kidney disease can get into trouble on even small amounts.² A diuretic, already flushing out potassium on its own, stacks dangerously on top.¹ (We covered the interactions that push potassium the other way in Drug Interactions in a Disaster.)

Not every bag counts, either. Many US “licorice” products are flavored with anise oil and contain no licorice at all, while licorice root itself shows up in supplements and herbal blends.²  So when a potassium comes back low for no clear reason, ask about candy and supplements.

2-Are costume contacts dangerous?

They can be. A decorative contact lens is a medical device, even if it corrects nothing and just gives you those freaky alien eyes. Selling one without a prescription is illegal, and FDA lists Halloween stores, flea markets, beach shops, and video stores (if you can still find one) as places to never buy them.³

The problem is fit. Decorative lenses aren’t one size fits all, and a lens that doesn’t fit can scratch the cornea, which opens the door for bacteria. FDA warns these infections can cause blindness, sometimes within as little as 24 hours.³

Any red, painful eye after a costume party needs to get seen right away.³ At the pharmacy counter you’ll see a patient asking for redness drops, but the better answer is a same-day exam. (Our pink eye article covers why any lens wearer with a red eye skips the wait.)

3-Can medications cause nightmares?

They sure can, and two common ones put it right on the label. Montelukast, the nightly allergy and asthma pill, got an FDA boxed warning in 2020 for mental health side effects, and “bad or vivid dreams” made the list. FDA’s counseling is that a patient who notices these changes is to stop the medication and call a health care professional right away. FDA also asks prescribers to save montelukast for allergy patients who don’t respond to, or can’t tolerate, other allergy medicines.⁴

Beta-blockers are the other one: propranolol’s label lists vivid dreams, and metoprolol’s lists nightmares.⁵,⁶ It’s not clear why these cause bad dreams, though. One theory is melatonin. The brain makes it at night on a beta-receptor signal, and in one small study, a single dose of propranolol’s active form cut nighttime melatonin to about a fifth of normal.⁷

Beta-blockers get the opposite advice from montelukast, though. Both labels warn that stopping suddenly can worsen angina, so the patient is to keep taking it and call the prescriber for next steps.⁵,⁶

So when a patient mentions new nightmares….check the medication list before blaming the horror movie marathon.

4-Why are death cap mushrooms so sneaky?

Because they play dead, like any good horror movie villain. The mushrooms that only upset the stomach make people sick within an hour or two. Death caps wait, then hit with vomiting and diarrhea, often 6 or more hours after the meal.⁸,⁹ With fluids, the patient can even start to feel better while their liver tests still look normal, which is how some get sent home with a stomach bug diagnosis.⁸

Meanwhile, the toxin has shut down the liver cells’ ability to make new proteins. Liver injury shows up on labs within a day or so, and liver failure can follow over the next several days.⁸,⁹

Death caps grow along the West Coast, including in city parks, and peak season runs October through April (happy Halloween). Northern California just had the largest outbreak in its history: 39 suspected poisonings and 4 deaths. Many of those patients had picked a mushroom that looked like a safe one they’d foraged in another country.⁹

So when vomiting and diarrhea start hours after a meal, ask about wild mushrooms. If the answer is yes, call Poison Control at 1-800-222-1222 right away, even if the patient feels better. (A pharmacist might answer. We really are everywhere.)¹⁰

5-Does a bat in the house mean rabies shots?

Sometimes. Bats caused 35 of the 42 rabies cases caught in the US since 2000.¹¹ A bat bite can be so small nobody notices it, so people don’t seek shots before symptoms start, and by then it’s too late.¹¹

That’s why any direct contact with a bat gets a rabies risk assessment. If the bat can’t be tested, waking up with one in the room calls for shots when the sleeper could have missed a bite: a deep sleeper, a young child, someone who’d been drinking, or someone on a sedating medication (pharmacists, that one’s ours).¹¹,¹²

One of the two Americans who died of bat rabies in 2024 had found a bat in her Minnesota home. She saw clinicians several times after her symptoms started, and the bat never made it into her chart.¹¹ So ask! (Our bite and scratch article has the full rabies refresher.)

The bottom line

Halloween hazards like to hide in plain sight. Here are the 5 to keep in your clinical back pocket this week:

  • Low potassium for no clear reason? Ask about licorice.
  • Red, painful eye after a costume party? Same-day eye exam.
  • New nightmares? Check the medication list.
  • Vomiting hours after a meal? Ask about wild mushrooms, and call Poison Control at 1-800-222-1222.
  • A bat in the house? Rabies risk assessment, especially for anyone who was asleep.

We’re here for the times primary care isn’t there, and in no way a replacement for it. This list is a good example: every one of these ends with a call to a clinician, an eye doctor, or Poison Control. Happy Halloween from all of us at Jase! 🎃


Sources

  1. Edelman ER, Butala NM, Avery LL, Lundquist AL, Dighe AS. Case 30-2020: a 54-year-old man with sudden cardiac arrest. N Engl J Med. 2020;383(13):1263-1275. https://pmc.ncbi.nlm.nih.gov/articles/PMC8568064/
  2. National Center for Complementary and Integrative Health. Licorice Root. Updated April 2025. https://www.nccih.nih.gov/health/licorice-root
  3. U.S. Food and Drug Administration. Colored and Decorative Contact Lenses: A Prescription Is a Must. Content current as of October 24, 2022. https://www.fda.gov/consumers/consumer-updates/colored-and-decorative-contact-lenses-prescription-must
  4. U.S. Food and Drug Administration. FDA requires Boxed Warning about serious mental health side effects for asthma and allergy drug montelukast (Singulair); advises restricting use for allergic rhinitis. Drug Safety Communication. March 4, 2020. https://www.fda.gov/drugs/drug-safety-communications/fda-requires-boxed-warning-about-serious-mental-health-side-effects-asthma-and-allergy-drug
  5. Inderal LA (propranolol hydrochloride) extended-release capsules. Prescribing information. ANI Pharmaceuticals; 2026. DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=35d28979-36b1-4630-b85e-a44e0a443734
  6. Metoprolol tartrate tablets. Prescribing information. Mylan Pharmaceuticals; 2024. DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=809c6386-0039-42ff-a03e-e42733e229b8
  7. Stoschitzky K, Sakotnik A, Lercher P, et al. Influence of beta-blockers on melatonin release. Eur J Clin Pharmacol. 1999;55(2):111-115. https://pubmed.ncbi.nlm.nih.gov/10335905/
  8. Santi L, Maggioli C, Mastroroberto M, Tufoni M, Napoli L, Caraceni P. Acute liver failure caused by Amanita phalloides poisoning. Int J Hepatol. 2012;2012:487480. https://pmc.ncbi.nlm.nih.gov/articles/PMC3395149/
  9. Brandecker KJ, Hayman C, LeSaint KT, et al. Amanita species mushroom poisonings, Northern California, November 2025-March 2026. MMWR Morb Mortal Wkly Rep. 2026;75(20):258-263. https://www.cdc.gov/mmwr/volumes/75/wr/mm7520a2.htm
  10. America’s Poison Centers. Get Poison Help. https://poisoncenters.org/page-1075452
  11. Ireland M, Fritz CL, Holzbauer S, et al. Human rabies deaths, Minnesota and California, 2024. MMWR Morb Mortal Wkly Rep. 2026;75(2):28-31. https://www.cdc.gov/mmwr/volumes/75/wr/mm7502a4.htm
  12. Manning SE, Rupprecht CE, Fishbein D, et al. Human rabies prevention, United States, 2008: recommendations of the Advisory Committee on Immunization Practices. MMWR Recomm Rep. 2008;57(RR-3):1-28. https://www.cdc.gov/mmwr/preview/mmwrhtml/rr57e507a1.htm
  13.  


Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

For Clinicians | New World Screwworm in Humans

For Clinicians | New World Screwworm in Humans

For Clinicians | New World Screwworm in Humans: The Wound Check, the Larvae, and the Risk By Dr. Jamie Wilkey, PharmD, Director of Clinical EducationMedically reviewed and edited by Kristen Carpenter, PA-C New World screwworm is the latest health headline. This one...

read more

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

For Clinicians | After the Tick Bite: The Tick Decides the Risk

For Clinicians | After the Tick Bite: The Tick Decides the Risk

By Dr. Jamie Wilkey, PharmD, Director of Clinical Education
Medically reviewed and edited by Aaron Asay, PA-C, DMSc, FIBODM, FAWM

Ticks have been on my radar my whole life. I grew up in Wyoming, where there are very few trees around (and those that exist are either aspens or pine trees), so needless to say,  a treehouse in my yard wasn’t an option. Instead, I had a fort out on the hill in my backyard in the sagebrush: a hole in the ground with planks over the top. Even then playing in the sagebrush all day I kept an eye out for ticks. I’ve never had a tick bite (knock on wood), which feels kind of amazing, because our family cabin has ticks everywhere and I still hike in the Utah mountains most mornings.

This article is for the clinicians helping outdoor people like me who just can’t stay away from the outdoors. We’ll cover basic tick identification, what a Lyme rash really looks like, when to test and treat, and the tick bite that ends in a red-meat allergy instead of an infection.

Which tick was it?

Whether it comes up in the office or at the pharmacy counter, start with two questions: what did the tick look like, and where was the patient when it bit?

  • Blacklegged tick (deer tick): carries Lyme. Common in the Northeast, mid-Atlantic, and upper Midwest, with a western cousin along the Pacific coast¹. The nymph is about the size of a poppy seed, so most patients never notice the bite².
  • Lone star tick: the adult female has one white spot on her back. Common in the South, East, and Midwest.³ It doesn’t carry Lyme, but it’s the main cause of alpha-gal syndrome¹,⁴.
  • Rocky Mountain wood tick: the common tick in the Rocky Mountain states³. It doesn’t carry Lyme¹(So my sagebrush fort was safe, at least from Lyme, whew!).However, it can transmit other serious infections, including Rocky Mountain spotted fever, Colorado tick fever, and tularemia.

[IMAGES: row of three, PHIL 28383, PHIL 8676, PHIL 10865]
Blacklegged tick, adult female (left) and nymph (right). Photo: CDC/Lauren Bishop.
Lone star tick, adult female. Photo: CDC/James Gathany.
Rocky Mountain wood tick. Photo: CDC/James Gathany.
Source for all: CDC Public Health Image Library.

If the patient can’t name the tick, their geographic exposure can help narrow the possibilities, although tick species and their ranges may overlap.

What does a Lyme rash actually look like?

Most of us learned the Lyme rash as a bull’s-eye presentation. In the US, most erythema migrans (EM) rashes are evenly red, or reddest in the center, with no rings at all²,⁵. A typical EM is diagnosed on sight ⁶.

The rash is the bacteria spreading outward through the skin from the bite, which is why it grows². What to look for:

  • A red patch at the bite site that keeps expanding over several days, sometimes to 12 inches or more
  • Shows up 3 to 30 days after the bite, about a week on average
  • Warm to the touch, but rarely itchy or painful⁷.

A small red bump right after the bite that looks like a mosquito bite and fades in a day or two is a bite reaction, not Lyme⁷.

Should you test a typical EM?

No. For a typical EM rash, skip the blood test and treat ⁶.

The rash shows up before the immune system has made enough antibodies to measure. If you were to test 10 patients with a fresh rash, 6 to 8 of them would come back negative⁸. Antibody testing has limited sensitivity during early localized Lyme disease, so a negative result does not exclude infection. When a patient has a typical erythema migrans rash and credible exposure, treatment should not wait for laboratory confirmation.

Two more tests to skip after a tick bite ⁶:

  • Testing the tick itself for Lyme bacteria. A positive or negative tick doesn’t predict whether the patient gets infected. (Identifying the species is still useful.)
  • Testing a patient who has no symptoms.

Save the blood test for a rash that doesn’t look typical. If that first draw is negative, IDSA suggests a second sample taken later to catch the antibodies as they rise⁶.

[IMAGES: side by side, PHIL 9875 and PHIL 14474]
The Lyme rash everyone pictures (left) and a more typical one (right). Photos: CDC/James Gathany (left), CDC (right). Source: CDC Public Health Image Library.

How long do you treat a Lyme rash?

Treat a typical EM with 10 days of doxycycline, or 14 days of amoxicillin or cefuroxime ⁶. Longer courses aren’t recommended. Azithromycin for 7 days is the backup for patients who can’t take doxycycline or a beta-lactam ⁶. Doxycycline isn’t off-limits for young kids anymore, either. IDSA notes a growing consensus that courses of up to 14 days are safe in young children (plus, newer research casts doubt on that old tooth-staining worry ⁶).

Doxycycline counseling is the same as always: take it with a full glass of water and wear sunscreen⁹,¹⁰. And finish the course as written, even after the rash fades.

What about a single dose of doxycycline right after the bite? It’s an option for a high-risk bite within 72 hours of removing the tick, and the criteria are strict. We walked through who qualifies in our July article on doxycycline uses.

What is alpha-gal syndrome?

Alpha-gal is a sugar found in most mammals, but not in people, birds, or fish. A tick bite, most often from a lone star tick, can sensitize the immune system to it⁴,¹¹. Lone star ticks aren’t the only suspect, though: Maine has reported a case after a blacklegged tick bite¹². It’s an allergy, not an infection, so antibiotics don’t treat or prevent it. The doxycycline from the last section does nothing here.

Consider alpha-gal when a patient has hives, stomach symptoms, or anaphylaxis 2 to 6 hours after eating red meat or dairy¹¹,¹³. The delay is a big part of why it gets missed. So is unfamiliarity: in a CDC survey of 1,500 clinicians, about 4 in 10 had never heard of it ¹³. 

The workup is an alpha-gal IgE blood test, read alongside the history, because a positive result alone doesn’t make the diagnosis¹⁴. From there, it’s avoidance, an allergist, and an epinephrine plan for anyone with systemic reactions¹⁵,¹⁶.

Pharmacists, something good for you to keep in mind as well: some medications made with gelatin can trigger a reaction¹.Not every patient reacts to dairy, gelatin, or mammalian-derived medications. Avoidance recommendations should be individualized according to reaction history and allergy evaluation.

Where the gap is after a tick bite


Most tick bites don’t happen conveniently next to a clinic during office hours. They happen on a trail, at a cabin, or on a hunting trip. And right now, care after a bite is all or none: the patient reaches a clinician while it still matters, or they’re left with a rash, an internet search, and a bull’s-eye picture that doesn’t match what’s on their leg.

That missing middle is the work we do. We call it appropriate medical preparation: teaching patients what to watch for before they head out, with a clinician-built plan for when care isn’t reachable. It’s in no way a replacement for primary care. It’s for the times when primary care isn’t there.

Tick bites are part of that work. Doxycycline is in every JaseCase, and its card covers two tick situations: the single preventive dose, only when every criterion on the card is met, and the 10-day course for an EM rash. Both are for emergency use only, after the patient has first tried to reach a qualified healthcare provider.

If you’d rather not prescribe in this space, you can refer patients to us. A licensed provider reviews every request and writes every prescription. And we’ll keep publishing how we draw these lines, the same way we did here.

The bottom line
Ask which tick made the bite and where it happened. Diagnose a typical Lyme rash on sight, and don’t wait for a bull’s-eye or a positive test to treat it. Skip testing the tick, and skip testing the patient with no symptoms. Think alpha-gal when a lone star bite is followed by delayed reactions to red meat, and remember antibiotics won’t touch it.

People who love the outdoors aren’t going to stay inside, and I’m one of them. To refer a patient, visit Jase.com, where a licensed provider reviews every request.


Sources

  1. CDC. How Lyme disease spreads. Updated September 24, 2024. https://www.cdc.gov/lyme/causes/index.html
  2. Nadelman RB. Erythema migrans. Infect Dis Clin North Am. 2015;29(2):211-239. https://doi.org/10.1016/j.idc.2015.02.001
  3. CDC. Where ticks live. Updated July 30, 2025. https://www.cdc.gov/ticks/about/where-ticks-live.html
  4. CDC. About alpha-gal syndrome. Updated January 5, 2026. https://www.cdc.gov/alpha-gal-syndrome/about/index.html
  5. Smith RP, Schoen RT, Rahn DW, et al. Clinical characteristics and treatment outcome of early Lyme disease in patients with microbiologically confirmed erythema migrans. Ann Intern Med. 2002;136(6):421-428. https://doi.org/10.7326/0003-4819-136-6-200203190-00005
  6. Lantos PM, Rumbaugh J, Bockenstedt LK, et al. Clinical practice guidelines by the Infectious Diseases Society of America (IDSA), American Academy of Neurology (AAN), and American College of Rheumatology (ACR): 2020 guidelines for the prevention, diagnosis, and treatment of Lyme disease. Clin Infect Dis. 2021;72(1):e1-e48. https://doi.org/10.1093/cid/ciaa1215
  7. CDC. Signs and symptoms of untreated Lyme disease. Updated May 15, 2024. https://www.cdc.gov/lyme/signs-symptoms/index.html
  8. Horn EJ, Menefee B, Schotthoefer AM, et al. Evaluation of standard and modified two-tiered testing algorithms using well-characterized early Lyme disease samples. J Clin Microbiol. 2026;64(5):e0118725. https://doi.org/10.1128/jcm.01187-25
  9. MedlinePlus. Doxycycline. Revised May 15, 2026. https://medlineplus.gov/druginfo/meds/a682063.html
  10. Medsafe (New Zealand Medicines and Medical Devices Safety Authority). Oesophagitis with doxycycline and others. Prescriber Update. 2003;24(2):30. https://www.medsafe.govt.nz/profs/puarticles/doxoesoph.htm
  11. CDC. Alpha-gal syndrome for healthcare providers. April 12, 2022. https://stacks.cdc.gov/view/cdc/131343
  12. Saunders EF, Sohail H, Myles DJ, et al. Alpha-gal syndrome after Ixodes scapularis tick bite and statewide surveillance, Maine, USA, 2014–2023. Emerg Infect Dis. 2025;31(4). https://doi.org/10.3201/eid3104.241265
  13. Carpenter A, Drexler NA, McCormick DW, et al. Health care provider knowledge regarding alpha-gal syndrome: United States, March–May 2022. MMWR Morb Mortal Wkly Rep. 2023;72(30):809-814. https://doi.org/10.15585/mmwr.mm7230a1
  14. CDC. Clinical diagnosis and testing (alpha-gal syndrome). Updated January 5, 2026. https://www.cdc.gov/alpha-gal-syndrome/hcp/diagnosis-testing/index.html
  15. Nationwide Children’s Hospital. Alpha-gal syndrome (AGS): clinical FAQ for health care professionals. October 2025. https://pediatricsnationwide.org/wp-content/uploads/2026/04/W2043400-RUSH_Alpha-Gal-Syndrome_Clinical-FAQ-for-Providers_FINAL.pdf
  16. CDC. Managing alpha-gal syndrome. Updated January 5, 2026. https://www.cdc.gov/alpha-gal-syndrome/managing/index.html


Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

For Clinicians | New World Screwworm in Humans

For Clinicians | New World Screwworm in Humans

For Clinicians | New World Screwworm in Humans: The Wound Check, the Larvae, and the Risk By Dr. Jamie Wilkey, PharmD, Director of Clinical EducationMedically reviewed and edited by Kristen Carpenter, PA-C New World screwworm is the latest health headline. This one...

read more

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!

For Clinicians | Diabetes Sick-Day Rules in a Disaster

For Clinicians | Diabetes Sick-Day Rules in a Disaster

By Dr. Jamie Wilkey, PharmD, Director of Clinical Education
Medically reviewed and edited by Kristen Carpenter, PA-C

Diabetes is already hard to manage. Sick days just make everything worse. And a sick day in a disaster, when healthcare isn’t readily available, compounds the hardship. Put the three together and it’s 1 + 1 + 1. For someone’s health, that doesn’t equal 3.
It equals 20. 

And the disaster itself counts as its own 1, even before anyone gets sick. In a Puerto Rico cohort of adults who didn’t have diabetes, new cases showed up at about twice the pre-storm rate in the years spanning Hurricanes Irma and Maria¹.

Disaster guidance for diabetes focuses mostly on a supply list (have plenty of insulin on hand and stored properly!). Sick days barely come up as a management topic. That’s a big gap when about 40 million Americans have diabetes, 2.1 million of them type 1². Their care really does change in a disaster, whether that’s a hurricane or a week when they can’t reach their clinic or pharmacy. We have to address that.

Today we’ll cover:

  • what a diabetes sick day is
  • which medications pause (+ why insulin never pauses)
  • how ketones work, and why a normal meter reading can fool you
  • what to look for in the OTC aisle
  • how to write the plan before storm season

What is a diabetes sick day?

I’m including this here to start because even as a pharmacist I have to admit (abashedly) that I didn’t know much about this topic. 99% of my diabetic counseling focused on medications in general and blood sugar testing.

A diabetes sick day is any illness that changes how the body handles glucose, fluids, or medications: a stomach bug, a fever, a UTI, or a really rough flu. The hormones the body releases to fight illness push blood sugar up ³…. even in a patient who has barely eaten all day. Vomiting, diarrhea, and fever drain fluid, and the kidneys feel it first. That’s where the medication problems start.  Several of the drugs these patients take every day either depend on the kidneys or make dehydration worse. And when insulin runs short, the body breaks down fat for fuel and starts making ketones.

Sick-day rules exist to catch all of that early: check glucose more often, keep fluids going, check ketones, and call when the numbers cross a line. The ADA’s patient guide ends with “call your doctor or go to the ER” ⁴. Yep, every version ends there, which doesn’t really work.

A disaster amplifies everything. Bad water brings on vomiting and diarrhea. Heat causes dehydration. Meals get skipped. Smoke or mold sets off someone’s asthma, and the steroid burst that settles their breathing raises glucose on its own (we covered that in our asthma and COPD flare article). The clinic is often closed, flooded, or not picking up, so care isn’t available.

Which medications pause on a diabetes sick day?

Canadian clinicians teach the pause list as SADMANS, a Diabetes Canada mnemonic ⁵, and UK sick-day cards carry close versions of it⁶,⁷. Each class gets much riskier when a patient is dehydrated or not eating, and most of the list comes back to the kidney’s filter, which needs pressure to work. Picture a garden hose with me for the kidneys. Blood volume is the water from the spigot. When the water runs low, the kidney keeps the spray going two ways: it holds the inflow open, and it puts a thumb over the end of the hose so pressure builds inside, where the filtering happens. That’ll help you picture how the SADMANS medications affect the patient’s kidney.

  • S: sulfonylureas like glipizide and glimepiride keep pushing insulin out when the patient isn’t eating. Some linger as kidney function drops.
  • A: ACE inhibitors like lisinopril shut off angiotensin II, and angiotensin II is the kidney’s thumb. Take it away from a dehydrated patient and filtering pressure drops.
  • D: diuretics like HCTZ and furosemide turn the spigot down further on a patient who’s already losing fluid.
  • M: metformin doesn’t hurt the kidneys, but they’re its only way out. When they slow down, metformin builds up, and so does the risk of lactic acidosis.
  • A: ARBs like losartan take the thumb off the same way ACE inhibitors do.
  • N: NSAIDs like ibuprofen and naproxen kink the hose near the spigot by blocking the prostaglandins that hold the inflow open. (Spigot down, hose kinked, thumb off: that’s the triple whammy from our drug interactions article)
  • S: SGLT2 inhibitors like Jardiance and Farxiga pull glucose and water out through the urine, deepening dehydration, and raise DKA risk, sometimes with a normal glucose (more on that next).

GLP-1 drugs like semaglutide aren’t in the mnemonic, but the ADA Standards note they may need holding when GI symptoms are significant ⁸.

SADMANS isn’t a US guideline, and the evidence behind sick-day lists is mostly expert opinion⁵. The ADA Standards say to consider holding metformin and SGLT2 inhibitors when the patient can’t keep up with eating and drinking or kidney injury is a concern ⁸, and Jardiance’s label says to withhold it, if possible, in situations that could predispose to ketoacidosis ⁹. The ADA’s patient guide says to keep taking diabetes medications as prescribed unless the doctor advises otherwise ⁴. That “unless” is our job. Which pills pause for which patient, and when they restart (UK practice is usually after 24 to 48 hours of normal eating and drinking⁶, are prescriber decisions that belong in the written plan. The plan is for emergency use only, after the patient has tried to reach their prescriber or pharmacist first.

And just to be clear here, insulin never pauses. Basal insulin keeps going even when the patient isn’t eating⁸. Mealtime doses follow the food¹⁰, and the total dose can change while they’re sick ³, which is exactly the kind of adjustment that belongs in the plan. Stopping basal insulin because they can’t eat is the classic road to DKA, and in type 1 that road is short. (For keeping insulin cool when the power’s out, see our insulin storage article.)

Who owns the sick-day conversation?

The ADA already tells patients to make a sick-day action plan with their doctor before they ever get sick ⁴. I don’t think many of us are having that conversation, in the office or at the pharmacy. In more than 10 years as a pharmacist, I’ve had five or fewer of them. I’m not proud of that at all, but patients rarely, if ever, proactively brought up the topic. At my busy 24-hour pharmacy, counseling got to the single most important thing a patient needs to start the medication (and sick days didn’t usually make the cut). 

Part of the problem is that nobody owns the med list. The pills that pause on a sick day often come from two prescribers: metformin and an SGLT2 inhibitor from primary care, lisinopril and a diuretic from cardiology. Each prescriber may only see their half. The pharmacy profile shows every prescription filled there, from every prescriber, and our interaction software checks across all of it.

That makes this a pharmacy counter conversation as much as an office one. For a patient on metformin, Jardiance, lisinopril, and HCTZ, here’s how it would sound coming from me:

“When you’re sick, it can really change your diabetes and your medications and you have to be extra careful. Here’s what to know in a nutshell. If you’re throwing up or can’t keep fluids down, some of your pills may need to pause until you’ve been eating and drinking normally for a day or two. For you, that’s probably all four, but your doctor makes that call, so let’s ask them to put it in writing now. I’ll send a fax requesting that right now.  Because you’re on Jardiance, check your ketones when you’re sick, even if your sugar looks normal. Call your doctor or the pharmacy first. If you can’t reach anyone, these symptoms mean you need to get to emergency care ASAP: throwing up or diarrhea for more than 4 hours, moderate or large ketones, or a sugar over 300 twice.“

How ketones work, and why a normal meter reading can fool you

Ketones are what the liver makes from fat when cells can’t get enough insulin to use glucose. A little after a long fast is normal. When insulin runs short in a dehydrated patient, ketones build faster than the body clears them. Then the blood turns acidic, and that’s DKA (diabetic ketoacidosis).

On an SGLT2 inhibitor, the kidneys keep dumping glucose into the urine, so the meter can read 150 while ketones climb. Jardiance’s label warns that glucose at presentation can sit below what we’d expect for DKA, for example under 250 ⁹, and the ADA defines euglycemic DKA as DKA with a glucose under 200 ¹¹. The glucose number stops being a warning light, so an SGLT2 user’s plan needs to be checking ketones when sick, whatever the meter reads.

The tool matters too. There are two main ketones in the blood, and urine strips only see one of them. In DKA, most of the ketones are the other kind¹², so a strip can read low while the real level is high. That’s why the ADA wants at-risk SGLT2 users to have a blood ketone meter¹³. From what I’ve seen working in the pharmacy a lot of urine strips and keto meters are being bought up by the keto, weight-loss, and muscle-building crowds, so they can be kind of hard to find sometimes. (Funny twist, since the ADA also tells us to steer SGLT2 users away from keto eating¹³.) Put the strips, or a blood meter, on the written plan and make sure that patients actually have some on hand so they’re handy before they are needed.

The Wilderness Medical Society tells insulin users heading into the backcountry to carry a ketone kit, and it treats DKA as an emergency that calls for evacuation¹⁴. A hurricane week at home isn’t the backcountry, but it shares the part the guideline is written around: limited access to care. Moderate or large ketones means to get to emergency care, not wait for the phone.

What to look for in the OTC aisle

The ADA’s guide tells patients to work out which OTC medications are safe with their doctor before they get sick ⁴, but it doesn’t say which ones. The pharmacist is the natural person to fill in that blank. Every pick comes back to the two questions from the pause list: what it does to the kidneys, and what it does to glucose.

  • Ibuprofen and naproxen are the N in SADMANS, and they hide in combination products (one 12-hour sinus product pairs naproxen with pseudoephedrine). The plan should name the swap for pain and fever, usually acetaminophen if the liver allows.
  • Pseudoephedrine’s Drug Facts tell anyone with diabetes to ask a doctor before using it¹⁵. 
  • The ADA’s guide says to alternate water and electrolyte drinks ⁴, and sugar isn’t automatically the enemy. A patient who can’t eat still needs about 50 grams of carbohydrate every 4 hours ³, and regular juice or soda may be how they get it.
  • Glucose tabs or gel are on the ADA’s sick-day supply list ⁴, and they matter most for anyone on a sulfonylurea or insulin who can’t eat.

Like everything else on the plan, these are emergency-use answers, for when the patient has tried to reach their pharmacist or prescriber first and can’t get through.

How to write the plan before storm season

The ADA’s guide already lists what belongs in a sick-day plan ⁴. The disaster version fills in every line with this patient’s medication names and strengths written on paper, kept with their medication list:

  • Which of their pills pause, by name, and when each one restarts
  • For insulin users, the basal dose that keeps going and how to adjust mealtime and correction doses
  • How often to check glucose and ketones, and with what (urine strips or a blood meter)
  • The OTC picks for fever and pain, congestion, fluids, and lows
  • The numbers that mean get to emergency care when no one answers:
    • vomiting or diarrhea for more than 4 hours
    • moderate or large ketones, or the blood ketone number you set
    • glucose over 300 on two readings despite corrections
    • fever over 101°F lasting more than 24 hours
    • signs of dehydration, like dizziness or dark urine
  • Who to call first, their number, and when they are reachable: the prescriber or the pharmacy

The plan is for emergency use only, after the patient has tried those calls and can’t get through.

The bottom line

Sick-day care for diabetes is all or nothing right now. Either the clinic or the pharmacy picks up, or the patient is alone with four bottles and a meter just guessing and winging it with what they look up online. A written plan is the missing middle layer: the decision made ahead of time by the person who should make it, ready for the day nobody answers. That’s appropriate medical preparation at its simplest. It’s in no way a replacement for primary care; we’re here for the times when primary care isn’t there. Our team of physicians, PAs, and pharmacists is building the version of this plan for the week the clinic’s phone is dead, and we’ll publish the framework as we go.

Before the next storm, write the plan for every patient on an SGLT2 inhibitor, metformin, or insulin. Pharmacists, start it at the counter.

A sick day in a disaster will never be easy. A plan on paper keeps 1 + 1 + 1 a lot closer to 3.


Sources

  1. Martínez-Lozano M, Noboa C, Alvarado-González G, Joshipura KJ. Hurricanes Irma and Maria and diabetes incidence in Puerto Rico. BMC Public Health. 2023;23:1019. https://pmc.ncbi.nlm.nih.gov/articles/PMC10227808/
  2. Centers for Disease Control and Prevention. National Diabetes Statistics Report. Updated September 16, 2026. https://www.cdc.gov/diabetes/php/data-research/index.html
  3. Centers for Disease Control and Prevention. Managing sick days. Updated May 15, 2024. https://www.cdc.gov/diabetes/living-with/managing-sick-days.html
  4. American Diabetes Association. Sick Day Guide for People with Diabetes (patient version). September 2025. Based on the Standards of Care in Diabetes-2025. https://professional.diabetes.org/sites/dpro/files/2025-09/SickDayGuide_Final.pdf
  5. Watson KE, Dhaliwal K, McMurtry E, et al. Sick day medication guidance for people with diabetes, kidney disease, or cardiovascular disease: a systematic scoping review. Kidney Med. 2022;4(9):100491. https://pmc.ncbi.nlm.nih.gov/articles/PMC9420951/
  6. Healthcare Improvement Scotland. Medicines sick day guidance card, version 4. 2026. https://www.healthcareimprovementscotland.scot/wp-content/uploads/2026/05/Medicines-sick-day-guidance-card-A6-June-2026.pdf
  7. Northern Ireland Formulary. Sick day rules. Accessed October 5, 2026. https://niformulary.hscni.net/formulary/6-0-endocrine/6-1-drugs-used-in-diabetes/6-1-2-antidiabetic-drugs/sick-day-rules/
  8. American Diabetes Association Professional Practice Committee for Diabetes. 6. Glycemic goals, hypoglycemia, and hyperglycemic crises: Standards of Care in Diabetes-2026. Diabetes Care. 2026;49(Suppl 1):S132-S149. https://pmc.ncbi.nlm.nih.gov/articles/PMC12690178/
  9. Jardiance (empagliflozin) prescribing information. Boehringer Ingelheim Pharmaceuticals; revised January 2026. DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=faf3dd6a-9cd0-39c2-0d2e-232cb3f67565
  10. RxFiles. Protecting the kidneys. September 2025. https://www.rxfiles.ca/RxFiles/uploads/documents/SADMANS-Rx.pdf
  11. American Diabetes Association Professional Practice Committee for Diabetes. 16. Diabetes care in the hospital: Standards of Care in Diabetes-2026. Diabetes Care. 2026;49(Suppl 1):S339-S355. doi:10.2337/dc26-S016
  12. Umpierrez GE, et al. Hyperglycemic crises in adults with diabetes: a consensus report. Diabetes Care. 2024;47(8):1257-1275. https://pmc.ncbi.nlm.nih.gov/articles/PMC11272983/
  13. American Diabetes Association Professional Practice Committee for Diabetes. 9. Pharmacologic approaches to glycemic treatment: Standards of Care in Diabetes-2026. Diabetes Care. 2026;49(Suppl 1):S183-S215. https://pmc.ncbi.nlm.nih.gov/articles/PMC12690185/
  14. VanBaak KD, et al. Wilderness Medical Society clinical practice guidelines for diabetes management. Wilderness Environ Med. 2019;30(4 Suppl):S121-S140. Written for wilderness athletes; recommendations cited: carry a ketone testing kit (grade 1B), and evacuate for DKA or HHS (grade 1A). https://pmc.ncbi.nlm.nih.gov/articles/PMC7510348/
  15. Sudafed Sinus Congestion 12 Hour (pseudoephedrine HCl) Drug Facts label. Kenvue; revised November 8, 2024. DailyMed. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=d600b5d5-7d95-4ad6-a95b-6d73502743d7


Lifesaving Solutions

Everyone should be empowered to care for themselves and their loved ones during the unexpected. Check out our recent lifesaving products today.

Recent Posts

Keeping you informed and safe.

For Clinicians | New World Screwworm in Humans

For Clinicians | New World Screwworm in Humans

For Clinicians | New World Screwworm in Humans: The Wound Check, the Larvae, and the Risk By Dr. Jamie Wilkey, PharmD, Director of Clinical EducationMedically reviewed and edited by Kristen Carpenter, PA-C New World screwworm is the latest health headline. This one...

read more

Join Our Newsletter

Our mission is to help you be more medically prepared. Join our newsletter and follow us on social media for health and safety tips each week!